Related Experiment Video
Updated: Jan 19, 2026


Intraventricular Drug Delivery and Sampling for Pharmacokinetics and Pharmacodynamics Study
Published on: March 31, 2022
Augmented renal clearance is associated with inadequate antibiotic pharmacokinetic/pharmacodynamic target in Asian
Chien-Chih Wu1,2, Chih-Hsun Tai1, Wen-You Liao2
1Department of Pharmacy, National Taiwan University Hospital, College of Medicine, National Taiwan University, Taipei, Taiwan.

Background:
Augmented renal clearance (ARC) is common in critically ill patients and could result in subtherapeutic antibiotic concentration. However, data in the Asian population are still lacking. The aim of this study was to explore the incidence and risk factors of ARC and its effect on β-lactam pharmacokinetics/pharmacodynamics (PK/PD) in Asian populations admitted to a medical ICU. In addition, we evaluated the appropriateness of using three estimated glomerular filtration (eGFR) formulas [Cockcroft-Gault (CG), Modification of Diet in Renal Disease (MDRD), and the Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI)] as screening tools.
Methods:
We measured 2-, 8-, and 24-hr creatinine clearance (CLCr) and calculated eGFR by using three formulas for each. ARC was defined as CLCr24hr >130 mL/min/1.73 m2. Concentrations at the mid-dosing interval and prior to the next dose were collected if patients received the β-lactam antibiotic of piperacillin/tazobactam, cefepime, and meropenem, to determine the PK/PD index of fT > MIC. Multiple logistic regression analysis was conducted to identify the risk factors for ARC. Pearson correlation coefficient and the Bland and Altman method were applied to assess the accuracy of CLCr2hr, CLCr8hr, and eGFR for predicting ARC.
Results:
Of 100 patients, 46 (46%) manifested ARC. Younger age (<50 years) and lower Sequential Organ Failure Assessment score increased the likelihood of ARC. ARC resulted in a low chance of achieving 50% fT >4MIC (33% vs 75%, p<0.01), 100% fT > MIC (23% vs 69%, p<0.01), and 100% fT >4MIC (3% vs 25%, p<0.02). CLCr8hr wielded the best correlation and agreement with CLCr24hr. eGFRCG was the most appropriate screening tool, and the optimal cutoff value for detecting ARC was 130.5 mL/min/1.73 m2.
Conclusion:
ARC is associated with inadequate β-lactam PK/PD target in Asian ICU.
Insights
Augmented renal clearance (ARC) in Asian ICU patients often leads to subtherapeutic antibiotic levels. This study identifies risk factors and recommends the Cockcroft-Gault formula for screening.
Area of Science:
- Pharmacology
- Nephrology
- Critical Care Medicine
Background:
- Augmented renal clearance (ARC) is prevalent in critically ill patients, potentially causing subtherapeutic antibiotic concentrations.
- Limited data exists on ARC in Asian populations, necessitating further investigation.
- Understanding ARC is crucial for optimizing antibiotic therapy in diverse patient groups.
Purpose of the Study:
- To determine the incidence and risk factors of ARC in Asian medical ICU patients.
- To assess the impact of ARC on β-lactam pharmacokinetic/pharmacodynamic (PK/PD) targets.
- To evaluate the efficacy of estimated glomerular filtration rate (eGFR) formulas for ARC screening.
Main Methods:
- Measured creatinine clearance (CLCr) at 2, 8, and 24 hours.
- Defined ARC as CLCr24hr >130 mL/min/1.73 m².
- Collected antibiotic concentrations to determine PK/PD indices (fT > MIC).
- Used logistic regression for risk factor analysis and correlation/Bland-Altman for screening tool accuracy.
Main Results:
- 46% of patients exhibited ARC.
- Younger age (<50 years) and lower SOFA scores were associated with ARC.
- ARC significantly reduced the achievement of target β-lactam PK/PD indices.
- Creatinine clearance at 8 hours (CLCr8hr) showed the best correlation with 24-hour CLCr.
- eGFR-Cockcroft-Gault (eGFRCG) was the most suitable screening tool for ARC.
Conclusions:
- ARC is common in Asian ICU patients and is linked to inadequate β-lactam PK/PD target attainment.
- Early identification of ARC is essential for dose adjustment and effective antibiotic therapy.
- The Cockcroft-Gault formula is recommended for screening ARC in this population.
Related Concept Videos
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 09:18
Intraventricular Drug Delivery and Sampling for Pharmacokinetics and Pharmacodynamics Study
 08:41
Carotid Artery Infusions for Pharmacokinetic and Pharmacodynamic Analysis of Taxanes in Mice
 01:06
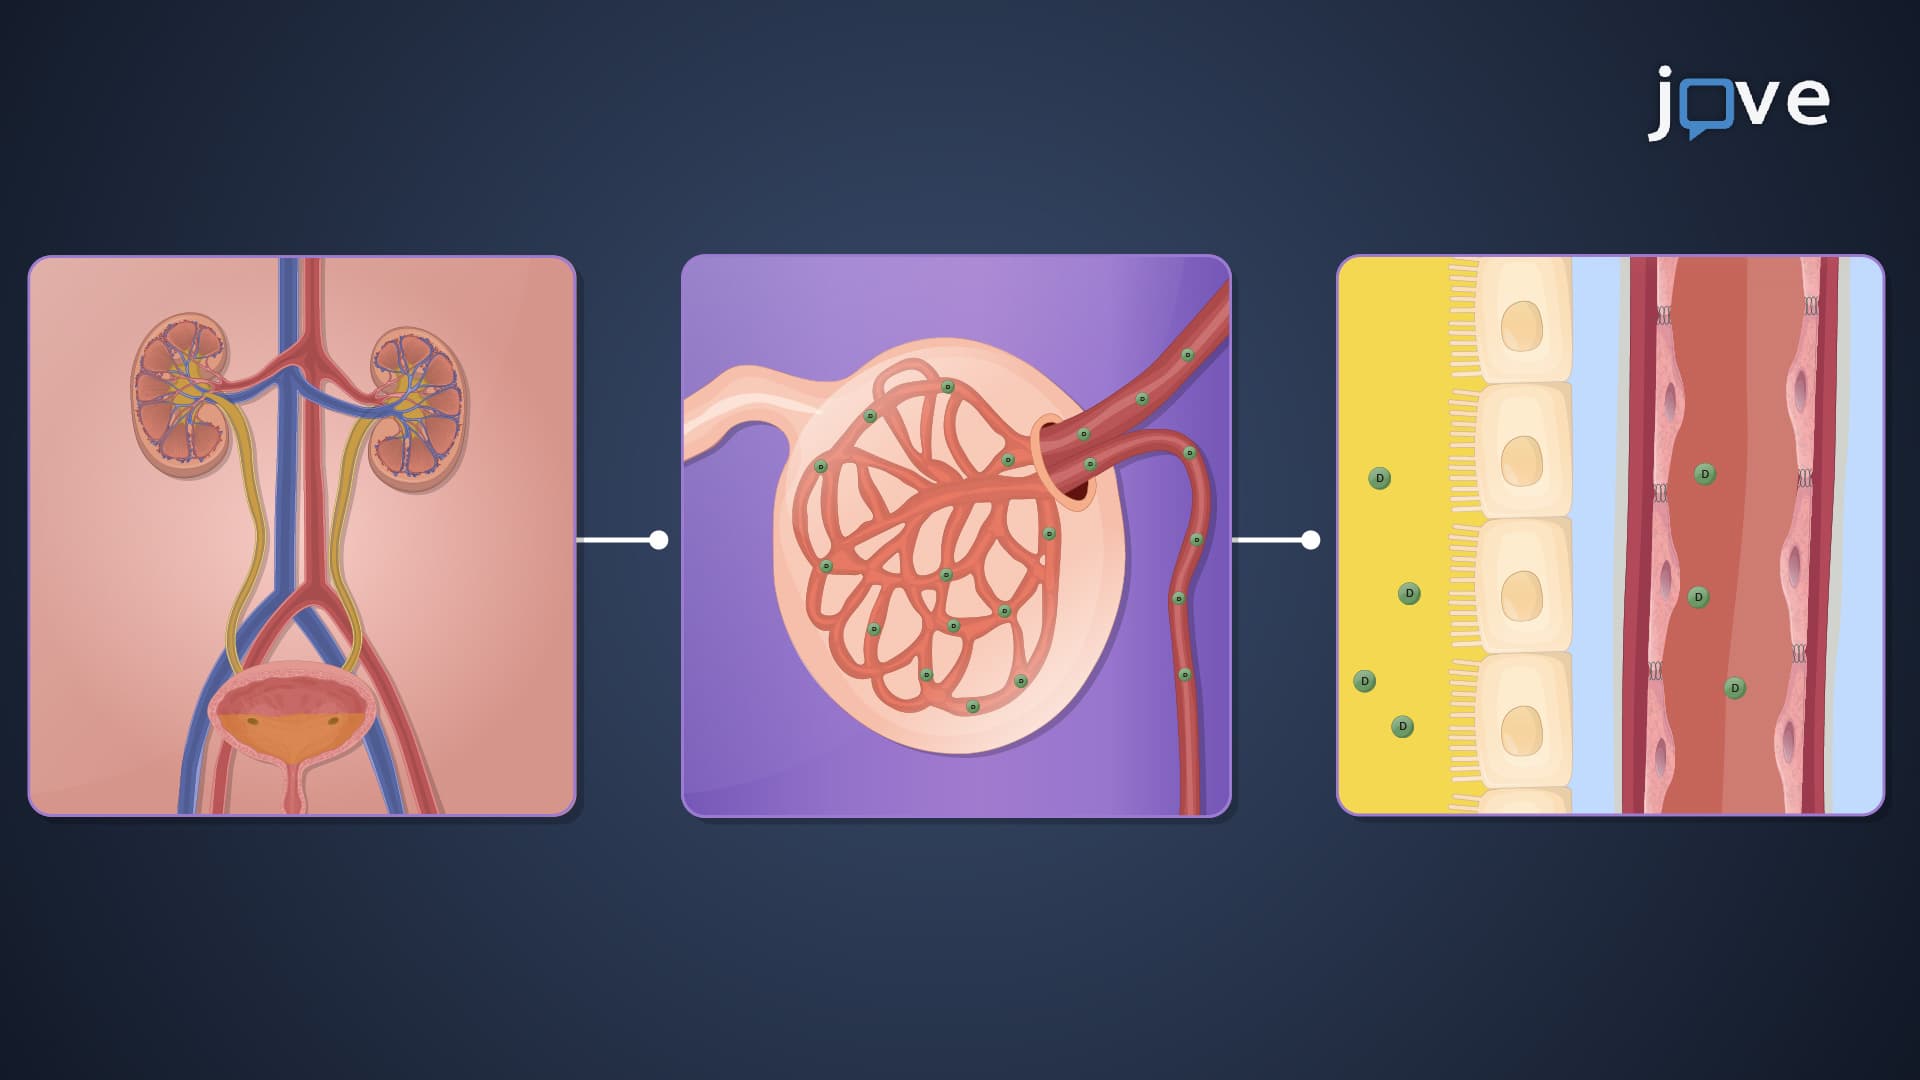
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...