Related Experiment Video
Updated: Aug 6, 2026
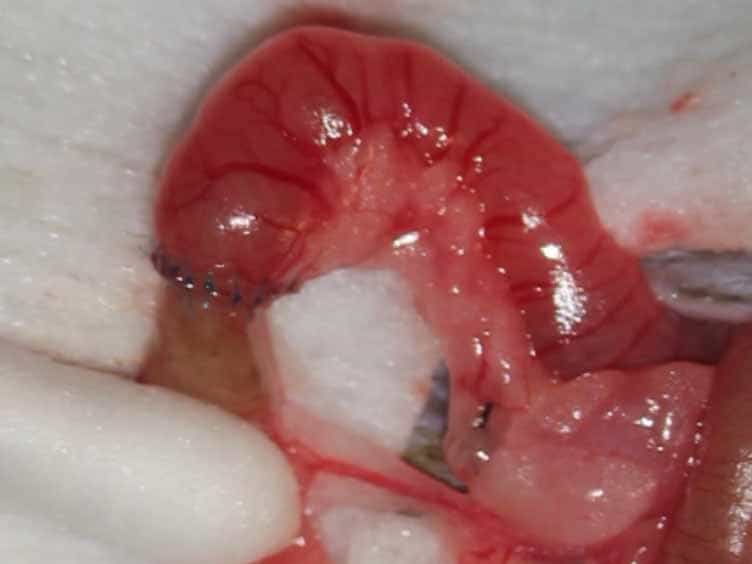
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
[Iatrogenic gastrointestinal hemorrhages. A review of 108 cases (author's transl)]

Macroscopic gastrointestinal hemorrhages caused by the consumption of oral drugs are relatively scarce among patients receiving antirheumatic treatment. On the other hand, in a high percentage of all cases of digestive bleeding, antirheumatic drugs were administered shortly beforehand. A review of 216 cases with hematemesis and/or melena are presented. In 50 percent of the patients there was evidence of previous administration of potentially ulcerogenic drugs capable of causing hemorrhages in the digestive tract. Salicylates predominated among the compounds that were considered to be responsible for hemorrhages (salicylates, corticosteroids, reserpine, and other antirheumatic products). The mechanisms involved in producing iatrogenic hemorrhages were examined and the drugs were classified as precipitating and directly ulcerogenic compounds. Precipitating drugs were those which were able to reactivate a preexisting lesion (reserpine, glucocorticoids, phenylbutazone, etc.). The ulcerogenic drugs included those products that could provoke a lesion of previously unimpaired digestive mucosa (salicylates).
Macroscopic gastrointestinal hemorrhages caused by the consumption of oral drugs are relatively scarce among patients receiving antirheumatic treatment. On the other hand, in a high percentage of all cases of digestive bleeding, antirheumatic drugs were administered shortly beforehand. A review of 216 cases with hematemesis and/or melena are presented. In 50 percent of the patients there was evidence of previous administration of potentially ulcerogenic drugs capable of causing hemorrhages in the digestive tract. Salicylates predominated among the compounds that were considered to be responsible for hemorrhages (salicylates, corticosteroids, reserpine, and other antirheumatic products). The mechanisms involved in producing iatrogenic hemorrhages were examined and the drugs were classified as precipitating and directly ulcerogenic compounds. Precipitating drugs were those which were able to reactivate a preexisting lesion (reserpine, glucocorticoids, phenylbutazone, etc.). The ulcerogenic drugs included those products that could provoke a lesion of previously unimpaired digestive mucosa (salicylates).
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:07
Intestinal Obstruction II: Pathophysiology