Related Experiment Video
Updated: Jan 19, 2026

Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
Published on: January 29, 2014
Novel insights into the treatment of complement-mediated hemolytic anemias
Sigbjørn Berentsen1, Anita Hill2, Quentin A Hill2
1Department of Research and Innovation, Haugesund Hospital, P.O. Box 2170, Haugesund, 5504, Norway.

Complement-mediated hemolytic anemias can either be caused by deficiencies in regulatory complement components or by autoimmune pathogenesis that triggers inappropriate complement activation. In paroxysmal nocturnal hemoglobinuria (PNH) hemolysis is entirely complement-driven. Hemolysis is also thought to be complement-dependent in cold agglutinin disease (CAD) and in paroxysmal cold hemoglobinuria (PCH), whereas warm antibody autoimmune hemolytic anemia (wAIHA) is a partially complement-mediated disorder, depending on the subtype of wAIHA and the extent of complement activation. The pathophysiology, clinical presentation, and current therapies for these diseases are reviewed in this article. Novel, complement-directed therapies are being rapidly developed. Therapeutic terminal complement inhibition using eculizumab has revolutionized the therapy and prognosis in PNH but has proved less efficacious in CAD. Upstream complement modulation is currently being investigated and appears to be a highly promising therapy, and two such agents have entered phase II and III trials. Of these, the anti-C1s monoclonal antibody sutimlimab has shown favorable activity in CAD, while the anti-C3 cyclic peptide pegcetacoplan appears to be promising in PNH as well as CAD, and may also have a therapeutic potential in wAIHA.
Complement-mediated hemolytic anemias can either be caused by deficiencies in regulatory complement components or by autoimmune pathogenesis that triggers inappropriate complement activation. In paroxysmal nocturnal hemoglobinuria (PNH) hemolysis is entirely complement-driven. Hemolysis is also thought to be complement-dependent in cold agglutinin disease (CAD) and in paroxysmal cold hemoglobinuria (PCH), whereas warm antibody autoimmune hemolytic anemia (wAIHA) is a partially complement-mediated disorder, depending on the subtype of wAIHA and the extent of complement activation. The pathophysiology, clinical presentation, and current therapies for these diseases are reviewed in this article. Novel, complement-directed therapies are being rapidly developed. Therapeutic terminal complement inhibition using eculizumab has revolutionized the therapy and prognosis in PNH but has proved less efficacious in CAD. Upstream complement modulation is currently being investigated and appears to be a highly promising therapy, and two such agents have entered phase II and III trials. Of these, the anti-C1s monoclonal antibody sutimlimab has shown favorable activity in CAD, while the anti-C3 cyclic peptide pegcetacoplan appears to be promising in PNH as well as CAD, and may also have a therapeutic potential in wAIHA.

Related Concept Videos
 06:29
Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
 05:40
A Serum Bactericidal Assay for the Complement-Mediated Bactericidal Activity of Antibodies
 05:35
A Point-of-Care Method with Integrated Decision Support Tool to Estimate Anemia at Population Level
 01:27
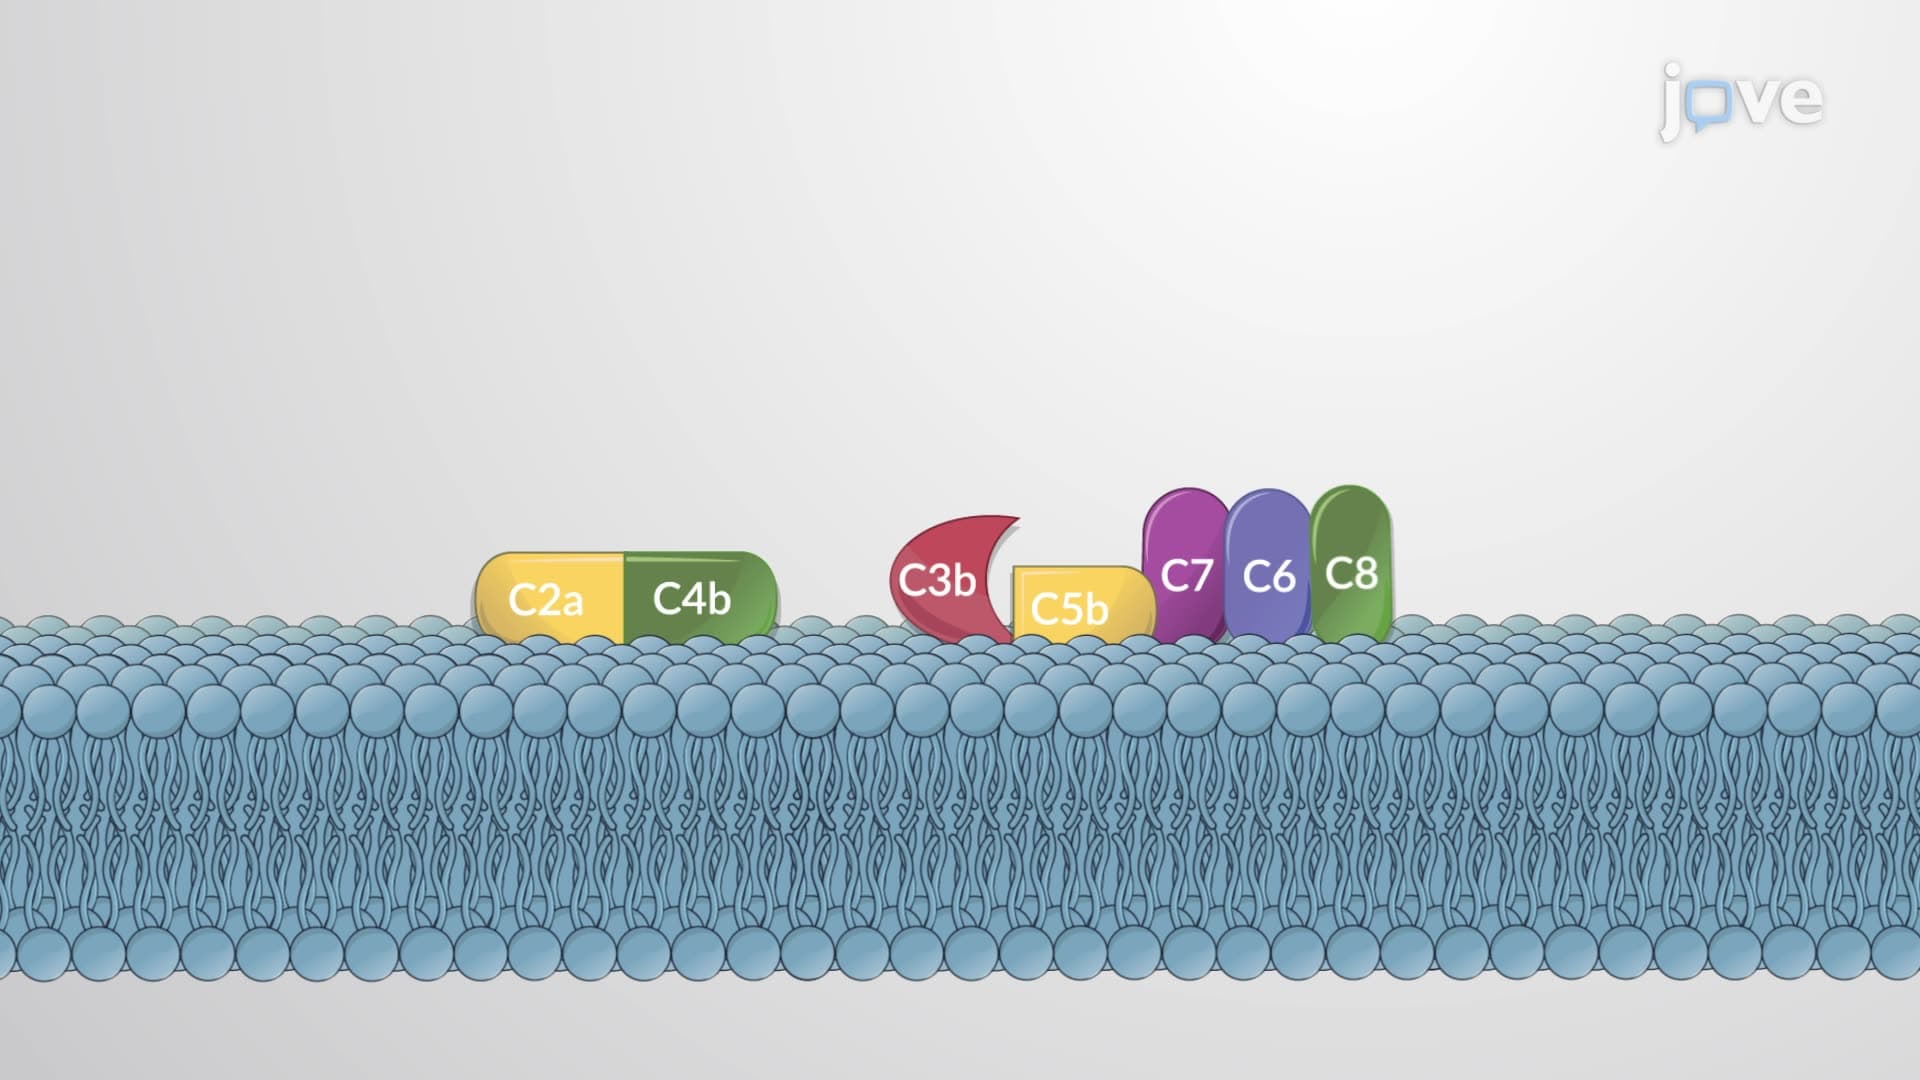
Complement System
 00:49
Complementation Tests
Organisms heterozygous for different mutations are crossed pairwise in all combinations. If present on different genes, the mutations can complement each other by providing the missing...
 10:21
Mechanistic Insight into the Development of TNBS-Mediated Intestinal Fibrosis and Evaluating the Inhibitory Effects of Rapamycin