Related Experiment Video
Updated: Jan 19, 2026
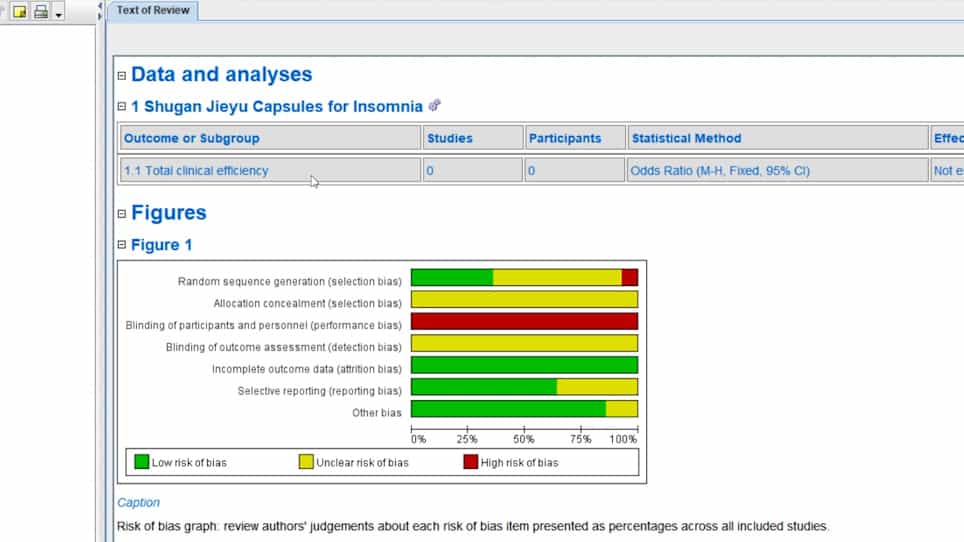
Meta-Analysis of the Effectiveness and Safety of Shugan Jieyu Capsules for the Treatment of Insomnia
Published on: February 17, 2023
Antibiotic treatment for spontaneous bacterial peritonitis in people with decompensated liver cirrhosis: a network
Laura Iogna Prat1, Peter Wilson, Suzanne C Freeman
1Sheila Sherlock Liver Centre, Royal Free Hospital and the UCL Institute of Liver and Digestive Health, London, UK.

Background:
Approximately 2.5% of all hospitalisations in people with cirrhosis are for spontaneous bacterial peritonitis (SBP). Antibiotics, in addition to supportive treatment (fluid and electrolyte balance, treatment of shock), form the mainstay treatments of SBP. Various antibiotics are available for the treatment of SBP, but there is uncertainty regarding the best antibiotic for SBP.
Objectives:
To compare the benefits and harms of different antibiotic treatments for spontaneous bacterial peritonitis (SBP) in people with decompensated liver cirrhosis.
Search Methods:
We searched CENTRAL, MEDLINE, Embase, Science Citation Index Expanded, World Health Organization International Clinical Trials Registry Platform, and trials registers until November 2018 to identify randomised clinical trials on people with cirrhosis and SBP.
Selection Criteria:
We included only randomised clinical trials (irrespective of language, blinding, or publication status) in adults with cirrhosis and SBP. We excluded randomised clinical trials in which participants had previously undergone liver transplantation.
Data Collection And Analysis:
Two review authors independently identified eligible trials and collected data. The outcomes for this review included mortality, serious adverse events, any adverse events, resolution of SBP, liver transplantation, and other decompensation events. We performed a network meta-analysis with OpenBUGS using Bayesian methods and calculated the odds ratio, rate ratio, and hazard ratio with 95% credible intervals (CrIs) based on an available-case analysis, according to the National Institute of Health and Care Excellence (NICE) Decision Support Unit guidance.
Main Results:
We included a total of 12 trials (1278 participants; 13 antibiotics) in the review. Ten trials (893 participants) were included in one or more outcomes in the review. The trials that provided the information included patients having cirrhosis with or without other features of decompensation of varied aetiologies. The follow-up in the trials ranged from one week to three months. All the trials were at high risk of bias. Only one trial was included under each comparison for most of the outcomes. Because of these reasons, there is very low certainty in all the results. The majority of the randomised clinical trials used third-generation cephalosporins, such as intravenous ceftriaxone, cefotaxime, or ciprofloxacin as one of the interventions.Overall, approximately 75% of trial participants recovered from SBP and 25% of people died within three months. There was no evidence of difference in any of the outcomes for which network meta-analysis was possible: mortality (9 trials; 653 participants), proportion of people with any adverse events (5 trials; 297 participants), resolution of SBP (as per standard definition, 9 trials; 873 participants), or other features of decompensation (6 trials; 535 participants). The effect estimates in the direct comparisons (when available) were very similar to those of network meta-analysis. For the comparisons where network meta-analysis was not possible, there was no evidence of difference in any of the outcomes (proportion of participants with serious adverse events, number of adverse events, and proportion of participants requiring liver transplantation). Due to the wide CrIs and the very low-certainty evidence for all the outcomes, significant benefits or harms of antibiotics are possible.None of the trials reported health-related quality of life, number of serious adverse events, or symptomatic recovery from SBP.
Funding:
the source of funding for two trials were industrial organisations who would benefit from the results of the trial; the source of funding for the remaining 10 trials was unclear.
Authors' Conclusions:
Short-term mortality after SBP is about 25%. There is significant uncertainty about which antibiotic therapy is better in people with SBP.We need adequately powered randomised clinical trials, with adequate blinding, avoiding post-randomisation dropouts (or performing intention-to-treat analysis), and using clinically important outcomes, such as mortality, health-related quality of life, and adverse events.

Related Concept Videos
 02:56
An ATP Utilization Assay for Determining Bacterial Survival Under Antibiotics Treatment
 04:34
Meta-Analysis of the Effectiveness and Safety of Shugan Jieyu Capsules for the Treatment of Insomnia
 08:23
Visualization of Bacterial Resistance using Fluorescent Antibiotic Probes
 08:36
The Adjuvant Efficacy of Angong Niuhuang Pill in the Treatment of Viral Encephalitis: A Meta-Analysis of Randomized Controlled Trials
 12:08
Multi-scale Analysis of Bacterial Growth Under Stress Treatments
 12:29
Population and Single-Cell Analysis of Antibiotic Persistence in Escherichia coli