Related Experiment Video
Updated: Jan 19, 2026
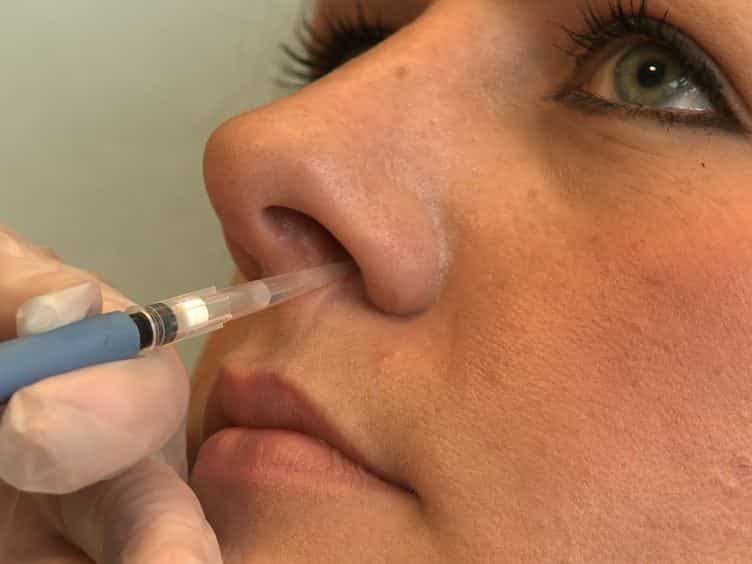

Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
Preferences for Adult Pneumococcal Vaccine Recommendations Among United States Health Care Providers
Patricia Sacco1, Kelley Myers2, Christine Poulos2
1RTI Health Solutions, Research Triangle Park, NC, USA. psacco@rti.org.

Introduction:
In 2014, the Advisory Committee on Immunization Practices (ACIP) of the US Centers for Disease Control and Prevention (CDC) recommended 13-valent pneumococcal conjugate vaccine (PCV13) followed by 23-valent pneumococcal polysaccharide vaccine (PPSV23) for all adults aged ≥ 65 years, with a commitment to revisit the recommendation for PCV13 because of declining vaccine-type disease. The Evidence-to-Recommendation framework used by the ACIP includes review of evidence regarding feasibility and stakeholder acceptability, but no surveys of vaccinator preferences have been published in the literature.
Methods:
Physicians (N = 700), physician assistants (N = 100), pharmacists (N = 100), and nurse practitioners (N = 100) who recently prescribed, administered, or recommended adult pneumococcal vaccine were surveyed in March 2018. Object-case best-worst scaling was used to assess preferences among potential recommendation scenarios: retaining the then-current 2014 recommendation without a scheduled re-evaluation, retaining with a scheduled re-evaluation, revising PCV13 to Category B (retaining PPSV23 as Category A), removing PCV13 (retaining PPSV23 as Category A), and removing both PCV13 and PPSV23.
Results:
Providers' most preferred recommendations were retaining the 2014 recommendation with another planned re-evaluation (52.6%) and retaining the then-current recommendation without planned re-evaluation (40.0%). Few preferred changing PCV13 to Category B (3.2%), removing PCV13 (3.7%), or removing both pneumococcal vaccines (0.5%).
Conclusions:
The majority of vaccinators surveyed preferred to retain the 2014 recommendation, either with another scheduled reassessment or indefinitely.
Funding:
Pfizer, Inc.
More Related Videos
 11:32
Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
 13:47
Opsono-Adherence Assay to Evaluate Functional Antibodies in Vaccine Development Against Bacillus anthracis and Other Encapsulated Pathogens
Published on: May 19, 2020
Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...