Related Experiment Video
Updated: Jan 19, 2026


Author Spotlight: Assessing the Cardiovascular Profile of Patients with Metabolic Syndrome
Published on: September 27, 2024
Increased Carotid Intima-Media Thickness (IMT) in Hyperuricemic Individuals May Be Explained by Hyperhomocysteinemia
Ji Ho Park1, Jung Soo Song1, Sang Tae Choi2
1Division of Rheumatology, Department of Internal Medicine, Chung-Ang University College of Medicine, Seoul, Korea.

Insights
Hyperuricemia is linked to higher homocysteine levels and worsened carotid intima-media thickness (IMT), a marker of cardiovascular disease. Renal function impairment may exacerbate this relationship in hyperuricemic patients.
Area of Science:
- Cardiovascular Disease Research
- Metabolic Disorders
- Nephrology
Background:
- Hyperuricemia and hyperhomocysteinemia are established cardiovascular disease risk factors.
- The relationship between carotid intima-media thickness (IMT) and homocysteine (Hcy) in hyperuricemic patients remains under-investigated.
- This study explores the association between hyperuricemia, hyperhomocysteinemia, and carotid IMT.
Purpose of the Study:
- To investigate the association between hyperuricemia and increased carotid IMT.
- To examine the role of hyperhomocysteinemia in this association.
- To identify risk factors for carotid plaque in hyperuricemic patients.
Main Methods:
- A cross-sectional study of 1,222 patients from January 2013 to December 2015.
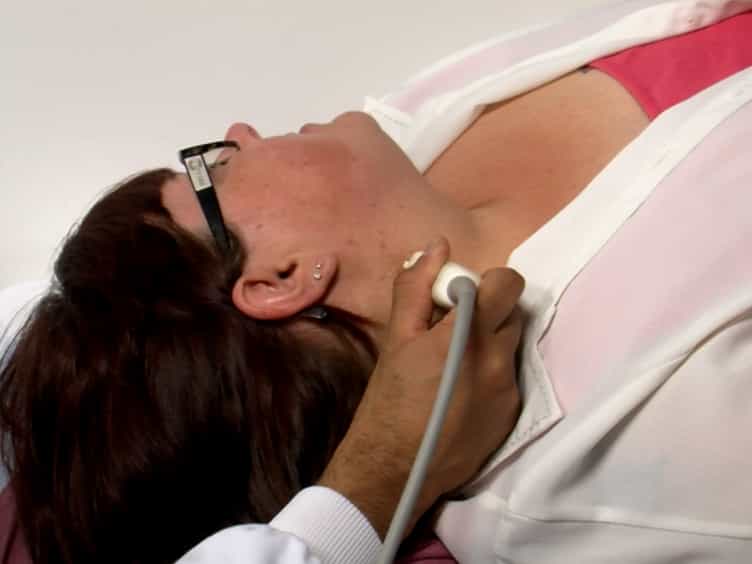
- Serum Hcy levels measured by competitive immunoassay; carotid IMT assessed by B-mode ultrasonography.
- Hyperuricemia defined as serum uric acid >7.0 mg/dL (men) or >5.6 mg/dL (women); hyperhomocysteinemia as serum Hcy >15 μmol/L.
Main Results:
- Hyperuricemic patients had significantly higher serum Hcy levels and lower estimated glomerular filtration rate (eGFR) compared to normouricemic patients.
- Serum Hcy level and fasting glucose were independent risk factors for carotid plaque.
- In hyperuricemic patients, serum Hcy correlated with eGFR, and carotid IMT correlated with both serum Hcy and eGFR.
Conclusions:
- Renal function impairment in hyperuricemic patients is associated with increased serum Hcy levels.
- These findings suggest that impaired renal function may contribute to worsened carotid IMT in hyperuricemic individuals via elevated Hcy.
- Serum Hcy and eGFR are significant predictors of carotid IMT in this population.
Background:
Both hyperuricemia and hyperhomocysteinemia are known as main risk factors of cardiovascular diseases. There has been, however, no report on the relationship between carotid intima-media thickness (IMT) and homocysteine (Hcy) in hyperuricemic patients. This study aimed to investigate how hyperuricemia is associated with increased carotid IMT with a focus on hyperhomocysteinemia.
Methods:
This cross-sectional study included 1,222 patients who visited the Chung-Ang University Hospital Health Promotion Center from January 2013 to December 2015. The serum Hcy levels were estimated with a competitive immunoassay using the direct chemiluminescence method. The carotid IMT was measured by B-mode carotid ultrasonography. The definition of hyperuricemia was a serum uric acid level > 7.0 mg/dL for men or > 5.6 mg/dL for women, and hyperhomocysteinemia was defined as serum levels > 15 μol/L.
Results:
The hyperuricemic patients showed significantly higher serum Hcy levels and lower estimated glomerular filtration rate (eGFR) than did normouricemic patients (13.39 ± 4.42 vs. 11.69 ± 3.65 μol/L, P < 0.001; 85.16 ± 19.18 vs. 96.14 ± 16.63, P < 0.001, respectively). Serum Hcy level (odds ratio [OR], 1.050; 95% confidence interval [CI], 1.009-1.092) and fasting glucose level (OR, 1.018; 95% CI, 1.011-1.026) were independent risk factors for carotid plaque. In patients with hyperuricemia, the serum Hcy levels correlated with the eGFR (γ = -0.478, P < 0.001). The carotid IMT correlated with serum Hcy levels and eGFR (γ = 0.196, P = 0.008; γ = - 0.297, P < 0.001, respectively) but not with the serum lipid profile.
Conclusion:
These results suggest that renal function impairment in hyperuricemic patients may worsen carotid IMT by increasing serum Hcy levels.

Related Concept Videos
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:30
Coronary Artery Disease I: Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Hypertension II: Pathophysiology
 01:30
Atherosclerosis I: Introduction