Related Experiment Video
Updated: Jan 6, 2026
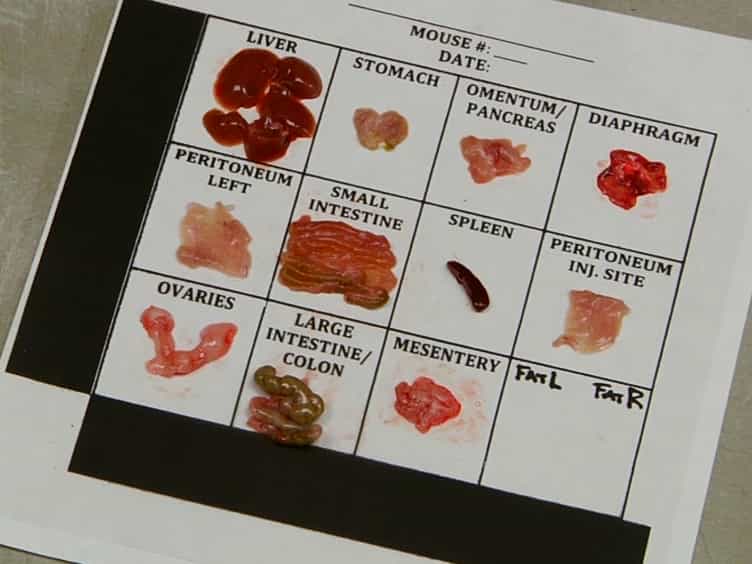
Quantitation of Intra-peritoneal Ovarian Cancer Metastasis
Published on: July 18, 2016
Evaluation of non-completion of intraperitoneal chemotherapy in patients with advanced epithelial ovarian cancer
Laura Moulton Chambers1, Ji Son2, Milena Radeva3
1Division of Gynecologic Oncology, Obstetrics, Gynecology and Women's Health Institute, Cleveland Clinic, Cleveland, OH, USA. moultol@ccf.org.

Objective:
To identify factors associated with non-completion of intraperitoneal with intravenous chemotherapy [IP/IV] in women with epithelial ovarian cancer (EOC).
Methods:
This was an Institutional Review Board approved, retrospective cohort study in women with stage III EOC following optimal cytoreductive surgery (CRS) (<1 cm) followed by IP/IV chemotherapy from 2000-2016. Demographic, surgical, and oncologic variables were collected. Pearson χ² test and 2 sample t-test evaluated for variables associated with IP/IV chemotherapy completion. Kaplan-Meier survival analysis was performed for progression-free survival (PFS) and overall survival (OS).
Results:
Of 96 women, 71.9% (n=69) completed 6 cycles of IP/IV chemotherapy. The majority had high grade serous histology (n=82; 85.4%) and stage IIIC disease (n=83; 86.5%). Common reasons for IP/IV chemotherapy discontinuation were grade 3-4 gastrointestinal (n=10; 37.0%), neurologic (n=6; 22.2%), hematologic (n=3; 11.1%), renal toxicities (n=3; 11.1%) and port infections (n=3; 11.1%). Incidence of IP port complications was 20.8% (n=20). Port complications (48.0% vs. 11.6%; p<0.001) and hospitalization during chemotherapy (29.6% vs. 2.9%; p<0.001) were more frequent in patients who discontinued IP/IV chemotherapy. Patients who completed IP/IV chemotherapy had higher rates of home discharge following CRS (92.2% vs. 72.0%; p<0.01) and lower Eastern Cooperative Oncology Group (ECOG) score (0 vs. 1.0; p=0.04). There was no significant difference in PFS (p=0.51) nor OS (p=0.38) between the cohorts.
Conclusion:
In this series, the rate of IP/IV chemotherapy completion is high. Non-home discharge and higher ECOG status following CRS are associated with IP/IV chemotherapy non-completion and should be considered in treatment planning.

