Related Experiment Video
Updated: Jan 6, 2026
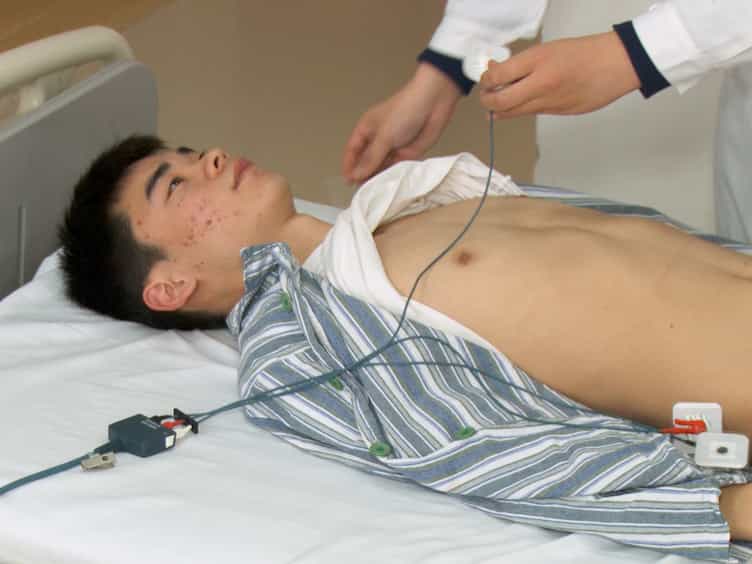
Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Carotid arterial stiffness is increased and related to left ventricular function in patients with hypertrophic
Monica Roşca1, Leonard Mandeş1, Daniela Ciupercă1
1University of Medicine and Pharmacy "Carol Davila", Euroecolab, Emergency Institute of Cardiovascular Diseases "Prof. Dr. C. C. Iliescu", Şos. Fundeni 258, Sector 2, 022328 Bucharest, Romania.

Insights
Arterial stiffness is elevated in hypertrophic cardiomyopathy patients, irrespective of cardiovascular risk factors. This increased arterial stiffness is linked to left ventricular filling pressures and may indicate a more severe disease phenotype.
Area of Science:
- Cardiovascular Medicine
- Biomedical Engineering
- Clinical Physiology
Background:
- Hypertrophic cardiomyopathy (HCM) is a complex cardiac condition.
- Arterial stiffness is a known cardiovascular risk factor.
- The relationship between arterial stiffness and left ventricular function in HCM requires further investigation.
Purpose of the Study:
- To evaluate carotid mechanical properties in patients with HCM.
- To determine the association between arterial stiffness and left ventricular function in HCM.
- To assess if cardiovascular risk factors influence arterial stiffness in HCM.
Main Methods:
- Prospective enrollment of 71 HCM patients and 25 controls.
- Division of HCM patients based on cardiovascular risk factors.
- Comprehensive echocardiography and echo-tracking for carotid arterial stiffness measurements (β index, pressure-strain elastic modulus, arterial compliance, pulse wave velocity).
Main Results:
- HCM patients without risk factors showed significantly higher carotid arterial stiffness (β index, pulse wave velocity, pressure-strain elastic modulus) compared to controls.
- Increased carotid β index was independently correlated with the presence of HCM.
- Arterial stiffness parameters correlated with age, gender, hypertension, hypercholesterolemia, and E/e' ratio in HCM patients.
Conclusions:
- Arterial stiffness is increased in HCM patients, independent of age or cardiovascular risk factors.
- Carotid artery stiffness is independently related to left ventricular filling pressure (E/e' ratio).
- Increased arterial stiffness may serve as a marker for a more severe HCM phenotype.
Aims:
To assess the carotid mechanical properties in patients with hypertrophic cardiomyopathy and the relation between arterial stiffness and left ventricular function in this setting.
Methods And Results:
We have prospectively enrolled 71 patients (52 ± 16 years, 34 men) with hypertrophic cardiomyopathy, divided into two groups depending on the presence (46 patients) or absence (25 patients) of cardiovascular risk factors associated with increased arterial stiffness. Twenty-five normal subjects similar by age and gender with hypertrophic cardiomyopathy patients without risk factors formed the control group. A comprehensive echocardiography was performed in all subjects. Carotid arterial stiffness index (β index), pressure-strain elastic modulus, arterial compliance, and pulse wave velocity were also obtained using an echo-tracking system. β index, pulse wave velocity, and pressure-strain elastic modulus were significantly higher in hypertrophic cardiomyopathy patients without risk factors compared to controls. After linear regression analysis, the increase in carotid β index was independently correlated with the presence of hypertrophic cardiomyopathy [beta = 0.49, 95% confidence interval (CI) = 1.04-3.02; P < 0.001]. In the entire hypertrophic cardiomyopathy population arterial stiffness parameters correlated with age, gender, hypertension degree, presence of hypercholesterolaemia, and the E/e' ratio. In multivariable analysis, β index (beta = 0.36, 95% CI = 0.32-1.25; P = 0.001), global left ventricular longitudinal strain, and the presence of left ventricular outflow tract obstruction were independently correlated with the E/e' ratio.
Conclusion:
In patients with hypertrophic cardiomyopathy arterial stiffness is increased independently of age or presence of cardiovascular risk factors. Carotid artery stiffness is independently related to left ventricular filling pressure, increased arterial stiffness representing a possible marker of a more severe phenotype.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:30
Coronary Artery Disease I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests