Related Experiment Video
Updated: Jan 6, 2026

Chemical Inactivation of the E3 Ubiquitin Ligase Cereblon by Pomalidomide-based Homo-PROTACs
Published on: May 15, 2019
Lenalidomide-based induction and maintenance in elderly newly diagnosed multiple myeloma patients: updated results of
Sara Bringhen1, Mattia D'Agostino2, Laura Paris3
1Myeloma Unit, Division of Hematology, University of Torino, Azienda Ospedaliero-Universitaria Città della Salute e della Scienza di Torino, Torino, Italy sarabringhen@yahoo.com.

Abstract:
n the EMN01 trial, the addition of an alkylator (melphalan or cyclophosphamide) to lenalidomide-steroid induction therapy was prospectively evaluated in transplant-ineligible patients with multiple myeloma. After induction, patients were randomly assigned to maintenance treatment with lenalidomide alone or with prednisone continuously. The analysis presented here (median follow-up of 71 months) is focused on maintenance treatment and on subgroup analyses defined according to the International Myeloma Working Group Frailty Score. Of the 654 evaluable patients, 217 were in the lenalidomide-dexamethasone arm, 217 in the melphalan-prednisone-lenalidomide arm and 220 in the cyclophosphamide-prednisone-lenalidomide arm. With regards to the Frailty Score, 284 (43%) patients were fit, 205 (31%) were intermediate-fit and 165 (25%) were frail. After induction, 402 patients were eligible for maintenance therapy (lenalidomide arm, n=204; lenalidomide-prednisone arm, n=198). After a median duration of maintenance of 22.0 months, progression-free survival from the start of maintenance was 22.2 months with lenalidomide-prednisone vs 18.6 months with lenalidomide (hazard ratio 0.85, P=0.14), with no differences across frailty subgroups. The most frequent grade ≥3 toxicity was neutropenia (10% of lenalidomide-prednisone and 21% of lenalidomide patients; P=0.001). Grade ≥3 non-hematologic adverse events were rare (<15%). In fit patients, melphalan-prednisone-lenalidomide significantly prolonged progression-free survival compared to cyclophosphamide-prednisone-lenalidomide (hazard ratio 0.72, P=0.05) and lenalidomide-dexamethasone (hazard ratio 0.72, P=0.04). Likewise, a trend towards a better overall survival was noted for patients treated with melphalan-prednisone-lenalidomide or cyclophosphamide-prednisone-lenalidomide, as compared to lenalidomide-dexamethasone. No differences were observed in intermediate-fit and frail patients. This analysis showed positive outcomes of maintenance with lenalidomide-based regimens, with a good safety profile. For the first time, we showed that fit patients benefit from a full-dose triplet regimen, while intermediate-fit and frail patients benefit from gentler regimens. ClinicalTrials.gov registration number: NCT01093196.
More Related Videos
 07:24
Repression of Multiple Myeloma Cell Growth In Vivo by Single-wall Carbon Nanotube SWCNT-delivered MALAT1 Antisense Oligos
Published on: December 13, 2018
 09:57
Comprehensive Protocol to Sample and Process Bone Marrow for Measuring Measurable Residual Disease and Leukemic Stem Cells in Acute Myeloid Leukemia
Published on: March 5, 2018
Related Concept Videos
 01:15
Drug Dosing: Geriatric Patients
 02:56
Treatment Resistant Cancers
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:24
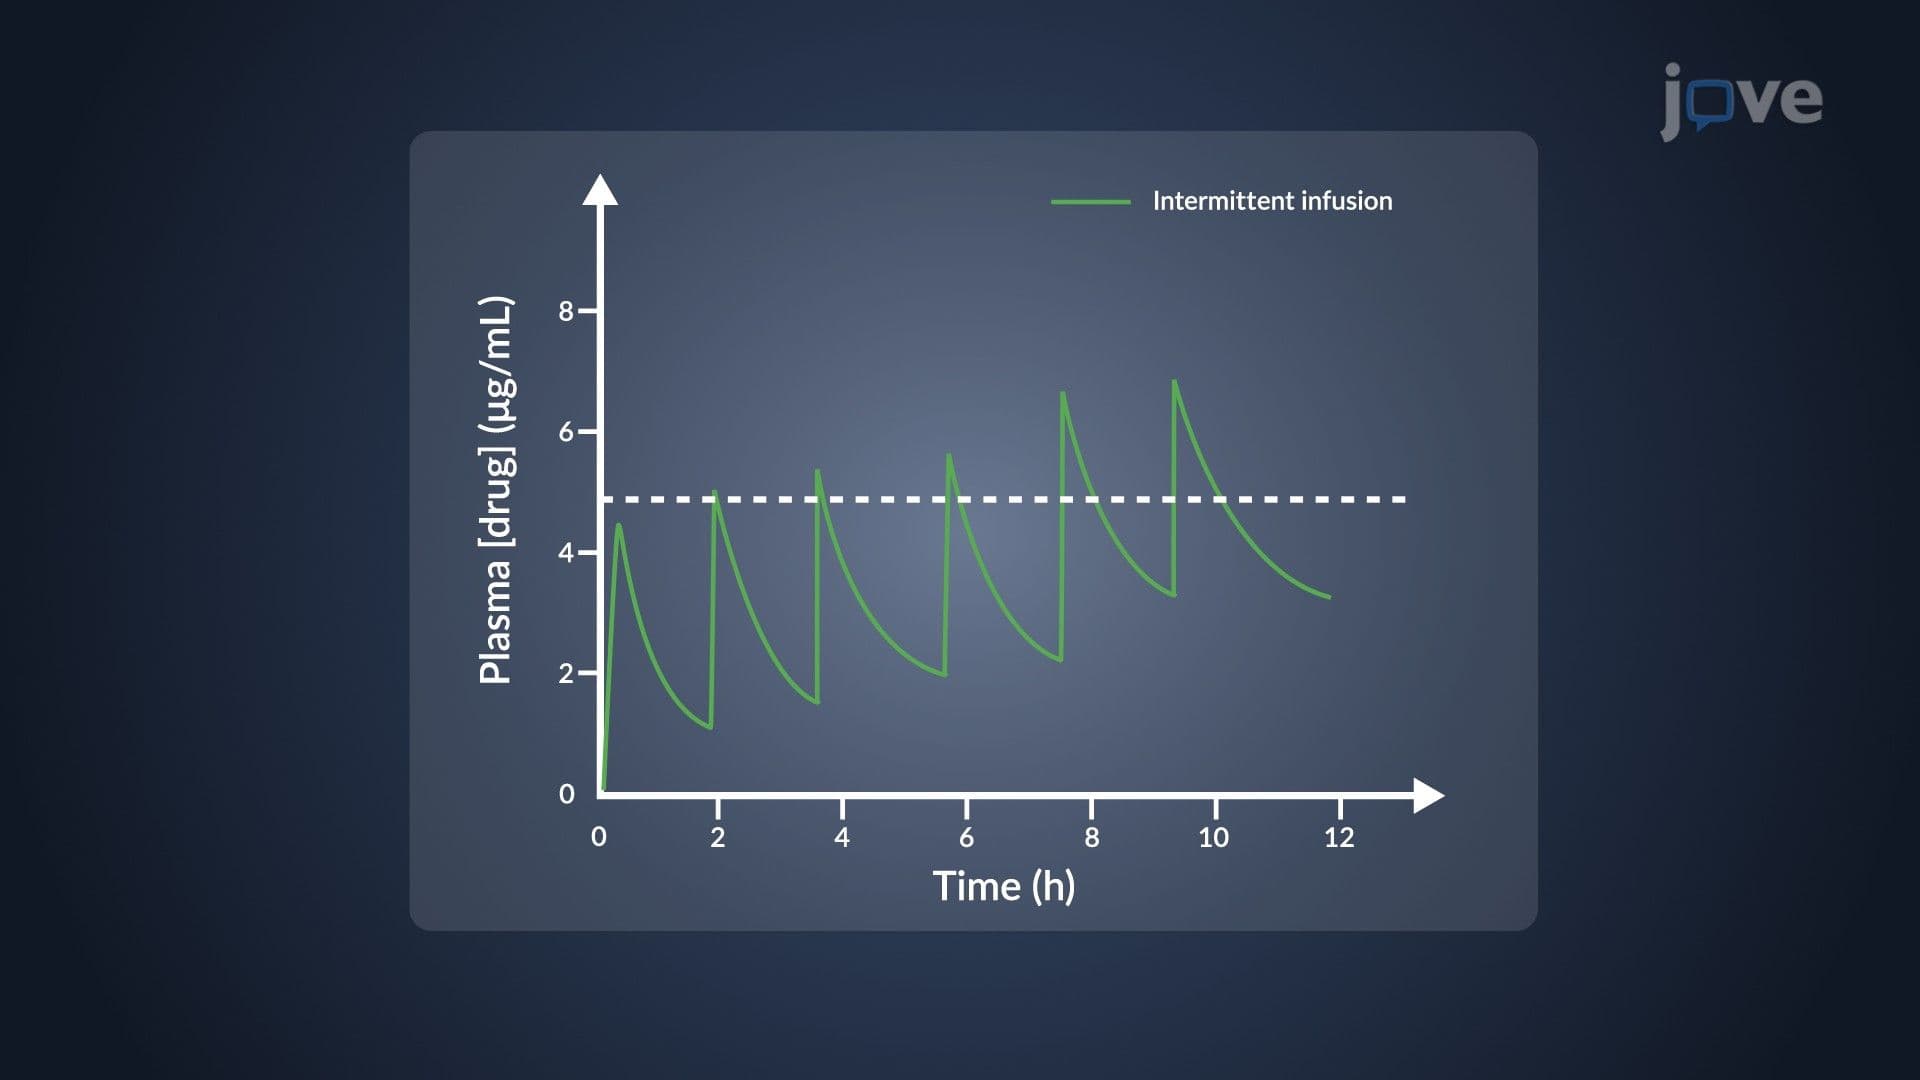
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...