Related Experiment Video
Updated: Jan 5, 2026
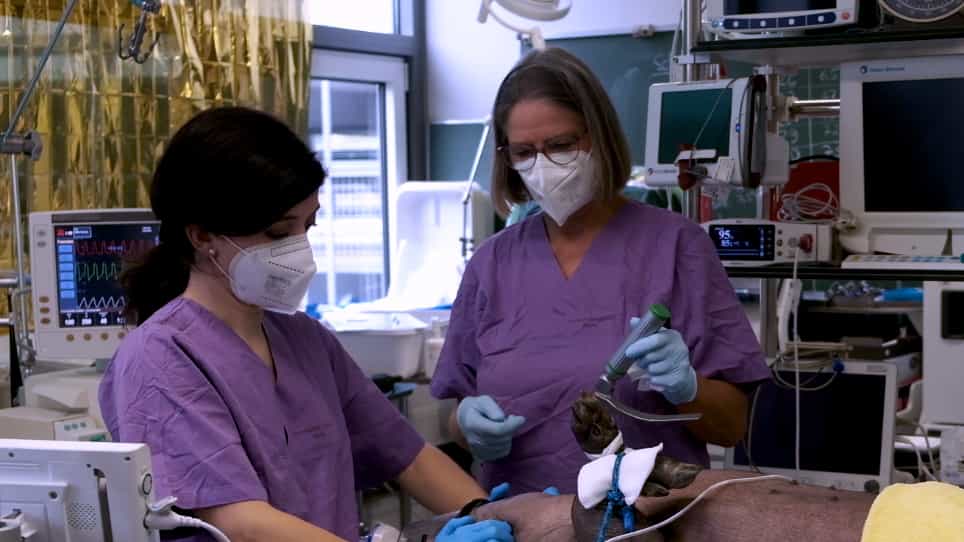
Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Use of a train-of-four ratio of 0.95 versus 0.9 for tracheal extubation: an exploratory analysis of POPULAR data
Manfred Blobner1, Jennifer M Hunter2, Claude Meistelman3
1Department of Anaesthesiology and Intensive Care Medicine, School of Medicine, Technical University of Munich, Munich, Germany.

Background:
The prospective observational European multicentre cohort study (POPULAR) of postoperative pulmonary complications (NCT01865513) did not demonstrate that adherence to the recommended train-of-four ratio (TOFR) of 0.9 before extubation was associated with better pulmonary outcomes from the first postoperative day up to hospital discharge. We re-analysed the POPULAR data as to whether there existed a better threshold for TOFR recovery before extubation to reduce postoperative pulmonary complications in patients who had quantitative neuromuscular monitoring (87% acceleromyography).
Methods:
To identify the optimal TOFR, the complete case cohort of patients with quantitative neuromuscular monitoring (n=3150) was split into several pairs of sub-cohorts related to TOFR values from 0.86 to 0.96; values of 0.97 and higher could not be used as the sub-cohorts were too small. The optimal TOFR was considered to have the lowest P-value from multivariate logistic regression calculated for each of the TOFR values. Data are presented as adjusted absolute risk reduction or median difference with 95% confidence interval.
Results:
Extubating patients with TOFR >0.95 rather than >0.9 reduced the adjusted risk of postoperative pulmonary complications by 3.5% (0.7-6.0%) from that reported in POPULAR (11.3%). Increasing the recommended TOFR from 0.9 to 0.95 reduced the adjusted risk by 4.9% (1.2-8.5%). Sub-cohorts resulting from 1:1 propensity score matching revealed that sugammadex had been given in higher doses by 0.30 (0.13-0.48) mg kg-1 in the sub-cohort with TOFR > 0.95.
Conclusions:
A post hoc analysis of patients receiving quantitative monitoring of neuromuscular function suggests that postoperative pulmonary complications are reduced for TOFR > 0.95 before tracheal extubation compared with TOFR > 0.9.
Trial Registration Number:
NCT01865513.

Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...