Related Experiment Video
Updated: Jan 5, 2026
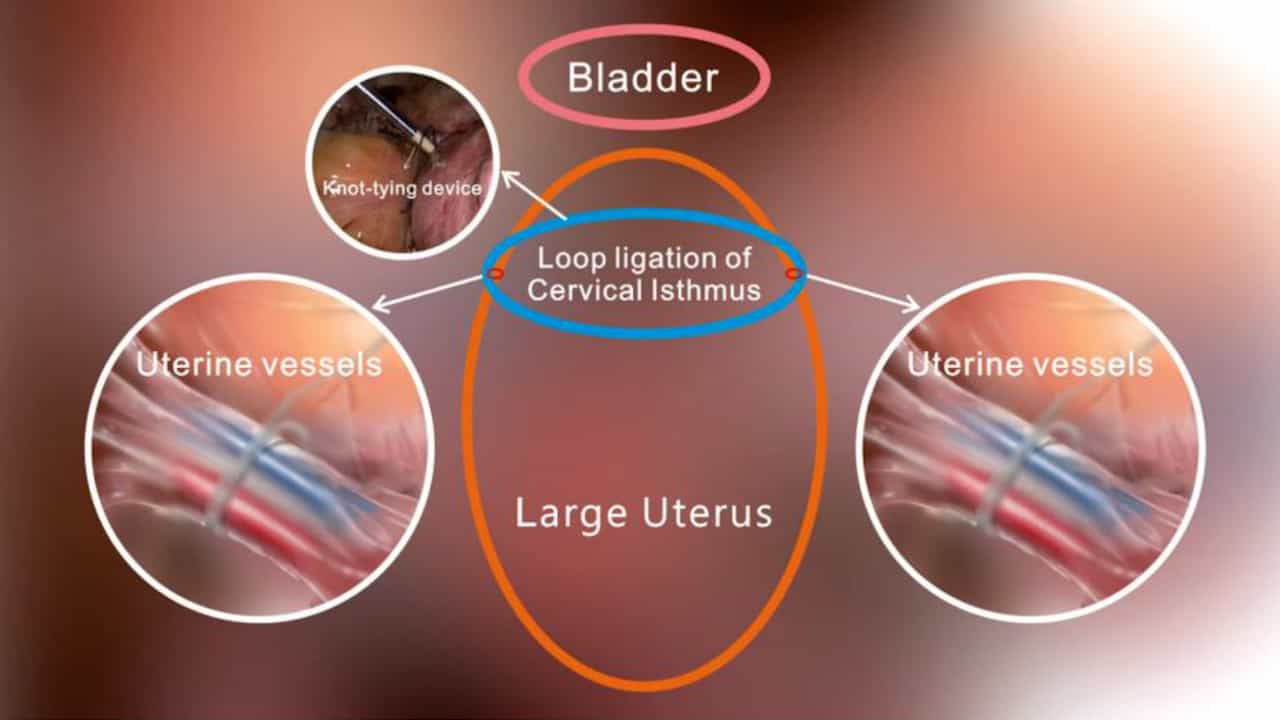

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
A Comparison of Hysterectomies for Bleeding With Hysterectomies for Pain
Bradley M Turner1,2, Stewart F Cramer2,3, Debra S Heller4
1Highland Hospital, Rochester, NY, USA.

Objectives. We recently suggested that increased intramural pressure may often explain pain and/or bleeding. Hysterectomies for bleeding tend to have outward bulges and endometrial vascular ectasia, while hysterectomies for pain tend to have deflection of pressure inward by subserosal ridges, which promote inner myometrial elastosis (IME). Study design. We analyzed causes of increased intramural pressure in 58 hysterectomies for pain and/or bleeding, excluding clinically fibroid uteri and prolapsed uteri. Postfixation photographs were used to avoid missing grossly obvious myometrial hyperplasia (MMH). Results. The most common cause of increased intramural pressure was grossly obvious MMH in 40/58 cases (69%). Other causes included clinically occult myomas (3 cases), adenomyosis (6 cases), and multifactorial causes (7 cases). Hysterectomies for bleeding weighed more than hysterectomies for pain (P = .035). Hysterectomies for pain had more IME than hysterectomies for bleeding (P = .029). Conclusions. When subserosal ridges deflect pressure inward, bulky MMH may cause pelvic pain and IME, but when they do not, bulkier MMH in heavier uteri may lead to both outward bulges and abnormal bleeding from endometrial vascular ectasia.
Objectives. We recently suggested that increased intramural pressure may often explain pain and/or bleeding. Hysterectomies for bleeding tend to have outward bulges and endometrial vascular ectasia, while hysterectomies for pain tend to have deflection of pressure inward by subserosal ridges, which promote inner myometrial elastosis (IME). Study design. We analyzed causes of increased intramural pressure in 58 hysterectomies for pain and/or bleeding, excluding clinically fibroid uteri and prolapsed uteri. Postfixation photographs were used to avoid missing grossly obvious myometrial hyperplasia (MMH). Results. The most common cause of increased intramural pressure was grossly obvious MMH in 40/58 cases (69%). Other causes included clinically occult myomas (3 cases), adenomyosis (6 cases), and multifactorial causes (7 cases). Hysterectomies for bleeding weighed more than hysterectomies for pain (P = .035). Hysterectomies for pain had more IME than hysterectomies for bleeding (P = .029). Conclusions. When subserosal ridges deflect pressure inward, bulky MMH may cause pelvic pain and IME, but when they do not, bulkier MMH in heavier uteri may lead to both outward bulges and abnormal bleeding from endometrial vascular ectasia.
More Related Videos
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
 03:01
Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024