Related Experiment Video
Updated: Jan 5, 2026
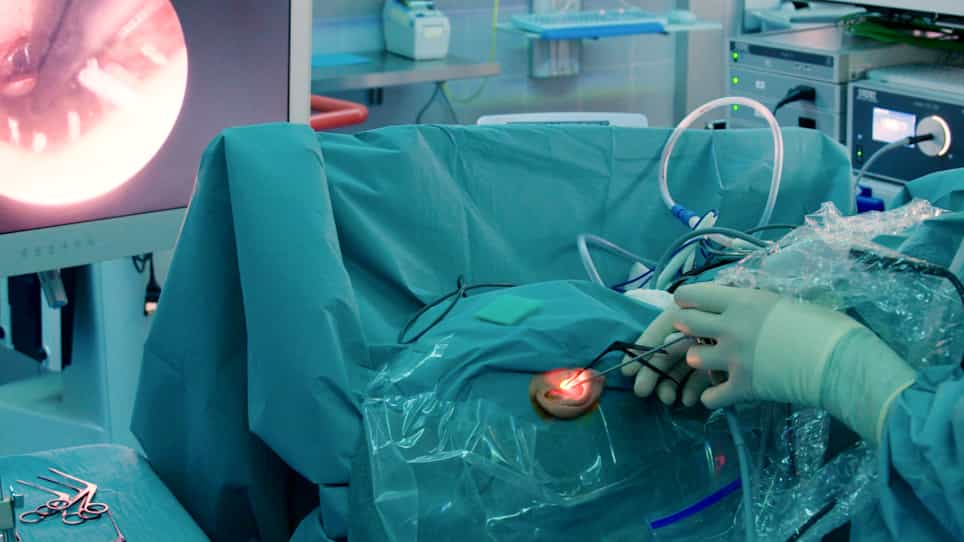

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Chronic Draining Ear and Cholesteatoma Recidivism: A Retrospection from Clinical, Imaging, and Surgical Perspectives
Saumik Das1, Mainak Dutta1, Tanaya Panja2
1Department of Otorhinolaryngology and Head-Neck Surgery, Medical College and Hospital, Kolkata, India.

Objective:
To evaluate the reasons for persistent draining ear and cholesteatoma recidivism following canal wall down (CWD) tympanomastoidectomy by studying the sensitivity of high-resolution computed tomography (HRCT) scanning in different potential etiologies, corroborating through appropriate surgical intervention, and thereby, to suggest proper preventive measures.
Methods:
In this observational study, 32 chronic, refractory draining ears were subjected to revision surgery following a radical or a modified radical mastoidectomy. Besides disease (cholesteatoma/granulations) eradication, pitfalls of the primary surgeries were addressed. Data were interpreted for studying the epidemiologic profile, the clinical presentation at recurrence, the type of primary surgery, the sites of recidivism, the probable causes, and the best possible management at revision.
Results:
Of the 32 patients/ears, 23 had residual/recurrent cholesteatoma. Major reasons were inadequate disease clearance, contracted/inadequate conchomeatoplasty, no cavity obliteration, and inappropriate bone work. HRCT predicted persistent bridge and lateral semicircular canal dehiscence with 100%, and ossicular integrity and bony overhang with >80% sensitivity. Sinus tympani and oval window niche were the commonest sites of recurrence. At revision, radical/modified radical mastoidectomies were associated with cavity obliteration and appropriate revision of conchomeatoplasty in 28 patients.
Conclusion:
Recurrence of cholesteatoma/granulations is an important cause for chronic drainage from post-CWD cavities. Revision surgery explores the surgical pitfalls, and ensures clearance of disease from hidden areas, adequate bone work, and optimum conchomeatoplasty following cavity obliteration to provide a safe, dry ear with hearing improvement whenever feasible.
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...