Related Experiment Video
Updated: Jan 5, 2026
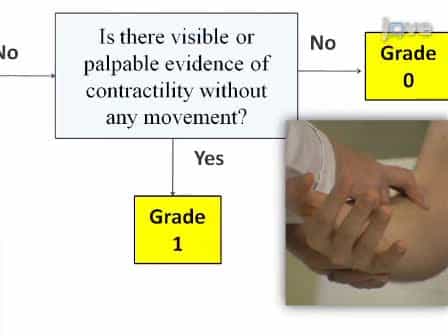

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
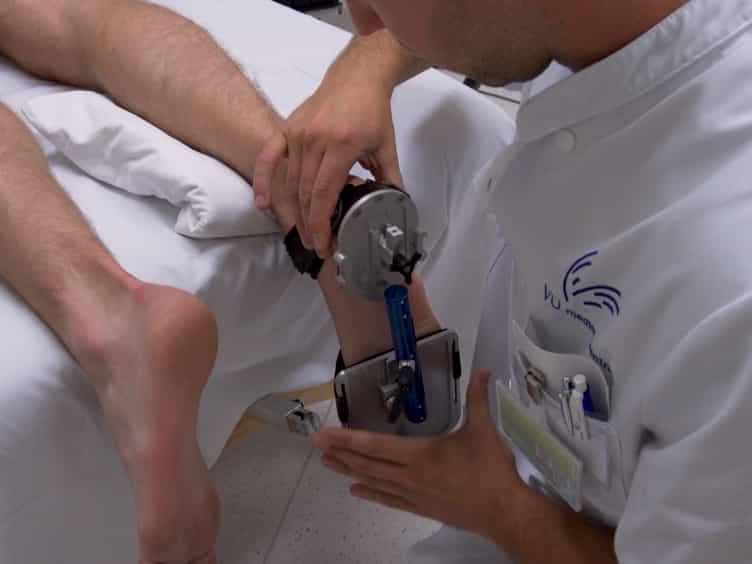
Relationship Between Respiratory Muscle Strength, Handgrip Strength, and Muscle Mass in Hospitalized Patients
Sarah J Peterson1, Jessica Park1, Hillary K Zellner2
1Department of Clinical Nutrition, College of Health Sciences, Rush University/Rush University Medical Center, Chicago, Illinois, USA.

Background:
Minimal information is available to validate measurement of respiratory muscle strength (RMS) in the clinical setting. The purpose of this study was to determine the correlation between maximal inspiratory pressure (MIP), maximal expiratory pressure (MEP), and sniff nasal inspiratory pressure (SNIP) with handgrip strength (HGS) and cross sectional muscle area obtained via diagnostic abdominal computed tomography (CT).
Materials And Methods:
Measures of MIP, MEP, SNIP, and HGS were obtained from individuals that participated in a previously published study; individuals who had an abdominal CT completed with (±)7 days of obtaining RMS measures were included. Both RMS and HGS were measured within 48-72 hours of admission; for RMS, the highest absolute (cm H2 O) and percent predicted values were recorded, and the average of 3 HGS measurements (kg) was documented. Cross-sectional muscle area (cm2 ) at the third lumbar region was recorded. Spearman's correlation coefficient was used to assess the relationship between variables.
Results:
A total of 35 participants were included. HGS was correlated to absolute MIP (rs = 0.62, rs = 0.61), MEP (rs = 0.74, rs = 0.73), and SNIP (rs = 0.58, rs = 0.54) for males and females, respectively. Crosss-sectional muscle area was correlated with absolute MIP (rs = 0.66), MEP (rs = 0.58), and SNIP (rs = 0.783) for men and absolute SNIP (rs = 0.56) among women.
Conclusion:
Measures of RMS represent a promising assessment of muscle mass and function among hospitalized patients.

Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: