Related Experiment Video
Updated: Jan 5, 2026

Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
Quantification of Cardiorespiratory Fitness in Children with Obesity
Dharini M Bhammar1,2, Beverley Adams-Huet3, Tony G Babb2
1Department of Kinesiology and Nutrition Sciences, School of Integrated Health Sciences, University of Nevada, Las Vegas, Las Vegas, NV.

Purpose:
Without consideration for the effects of fat mass, there could be an underestimation of cardiorespiratory fitness in children with obesity leading to a clinical diagnosis of deconditioning and resulting in unrealistic training goals and limitation of physical activities. The purpose of this study was to identify methods of quantifying cardiorespiratory fitness that were less influenced by fat mass.
Methods:
Fifty-three children, 27 with obesity (10.9 ± 1.0 yr) and 26 without obesity (11.0 ± 1.0 yr), volunteered for this study. Maximal oxygen uptake, an indicator of cardiorespiratory fitness, was referenced to lean body mass, body mass, and predicted body mass at the 50th and 85th body mass index percentiles.
Results:
Children with obesity carried 18 kg more fat mass and 7 kg more lean body mass compared with children without obesity. Cardiorespiratory fitness based on lean body mass, body mass, and predicted body mass at the 85th percentile was lower in children with obesity compared with children without obesity (P < 0.001). Differences in cardiorespiratory fitness based on predicted body mass at the 50th percentile between children with and without obesity did not reach statistical significance (P = 0.84). Fat mass influenced cardiorespiratory fitness least when referenced to lean body mass or predicted body mass at the 50th percentile (R < 0.26) in contrast to when it was referenced to body mass or predicted body mass at the 85th percentile (R > 0.37).
Conclusion:
Quantifying cardiorespiratory fitness based on lean body mass or predicted body mass at the 50th percentile could be useful for estimating fitness levels in children with obesity.

Related Concept Videos
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:22
Respiratory Volumes and Capacities
 01:26
Respiratory Volumes and Capacities I
 01:15
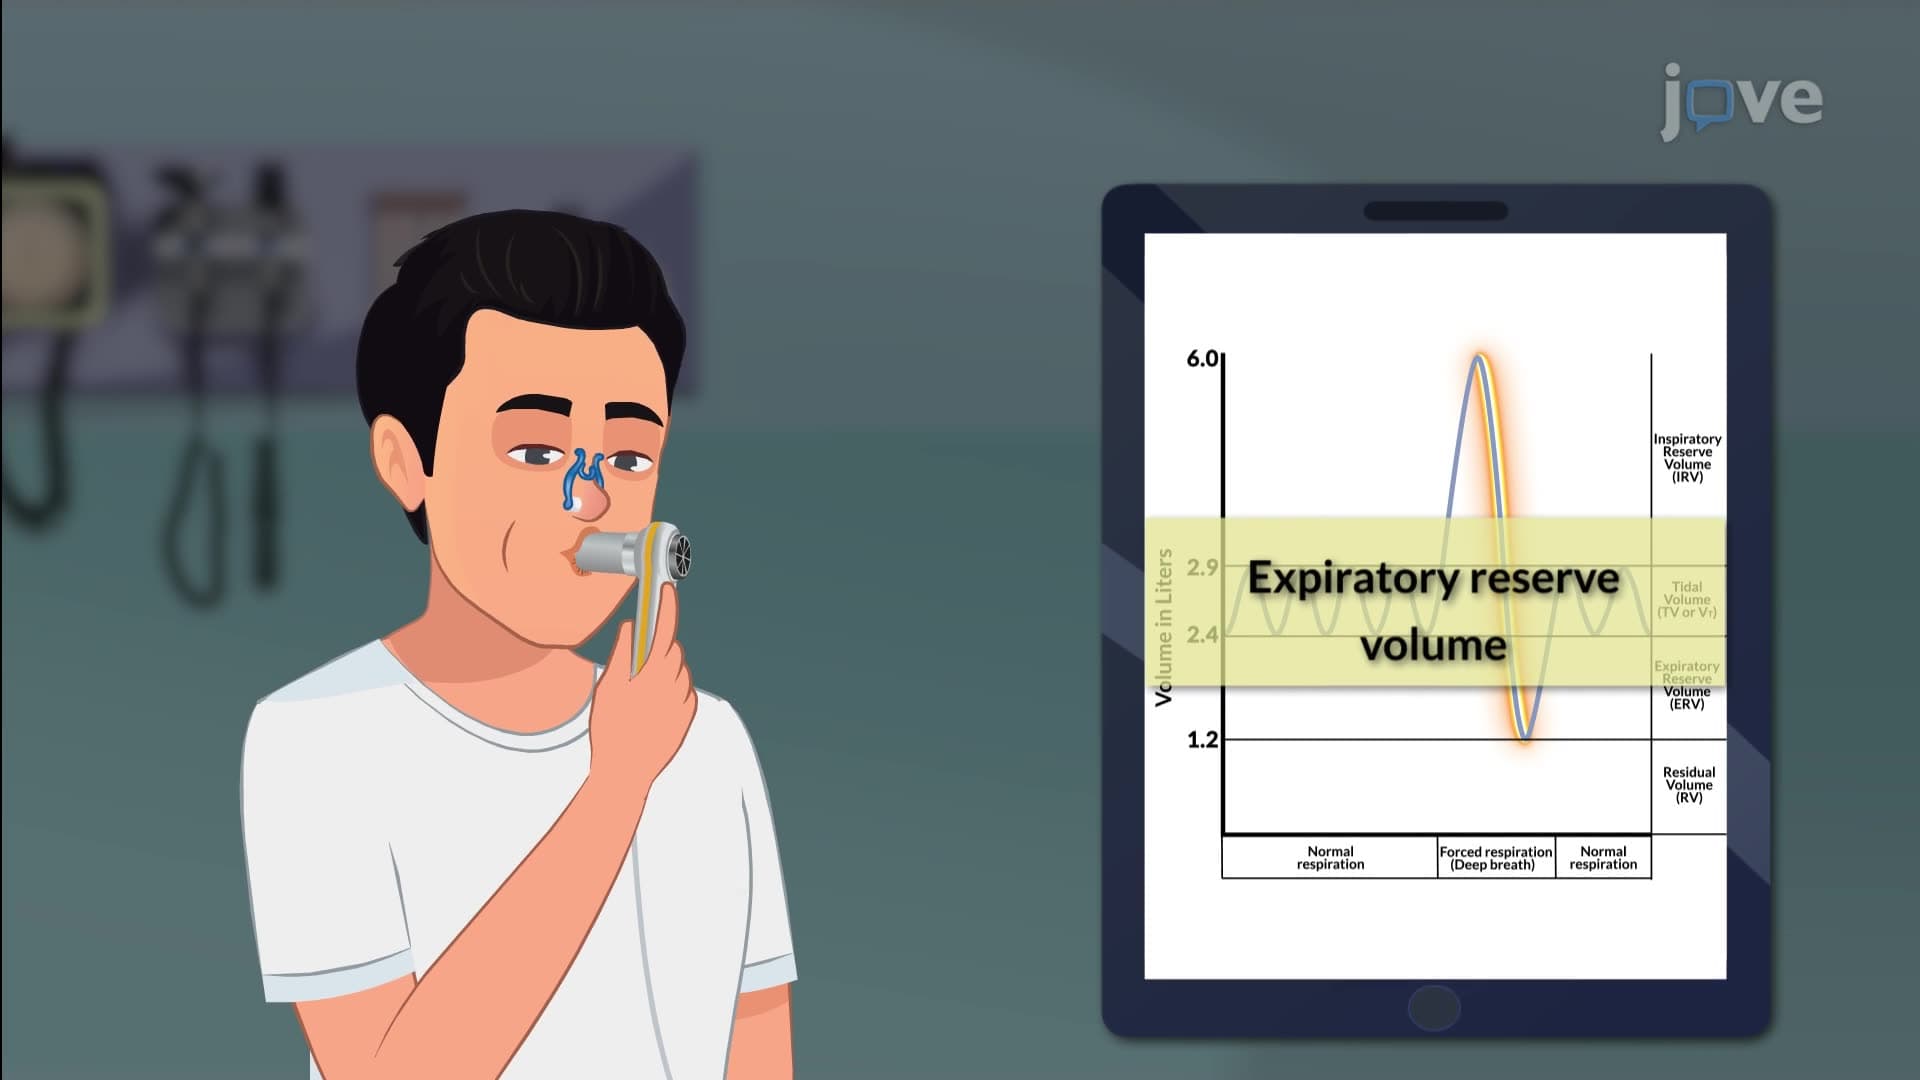
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: