Related Experiment Video
Updated: Jan 5, 2026
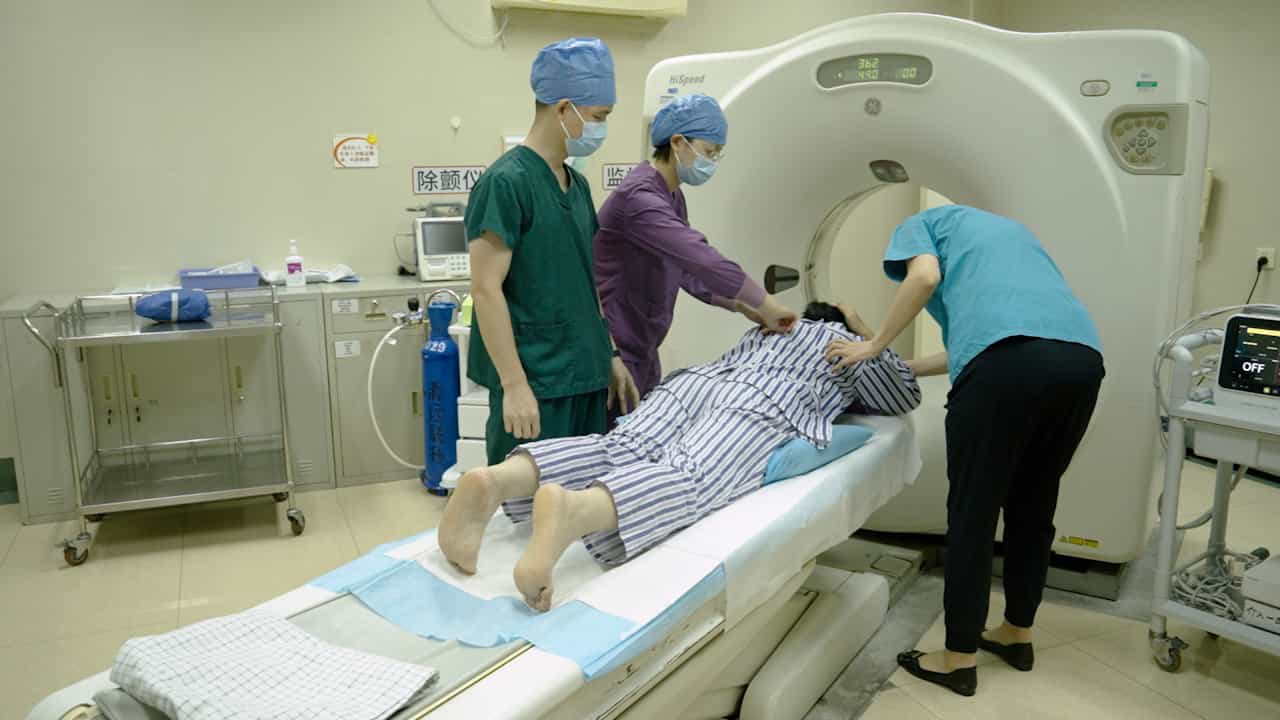

Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Rapid treatment of moderate to severe hypertension using a novel protocol in a single-centre, before and after
Andrew N Jordan1,2, Christine Anning1, Lindsay Wilkes1
1NIHR Exeter Clinical Research Facility, Vascular Medicine, Exeter, UK.

Rapid treatment to target in hypertension may have beneficial effects on long-term outcomes. This has led to a new recommendation in the 2018 European hypertension guidelines for patients with grade II/III hypertension to be treated to target within three months. However, whether it is feasible and safe to quickly manage treatment-naïve grade II/III hypertension to target was unclear. We examined this using a single-centre before and after interventional study, treating newly diagnosed, never-treated, grade II/III hypertensive patients with a daytime average systolic ABP ≥ 150 mmHg to target within 18 weeks. The proportion at office target BP at 18 weeks was determined, together with office and ambulatory BP change from baseline to after the intervention. The protocol was designed to maximise medication adherence, including a low threshold for treatment adaptation. Safety was evaluated through close monitoring of adverse events and protocol discontinuation. Fifty-five participants were enrolled with 54 completing the protocol. 69 ± 12.3% were at office target BP at their final visit, despite a high average starting BP of 175/103 mmHg, as a consequence of significant reductions in both office and ambulatory BP. Of those at office target BP, 51% were above target on ambulatory measurement. Adherence testing demonstrated that 92% of participants were adherent to treatment at their final visit. Therefore we conclude that the accelerated management of treatment-naïve grade II/III hypertension is feasible and safe to implement in routine practice and there is no evidence to suggest it causes harm. Further large-scale randomised studies of rapid, adaptive treatment, including a cost-effectiveness analysis, are required.
Rapid treatment to target in hypertension may have beneficial effects on long-term outcomes. This has led to a new recommendation in the 2018 European hypertension guidelines for patients with grade II/III hypertension to be treated to target within three months. However, whether it is feasible and safe to quickly manage treatment-naïve grade II/III hypertension to target was unclear. We examined this using a single-centre before and after interventional study, treating newly diagnosed, never-treated, grade II/III hypertensive patients with a daytime average systolic ABP ≥ 150 mmHg to target within 18 weeks. The proportion at office target BP at 18 weeks was determined, together with office and ambulatory BP change from baseline to after the intervention. The protocol was designed to maximise medication adherence, including a low threshold for treatment adaptation. Safety was evaluated through close monitoring of adverse events and protocol discontinuation. Fifty-five participants were enrolled with 54 completing the protocol. 69 ± 12.3% were at office target BP at their final visit, despite a high average starting BP of 175/103 mmHg, as a consequence of significant reductions in both office and ambulatory BP. Of those at office target BP, 51% were above target on ambulatory measurement. Adherence testing demonstrated that 92% of participants were adherent to treatment at their final visit. Therefore we conclude that the accelerated management of treatment-naïve grade II/III hypertension is feasible and safe to implement in routine practice and there is no evidence to suggest it causes harm. Further large-scale randomised studies of rapid, adaptive treatment, including a cost-effectiveness analysis, are required.


Related Concept Videos
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Heart Failure V: Medical Management
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors