Related Experiment Video
Updated: Jan 5, 2026


Author Spotlight: Advancing Pediatric Epilepsy Surgery in Children Through Novel Biomarkers and Enhanced Localization
Published on: September 20, 2024
Paroxysmal non-epileptic events in infancy: five cases with typical features
Eszter Nagy1, Katalin Hollody1
1Department of Paediatrics, Medical School, University of Pecs, Hungary.

Insights
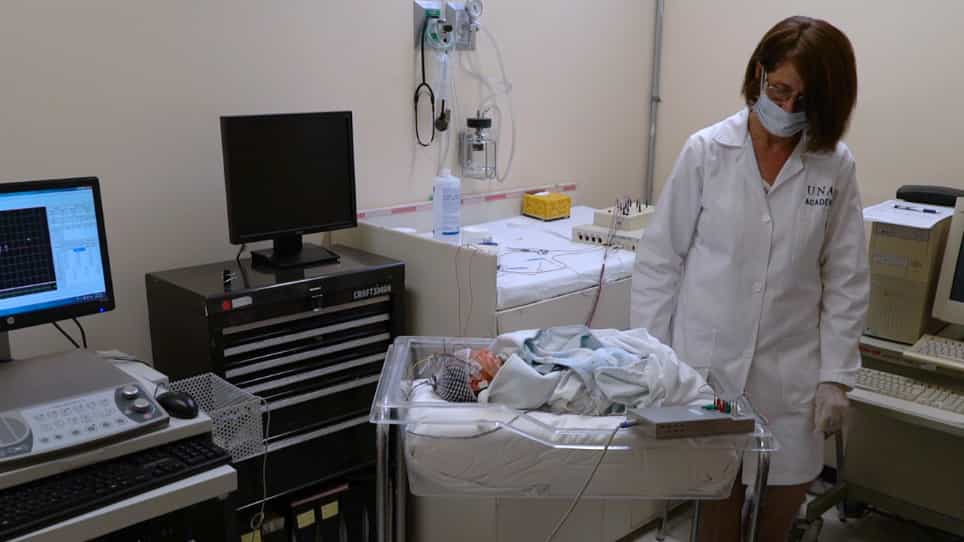
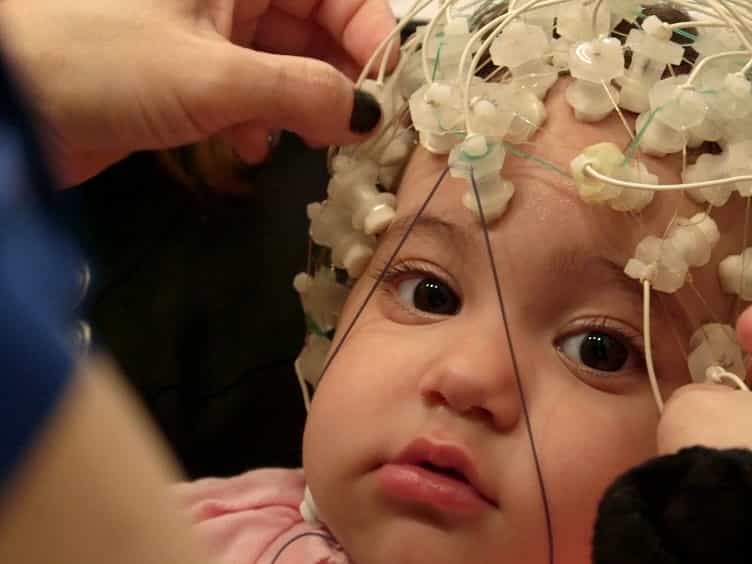
Differentiating childhood epilepsy from non-epileptic events is challenging. A detailed patient history is crucial for accurate diagnosis, potentially avoiding unnecessary investigations like video-electroencephalogram (EEG) examinations.
Area of Science:
- Pediatric Neurology
- Clinical Diagnostics
Background:
- Diagnosing paroxysmal non-epileptic events in infants and toddlers presents significant challenges for pediatricians and child neurologists.
- Parental concern over unusual infant movements often leads to immediate consultation with general practitioners, frequently with a suspicion of epilepsy.
Purpose of the Study:
- To identify the primary reasons for referral of infants and toddlers suspected of having epilepsy.
- To describe the characteristic features of five common non-epileptic paroxysmal events in early childhood using visual aids.
- To emphasize the diagnostic value of detailed patient history in distinguishing epileptic from non-epileptic events.
Main Methods:
- Retrospective review of five infants/toddlers (aged 1-30 months) initially referred with suspected epilepsy.
- Analysis of clinical presentation, focusing on history and observed paroxysmal events.
- Inclusion of images and video sequences to illustrate typical features of non-epileptic events.
Main Results:
- None of the five investigated infants/toddlers were ultimately diagnosed with epilepsy.
- Detailed historical information proved highly significant in differentiating epileptic from non-epileptic paroxysmal events.
- Identified non-epileptic events included benign neonatal sleep myoclonus, jitteriness, shuddering attacks, paroxysmal tonic upgaze, and infantile masturbation.
Conclusions:
- A thorough patient history is a cornerstone in the differential diagnosis of paroxysmal events in early childhood.
- Accurate historical assessment can prevent unnecessary diagnostic procedures, such as video-electroencephalogram (EEG) examinations.
- Video-EEG is reserved for cases where epilepsy remains a strong clinical suspicion.
Abstract:
The differential diagnosis of paroxysmal non-epileptic events in early childhood is one of the most challenging tasks in paediatrics, and may be difficult even for specialized child neurologists. Parents are usually concerned by every unusual movement of their children and consult paediatric general practitioners immediately. We investigated five infants/toddlers (aged 1-30 months) referred by their general practitioners with a suspicion of epilepsy. None of them were ultimately shown to have epilepsy. Our aim was to determine the main reasons for referral and describe, through images and video, the typical features of five non-epileptic paroxysmal events (benign neonatal sleep myoclonus, jitteriness, shuddering attack, paroxysmal tonic upgaze, and infantile masturbation). The review of these events reveals the significance of the circumstances within the history of the patients. A detailed history is of considerable help in the differentiation of epileptic paroxysmal events from non-epileptic events, avoiding unnecessary investigations. Video-EEG examination is necessary only in cases when epilepsy is strongly suspected. [Published with video sequences].
Related Concept Videos
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types:
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...