Related Experiment Video
Updated: Jan 5, 2026
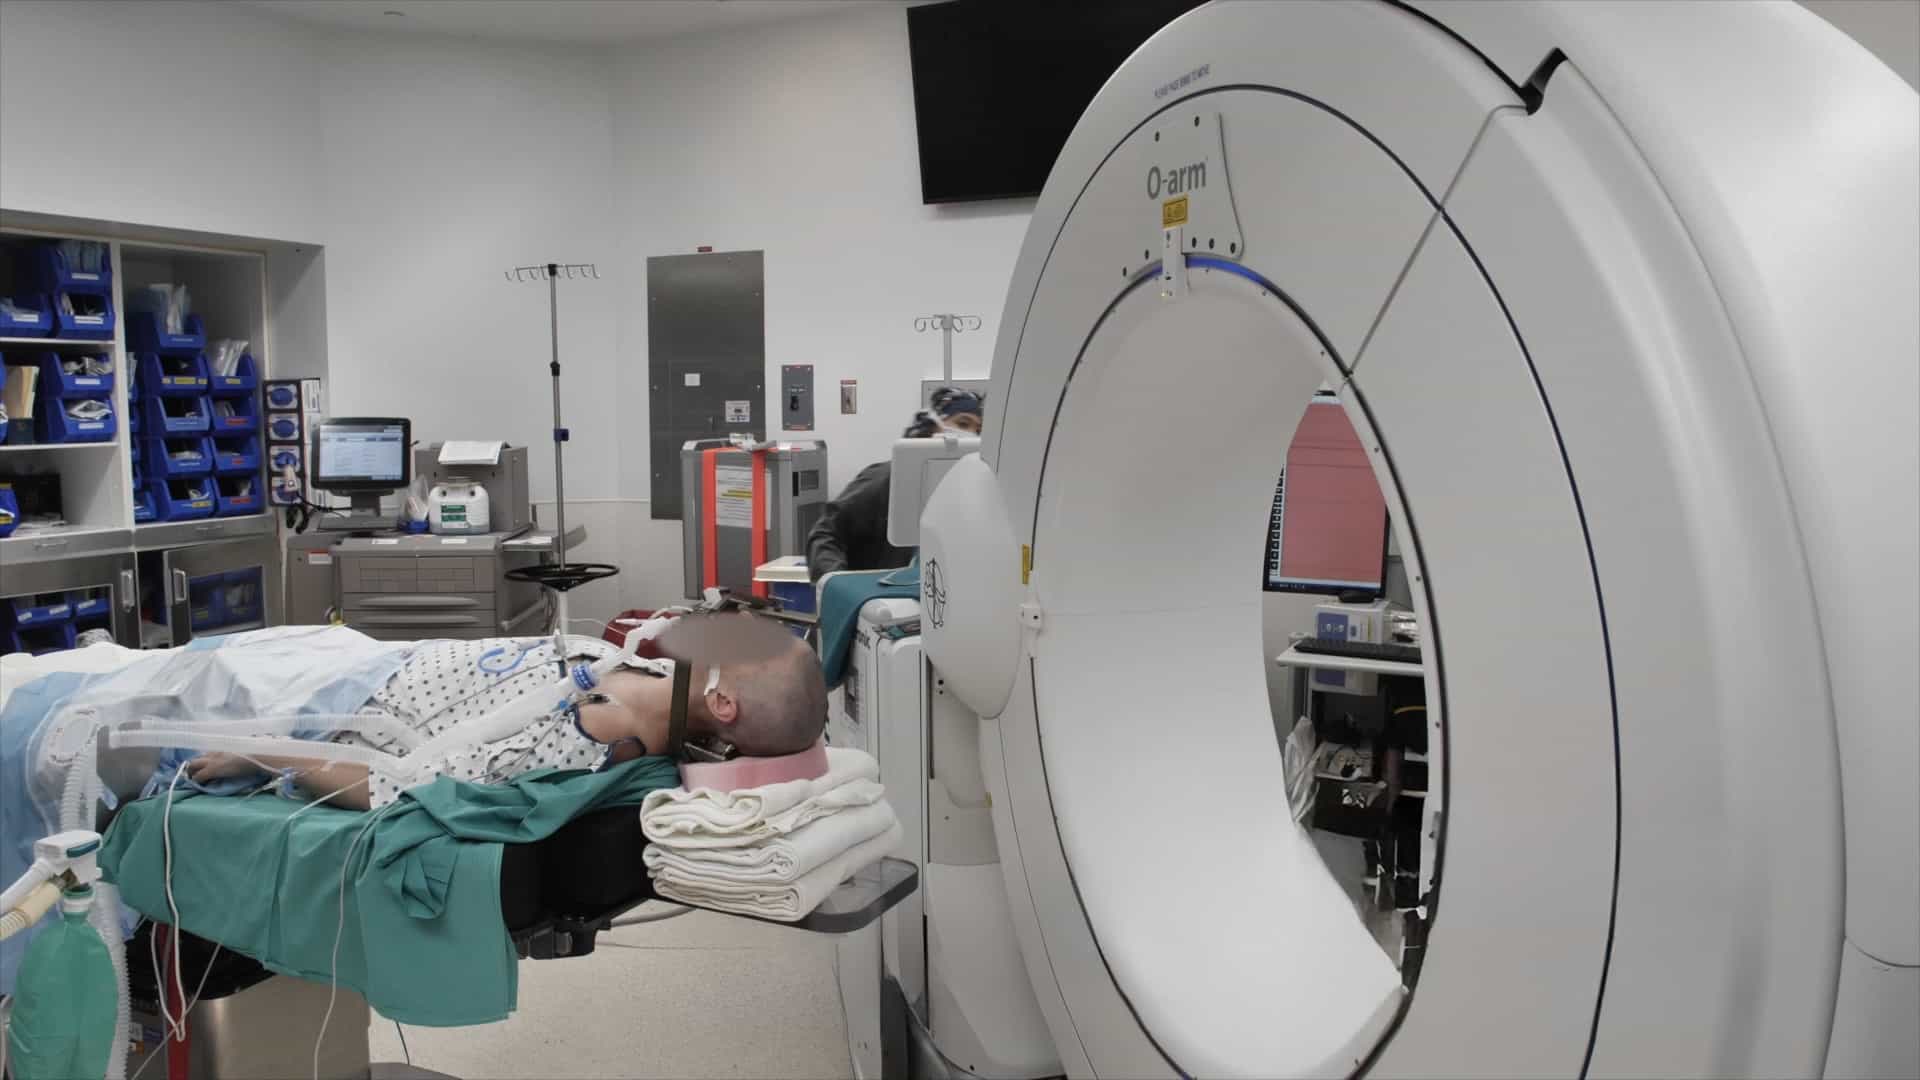

Robotic-Guided Stereoelectroencephalography for Invasive Epilepsy Monitoring
Published on: June 13, 2025
The Effect of Vascular Segmentation Methods on Stereotactic Trajectory Planning for Drug-Resistant Focal Epilepsy: A
Vejay N Vakharia1,2,3,4, Rachel Sparks5, Sjoerd B Vos1,2,3,6
1Department of Clinical and Experimental Epilepsy, UCL Institute of Neurology, University College London, London, United Kingdom.

Background:
Stereotactic neurosurgical procedures carry a risk of intracranial hemorrhage, which may result in significant morbidity and mortality. Vascular imaging is crucial for planning stereotactic procedures to prevent conflicts with intracranial vasculature. There is a wide range of vascular imaging methods used for stereoelectroencephalography (SEEG) trajectory planning. Computer-assisted planning (CAP) improves planning time and trajectory metrics. We aimed to quantify the effect of different vascular imaging protocols on CAP trajectories for SEEG.
Methods:
Ten patients who had undergone SEEG (95 electrodes) following preoperative acquisition of gadolinium-enhanced magnetic resonance imaging (MR + Gad), magnetic resonance angiography and magnetic resonance angiography (MRV + MRA), and digital subtraction catheter angiography (DSA) were identified from a prospectively maintained database. SEEG implantations were planned using CAP using DSA segmentations as the gold standard. Strategies were then recreated using MRV + MRA and MR + Gad to define the "apparent" and "true" risk scores associated with each modality. Vessels of varying diameter were then iteratively removed from the DSA segmentation to identify the size at which all 3 vascular modalities returned the same safety metrics.
Results:
CAP performed using DSA vessel segmentations resulted in significantly lower "true" risk scores and greater minimum distances from vasculature compared with the "true" risk associated with MR + Gad and MRV + MRA. MRV + MRA and MR + Gad returned similar risk scores to DSA when vessels <2 mm and <4 mm were not considered, respectively.
Conclusions:
Significant variability in vascular imaging and trajectory planning practices exist for SEEG. CAP performed with MR + Gad or MRV + MRA alone returns "falsely" lower risk scores compared with DSA. It is unclear whether DSA is oversensitive and thus restricting potential trajectories.
More Related Videos
 09:41
A Pipeline for 3D Multimodality Image Integration and Computer-assisted Planning in Epilepsy Surgery
Published on: May 20, 2016
 04:50
Operative Technique and Nuances for the Stereoelectroencephalographic SEEG Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023