Related Experiment Video
Updated: Jan 5, 2026

Ferritinophagy: Assessing the Selective Degradation of Iron by Autophagy in Human Fibroblasts
Published on: February 23, 2024
Oral Iron Replacement Normalizes Fibroblast Growth Factor 23 in Iron-Deficient Patients With Autosomal Dominant
Erik A Imel1,2, Ziyue Liu3, Melissa Coffman1
1Department of Medicine, Indiana University School of Medicine, Indianapolis, IN, USA.

Abstract:
Autosomal dominant hypophosphatemic rickets (ADHR) is caused by mutations impairing cleavage of fibroblast growth factor 23 (FGF23). FGF23 gene expression increases during iron deficiency. In humans and mice with the ADHR mutation, iron deficiency results in increased intact FGF23 concentrations and hypophosphatemia. We conducted a prospective open label pilot clinical trial of oral iron replacement over 12 months in ADHR patients to test the hypothesis that oral iron administration would normalize FGF23 concentrations. Eligibility criteria included: FGF23 mutation; and either serum iron <50 μg/dL; or serum iron 50 to 100 μg/dL combined with hypophosphatemia and intact FGF23 >30 pg/mL at screening. Key exclusion criteria were kidney disease and pregnancy. Oral iron supplementation started at 65 mg daily and was titrated based on fasting serum iron concentration. The primary outcome was decrease in fasting intact FGF23 by ≥20% from baseline. Six adults (three male, three female) having the FGF23-R176Q mutation were enrolled; five completed the 12-month protocol. At baseline three of five subjects had severely symptomatic hypophosphatemia (phosphorus <2.5 mg/dL) and received calcitriol with or without phosphate concurrent with oral iron during the trial. The primary outcome was met by 4 of 5 (80%) subjects all by month 4, and 5 of 5 had normal intact FGF23 at month 12. Median (minimum, maximum) intact FGF23 concentration decreased from 172 (20, 192) pg/mL at baseline to 47 (17, 78) pg/mL at month 4 and 42 (19, 63) pg/mL at month 12. Median ferritin increased from 18.6 (7.7, 82.5) ng/mL at baseline to 78.0 (49.6, 261.0) ng/mL at month 12. During iron treatment, all three subjects with baseline hypophosphatemia normalized serum phosphorus, had markedly improved symptoms, and were able to discontinue calcitriol and phosphate. Oral iron repletion normalized FGF23 and phosphorus in symptomatic, iron-deficient ADHR subjects. Thus, the standard approach to ADHR should include recognition, treatment, and prevention of iron deficiency. © 2019 American Society for Bone and Mineral Research.


Related Concept Videos
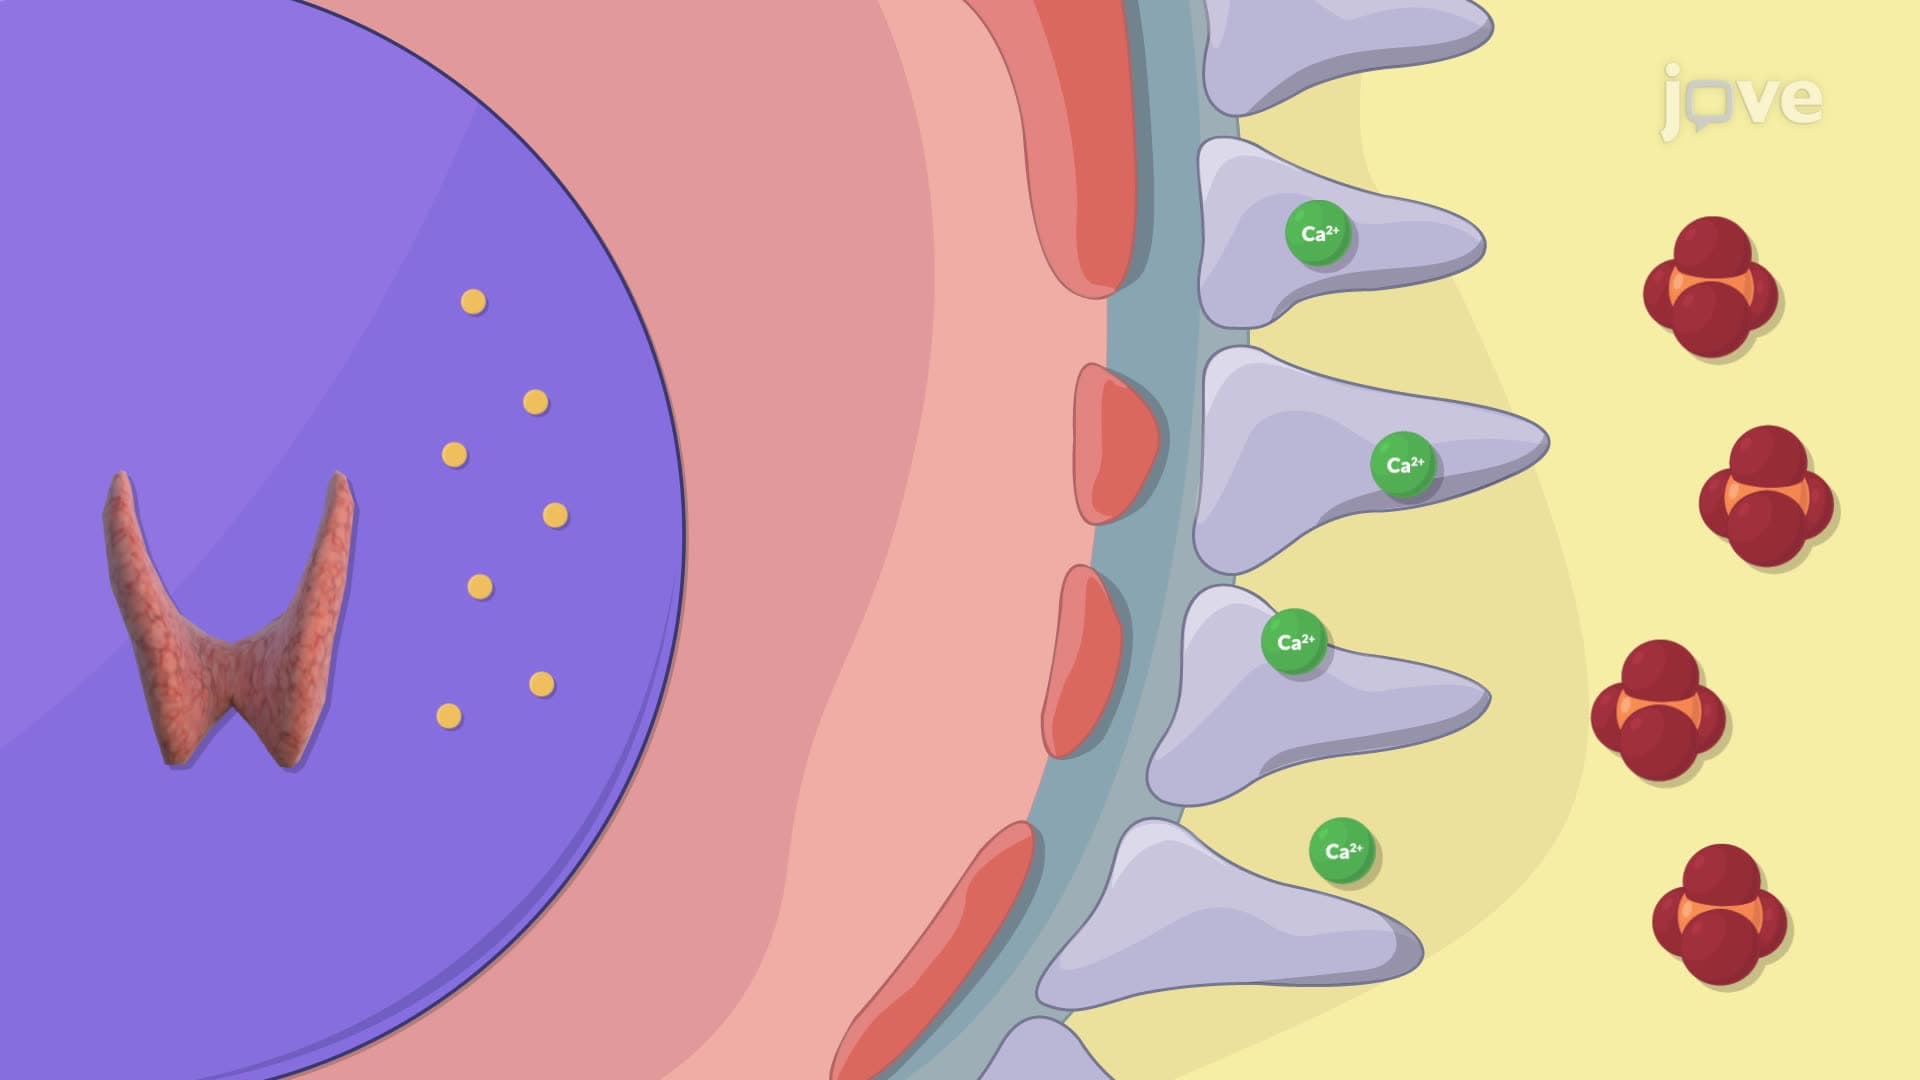 01:27
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily...
 01:28
Role of Hematopoietic Growth Factors
Thrombopoietin (TPO), mainly released by the liver,...
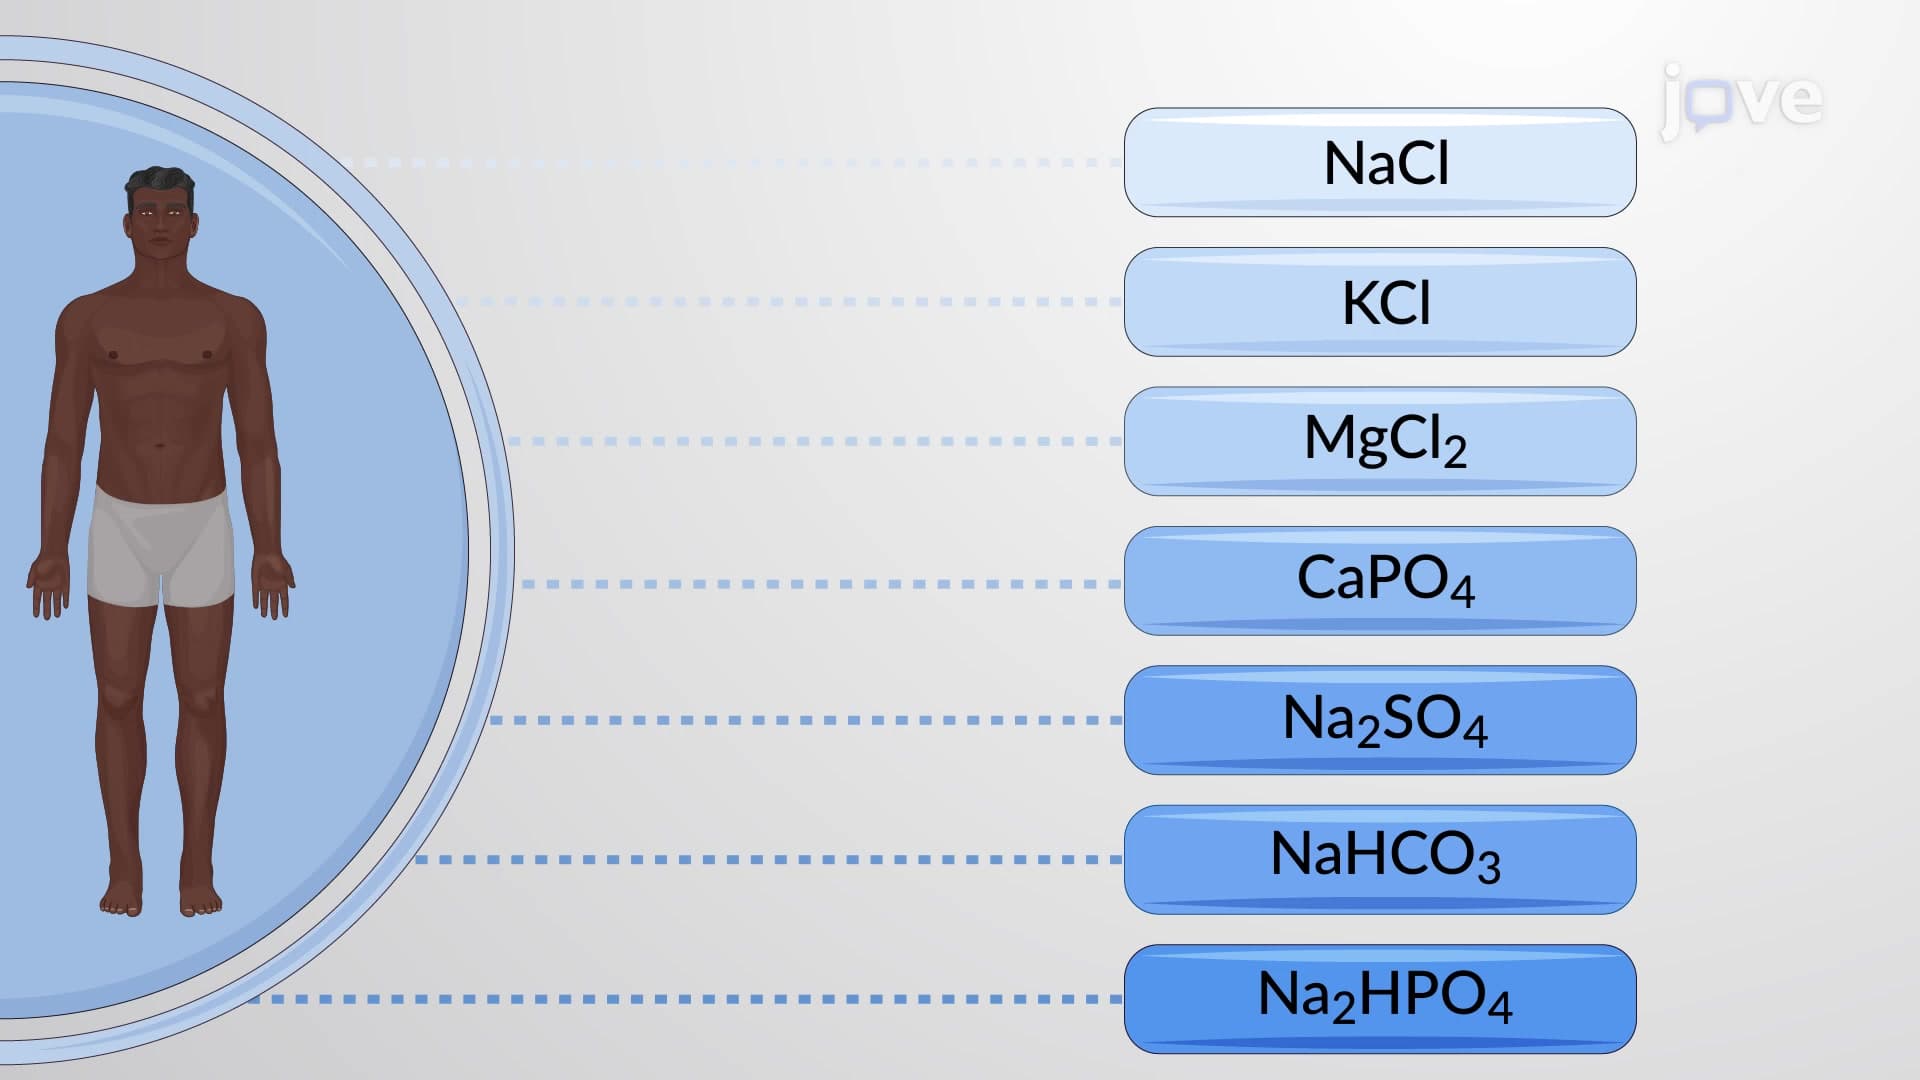 01:33
Introduction to Electrolytes
Role of Sodium
One...
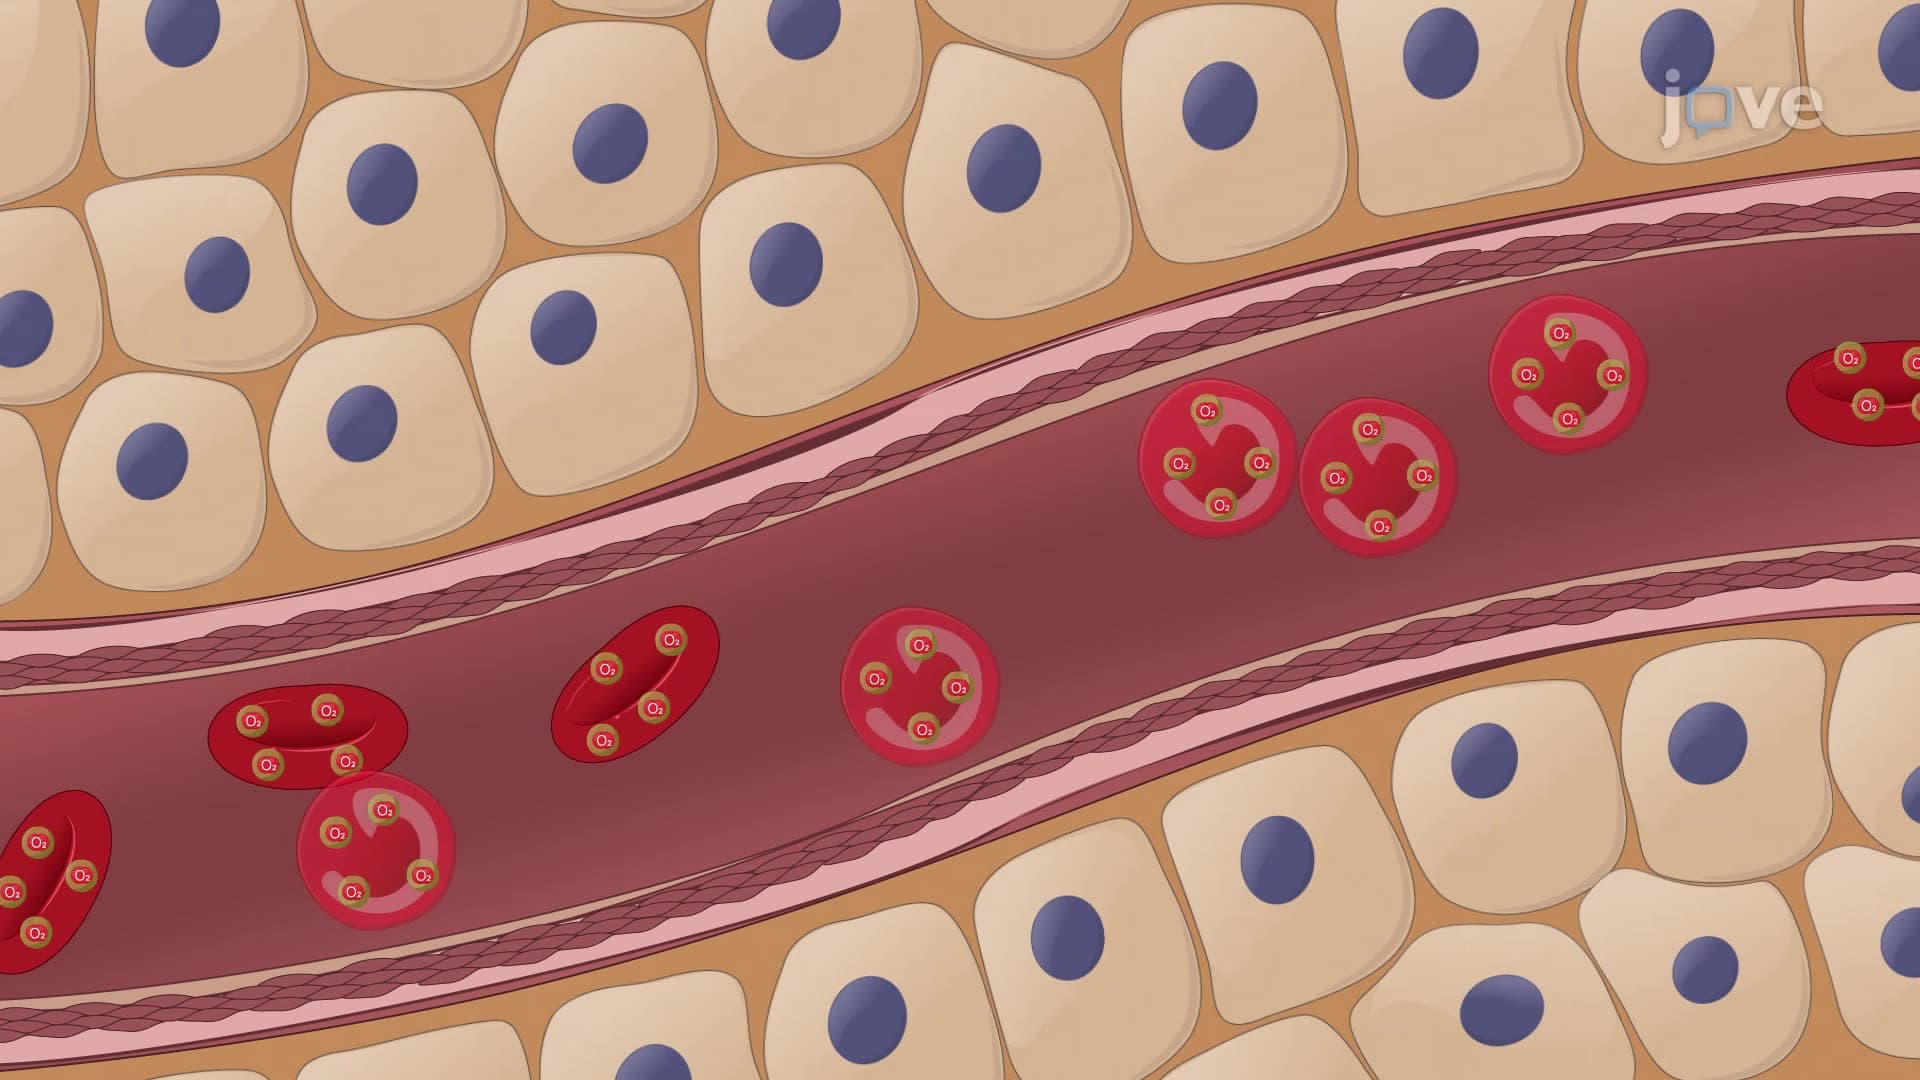 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...