Related Experiment Video
Updated: Jan 5, 2026

Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Anatomy of the Posterior Antebrachial Cutaneous Nerve, Revisited
Brian W Starr1, Dennis S Lee2, Peter J Stern2
1Department of Surgery, Division of Plastic, Reconstructive, Hand and Burn Surgery, University of Cincinnati College of Medicine, Cincinnati, OH.

Purpose:
To describe the branching pattern of the posterior antebrachial cutaneous nerve (PABCN) and to corroborate measurements and observations reported by previous authors.
Methods:
Using 28 fresh-frozen cadaver specimens, we dissected the PABCN from its origin from the radial nerve to its terminal arborization in the distal forearm. Measurements relative to the lateral humeral epicondyle were recorded. The course of the nerve over the muscles of the mobile wad and its branching pattern in the proximal forearm were noted.
Results:
The PABCN originated from the radial nerve at a mean of 14.2 cm proximal to the lateral epicondyle. The fascial hiatus through which the PABCN emerged to become superficial was a mean of 8.2 cm proximal to the lateral epicondyle. All specimens had at least 1 longitudinal branch that passed a mean of 2.8 cm anterior to the lateral epicondyle. Thirty-two percent of specimens had a lesser proximal branch in the distal third of the lateral arm; 86% had an epicondylar branch to the lateral epicondyle; and 21% had a second longitudinal branch. Ninety-three percent had a longitudinal branch coursing over the interval between the brachioradialis and the extensor carpi radialis longus in the proximal forearm.
Conclusions:
After becoming superficial in the distal brachium, the PABCN typically gives off a discrete epicondylar branch and then continues distally in the forearm as 1 or 2 longitudinal branches. In addition, in the proximal third of the forearm, a consistent longitudinal branch of the PABCN courses over the interval between the brachioradialis and the extensor carpi radialis longus. This review confirms previous observations of the PABCN.
Clinical Relevance:
Knowledge of the course of the PABCN will assist surgeons in identifying and avoiding injury in clinical situations such as plating the proximal radius or releasing the radial tunnel.
More Related Videos
 10:36
Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
 08:01
Cutaneous Surgical Denervation: A Method for Testing the Requirement for Nerves in Mouse Models of Skin Disease
Published on: June 26, 2016
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:12
Arteries of the Upper Limbs
 01:17
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...
 01:23
Spinal Nerves: Anatomy
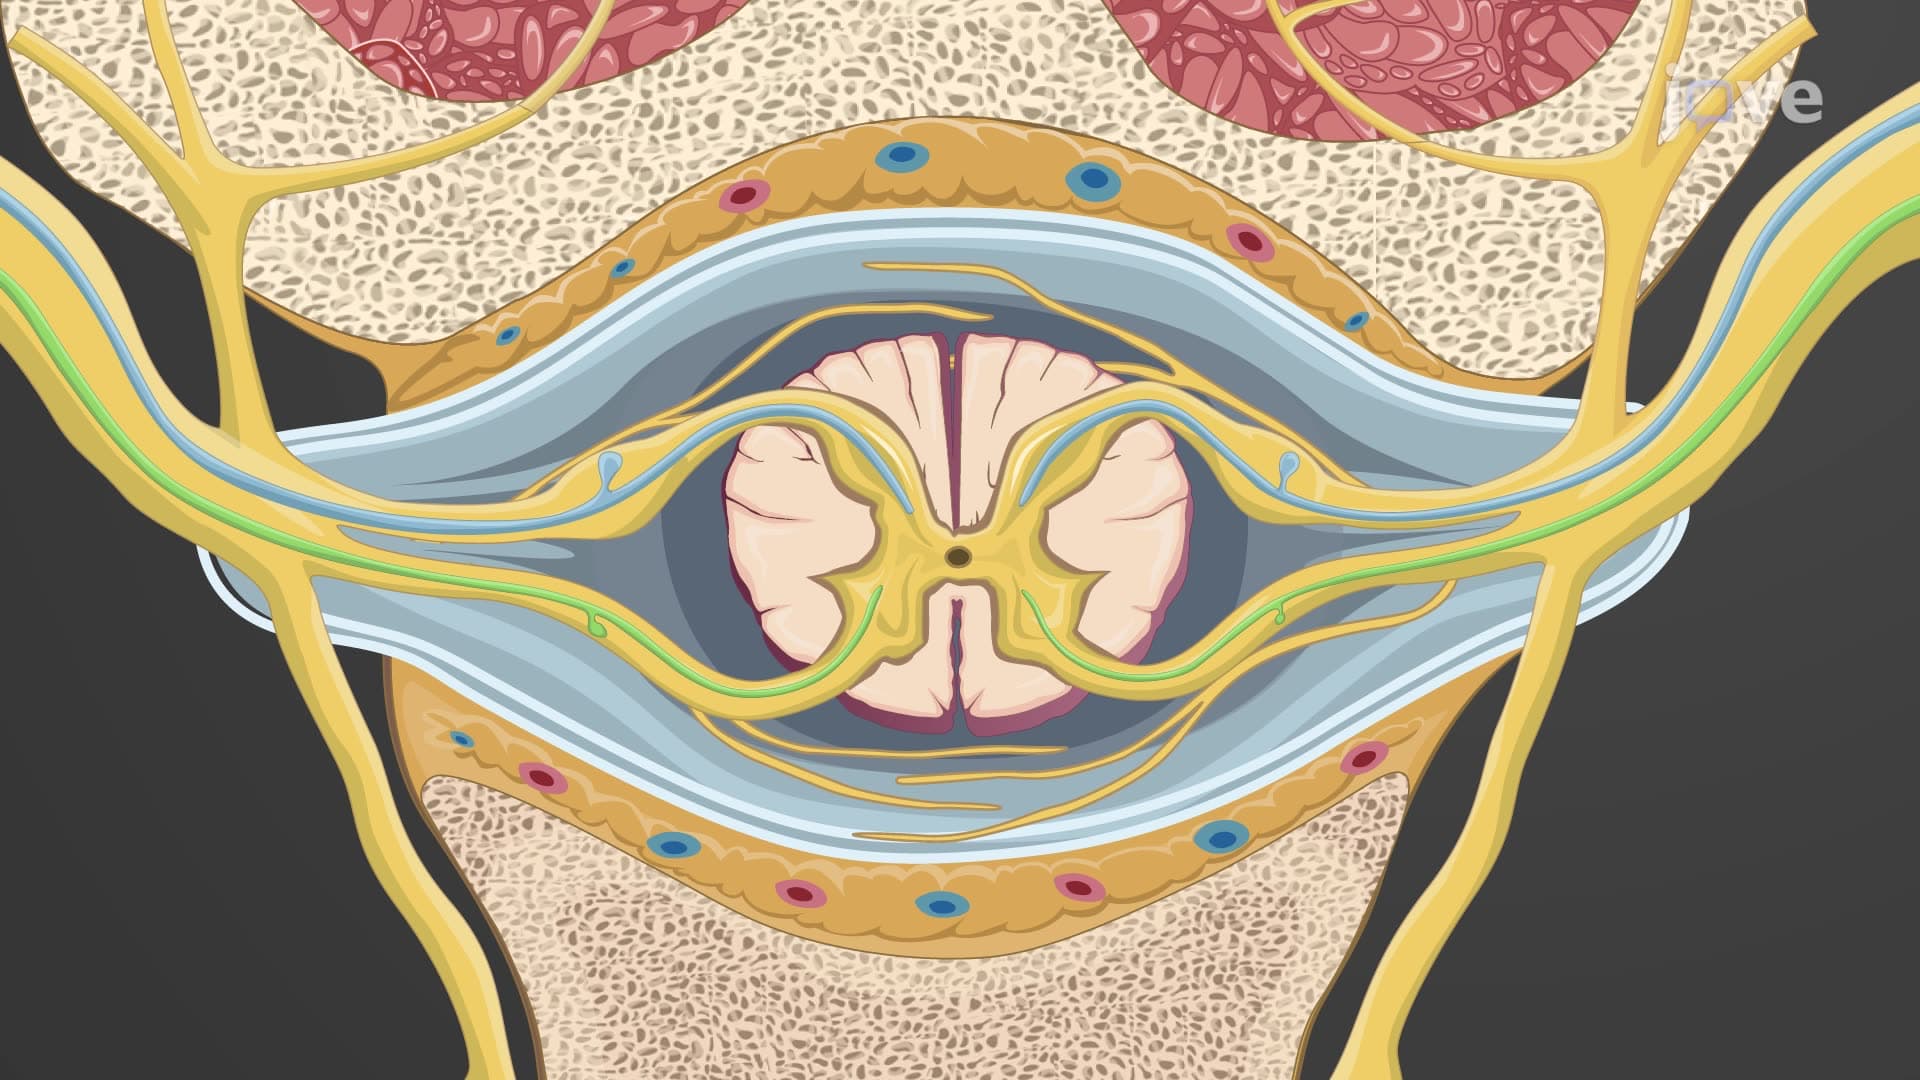
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...
 01:11
Papillary Dermis
The dermis might be considered the "core" of the integumentary system, as distinct from the epidermis and hypodermis. It contains blood and lymph vessels, nerves, and other structures, such as hair follicles and sweat glands. The dermis is made of two layers of connective tissue that comprise an interconnected mesh of elastin and collagenous fibers, produced by fibroblasts.
Papillary Layer
The papillary layer is made of loose, areolar connective tissue, which means the collagen...
 01:17
Veins of Upper Limbs
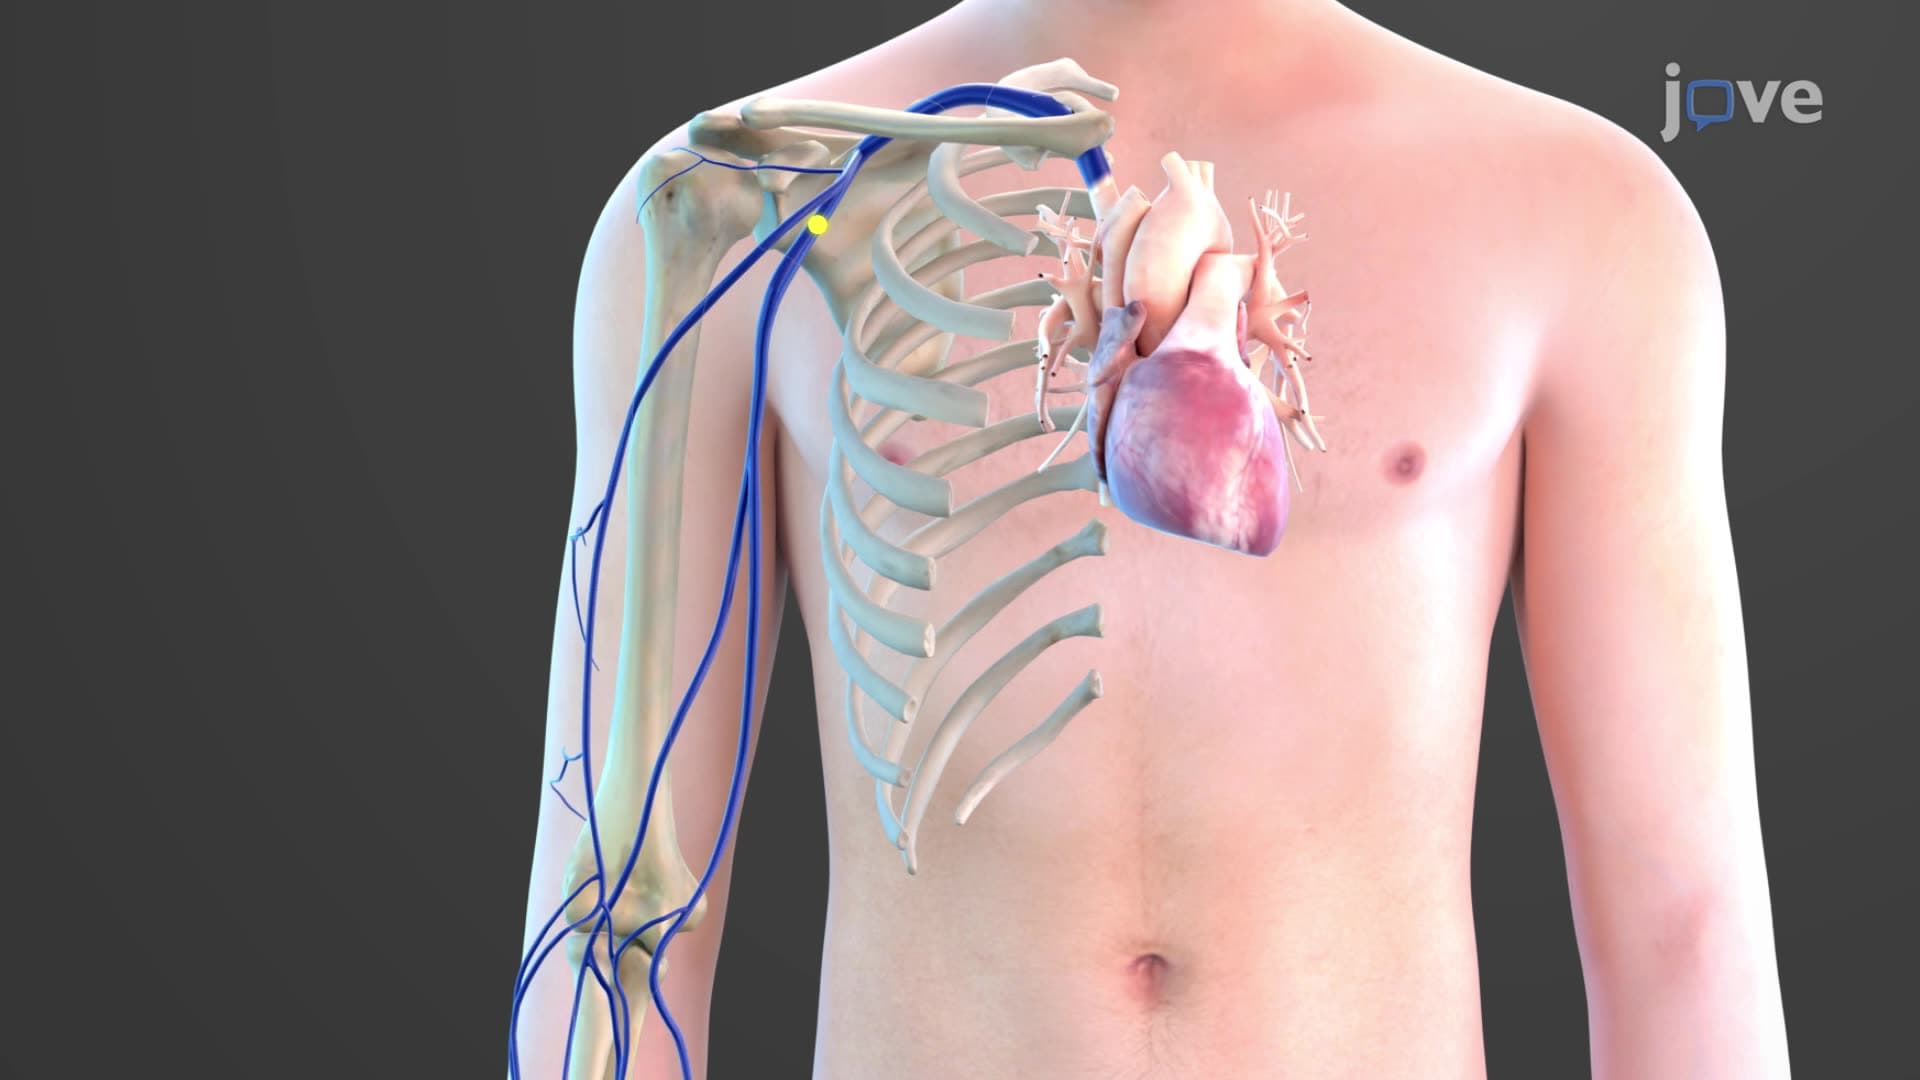
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...