Related Experiment Video
Updated: Jan 5, 2026
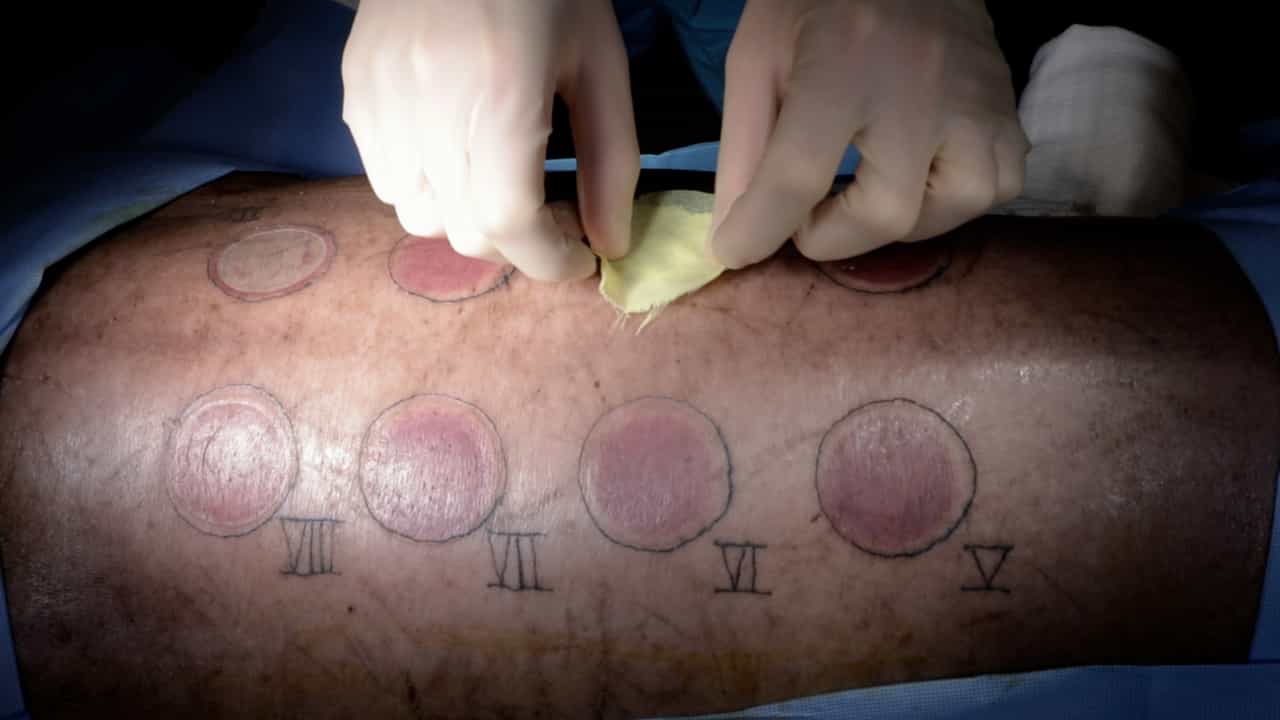
Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
[Clinical randomized controlled trial on influence of recombinant human growth hormone on the immune function of
1Ministry of Education Key Laboratory of Child Development and Disorders, National Clinical Reasearch Center for Child Health and Disorders, China International Science and Technology Cooperation Base of Child Development and Critical Disorders, Chongqing Key Laboratory of Pediatrics, Department of Burns and Plastic Surgery, Children's Hospital of Chongqing Medical University, Chongqing 400014, China.

Insights
Recombinant human growth hormone (rhGH) treatment in young children with severe burns may improve cellular immunity by increasing CD4(+) T cells and decreasing CD8(+) T cells. This study suggests rhGH could be a beneficial clinical option for pediatric burn patients.
Area of Science:
- Immunology
- Pediatric Burn Care
Background:
- Severe burn injuries in children can significantly impair immune function.
- Recombinant human growth hormone (rhGH) has potential immunomodulatory effects.
- Understanding rhGH's impact on pediatric burn patients' immunity is crucial for optimizing treatment.
Purpose of the Study:
- To investigate the preliminary influence of rhGH on the immune function of young children suffering from severe burn injuries.
- To assess changes in T lymphocyte subsets, B lymphocytes, and immunoglobulin levels following rhGH administration.
Main Methods:
- A prospective, randomized, double-blinded, controlled trial involving 30 pediatric burn patients.
- Treatment groups: standard care (control) vs. standard care plus rhGH (0.2 IU·kg(-1)·d(-1) subcutaneously for 7 days).
- Immune parameters (T lymphocyte subsets, B lymphocytes, immunoglobulins, complement C3) and blood glucose were measured via flow cytometry and ELISA.
Main Results:
- rhGH treatment significantly increased CD4(+) T lymphocyte percentages and the CD4(+)/CD8(+) ratio on day 7.
- A significant decrease in CD8(+) T lymphocyte percentage was observed on day 3 in the rhGH group.
- No significant effect of rhGH was found on CD19(+) B lymphocytes, serum IgA, IgG, or complement C3 levels.
Conclusions:
- rhGH shows limited impact on humoral immunity in pediatric burn patients.
- rhGH may enhance cellular immunity by modulating T lymphocyte subsets (increasing CD4+, decreasing CD8+).
- rhGH demonstrates potential as a therapeutic agent for younger children with severe burn injuries.
Abstract:
Objective: To preliminarily investigate the influence of recombinant human growth hormone (rhGH) on the immune function of younger children with severe burn injuries. Methods: A total of 30 younger children with severe burn injuries, conforming to the study criteria, were admitted to our hospital from July 2016 to July 2018. They were enrolled in the prospective, randomized, double-blinded, controlled trial and divided into group rhGH [n=15, 10 boys and 5 girls, aged (22±10) months] and control group [n=15, 8 boys and 7 girls, aged (21±7) months] according to the random number table. The patients in control group received anti-shock, anti-infection, and wound caring therapies, etc. On the basis of above-mentioned treatment, the patients in group rhGH were subcutaneously injected with rhGH once every night before bedding, with a dosage of 0.2 IU·kg(-1)·d(-1), from the 3rd day post injury for 7 consecutive days. Before and on the 3rd and 7th day of rhGH treatments, the fasting peripheral venous blood was collected from patients in both groups. Blood glucose level was detected by glucometer. Percentages of CD4(+) T lymphocytes, CD8(+) T lymphocytes, CD3(+) T lymphocytes, CD19(+) B lymphocytes, and ratio of CD4(+) T lymphocytes to CD8(+) T lymphocytes were determined by flow cytometer. Mass concentration of serum immune globulin (Ig) A, IgG, and complement C3 were detected by enzyme-linked immunosorbent assay. Data were processed with Fisher's exact probability test, independent sample t test, analysis of variance for repeated measurement and Bonferroni correction, and Mann-Whitney U test. Results: (1) The blood glucose levels of children in the two groups were similar before and on the 3rd and 7th day of rhGH treatment (t=0.474, 1.652, 1.997, P>0.05). The glucose levels of children in group rhGH on the 3rd and 7th day of rhGH treatment [(6.9±1.0) and (7.7±1.1) mmol/L] were significantly higher than (5.9±0.9) mmol/L before rhGH treatment (P<0.05). The glucose level of children in control group on the 7th day of rhGH treatment was significantly higher than that before rhGH treatment (P<0.05). (2) The percentages of CD4(+) T lymphocytes of children in group rhGH before rhGH treatment and on the 7th day of rhGH treatment were (35.1±2.0)% and (38.5±2.2)%, which were close to (36.2±2.0)% and (33.6±2.2)% in control group, respectively (t=0.371, 1.553, P>0.05). The percentages of CD4(+) T lymphocytes of children in group rhGH on the 7th day of rhGH treatment[(44.7±2.2)%] was significantly higher than (36.5±2.2)% in control group (t=2.624, P<0.05). The percentage of CD4(+) T lymphocytes of children in group rhGH on the 7th day of rhGH treatment was significantly higher than that before rhGH treatment (P<0.05). The percentages of CD4(+) T lymphocytes of children in control group on the 3rd and 7th day of rhGH treatment were both close to the percentage before rhGH treatment (P>0.05). (3) The percentage of CD8(+) T lymphocytes of children in group rhGH on the 3rd day of rhGH treatment was significantly lower than that in control group (t=2.107, P<0.05). (4) The ratio of CD4(+) T lymphocytes to CD8(+) T lymphocytes of children in group rhGH on the 7th day of rhGH treatment (2.36±0.20) was significantly higher than 1.72±0.20 in control group (t=2.285, P<0.05). The ratio of CD4(+) T lymphocytes to CD8(+) T lymphocytes of children in group rhGH on the 7th day of rhGH treatment was significantly higher than 2.04±0.19 before rhGH treatment (P<0.05). (5) The percentages of CD3(+) T lymphocytes and CD19(+) B lymphocytes of children in the two groups were similar before and on the 3rd and 7th day of rhGH treatment (t=1.913, 0.552, 1.327, 1.465, 1.587, 0.407, P>0.05). The percentages of CD3(+) T lymphocytes of children in group rhGH on the 3rd and 7th day of rhGH treatment were significantly higher than the percentage before rhGH treatment (P<0.05). (6) The mass concentration of serum IgA, complement C3, and IgG of children in the two groups was similar before and on the 3rd and 7th day of rhGH treatment (t=-1.596, -0.100, 1.263, -0.220, 1.378, 1.631, Z=0.228, 0.519, 1.182, P>0.05). The mass concentration of serum IgA and complement C3 of children in group rhGH on the 3rd and 7th day of rhGH treatment was significantly higher than that before rhGH treatment(P<0.05). Conclusions: rhGH has little effect on humoral immunity of younger children with severe burn injuries with limited influence on CD19(+) B lymphocyte, mass concentration of serum IgA, IgG, and complement C3. It may improve the cellular immunity function mainly through promoting the release of CD4(+) T lymphocyte, reducing the release of CD8(+) T lymphocyte. It can be used in clinical treatment of younger children with severe burn injuries.


