Related Experiment Video
Updated: Jun 10, 2026


Using Continuous Data Tracking Technology to Study Exercise Adherence in Pulmonary Rehabilitation
Published on: November 9, 2013
Female reproductive history in relation to chronic obstructive pulmonary disease and lung function in UK biobank: a
Rosalind Tang1,2, Abigail Fraser3,4, Maria Christine Magnus3,4,5
1Bristol Medical School, Faculty of Health Sciences, University of Bristol, Bristol, UK rt16358@bristol.ac.uk.

Objectives:
Sex differences in respiratory physiology and predilection for developing chronic obstructive pulmonary disease (COPD) have been documented, suggesting that female sex hormones may influence pathogenesis. We investigated whether aspects of female reproductive health might play a role in risk of COPD among women.
Design:
Population-based prospective cohort study.
Setting:
UK Biobank recruited across 22 centres in the UK between 2006 to 2010.
Primary And Secondary Outcomes Measures:
We examined a range of female reproductive health indicators in relation to risk of COPD-related hospitalisation/death (n=271 271) using Cox proportional hazards regression; and lung function (n=273 441) using linear regression.
Results:
Parity >3 was associated with greater risk of COPD-related hospitalisation/death (adjusted HR 1.45; 95% CI: 1.16 to 1.82) and lower forced expiratory volume at 1 second/forced vital capacity ratio (FEV1/FVC) (adjusted mean difference -0.06; 95% CI: -0.07 to 0.04). Any oral contraception use was associated with lower risk of COPD-related hospitalisation/death (adjusted HR 0.85; 95% CI: 0.74 to 0.97) and greater FEV1/FVC (adjusted mean difference 0.01; 95% CI: 0.003 to 0.03). Late menarche (age >15) and early menopause (age <47) were also associated with greater risk of COPD-related hospitalisation/death (but not lung function), while endometriosis was associated with greater FEV1/FVC (not COPD-related hospitalisation/death). Early menarche (age <12 years) was associated with lower FEV1/FVC (but not COPD hospitalisation/death). Associations with polycystic ovary syndrome (PCOS) or ovarian cysts, any hormone replacement therapy (HRT) use, hysterectomy-alone and both hysterectomy and bilateral oophorectomy were in opposing directions for COPD-related hospitalisation/death (greater risk) and FEV1/FVC (positive association).
Conclusions:
Multiple female reproductive health indicators across the life course are associated with COPD-related hospitalisation/death and lung function. Further studies are necessary to understand the opposing associations of PCOS/ovarian cysts, HRT and hysterectomy with COPD and objective measures of airway obstruction.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:23
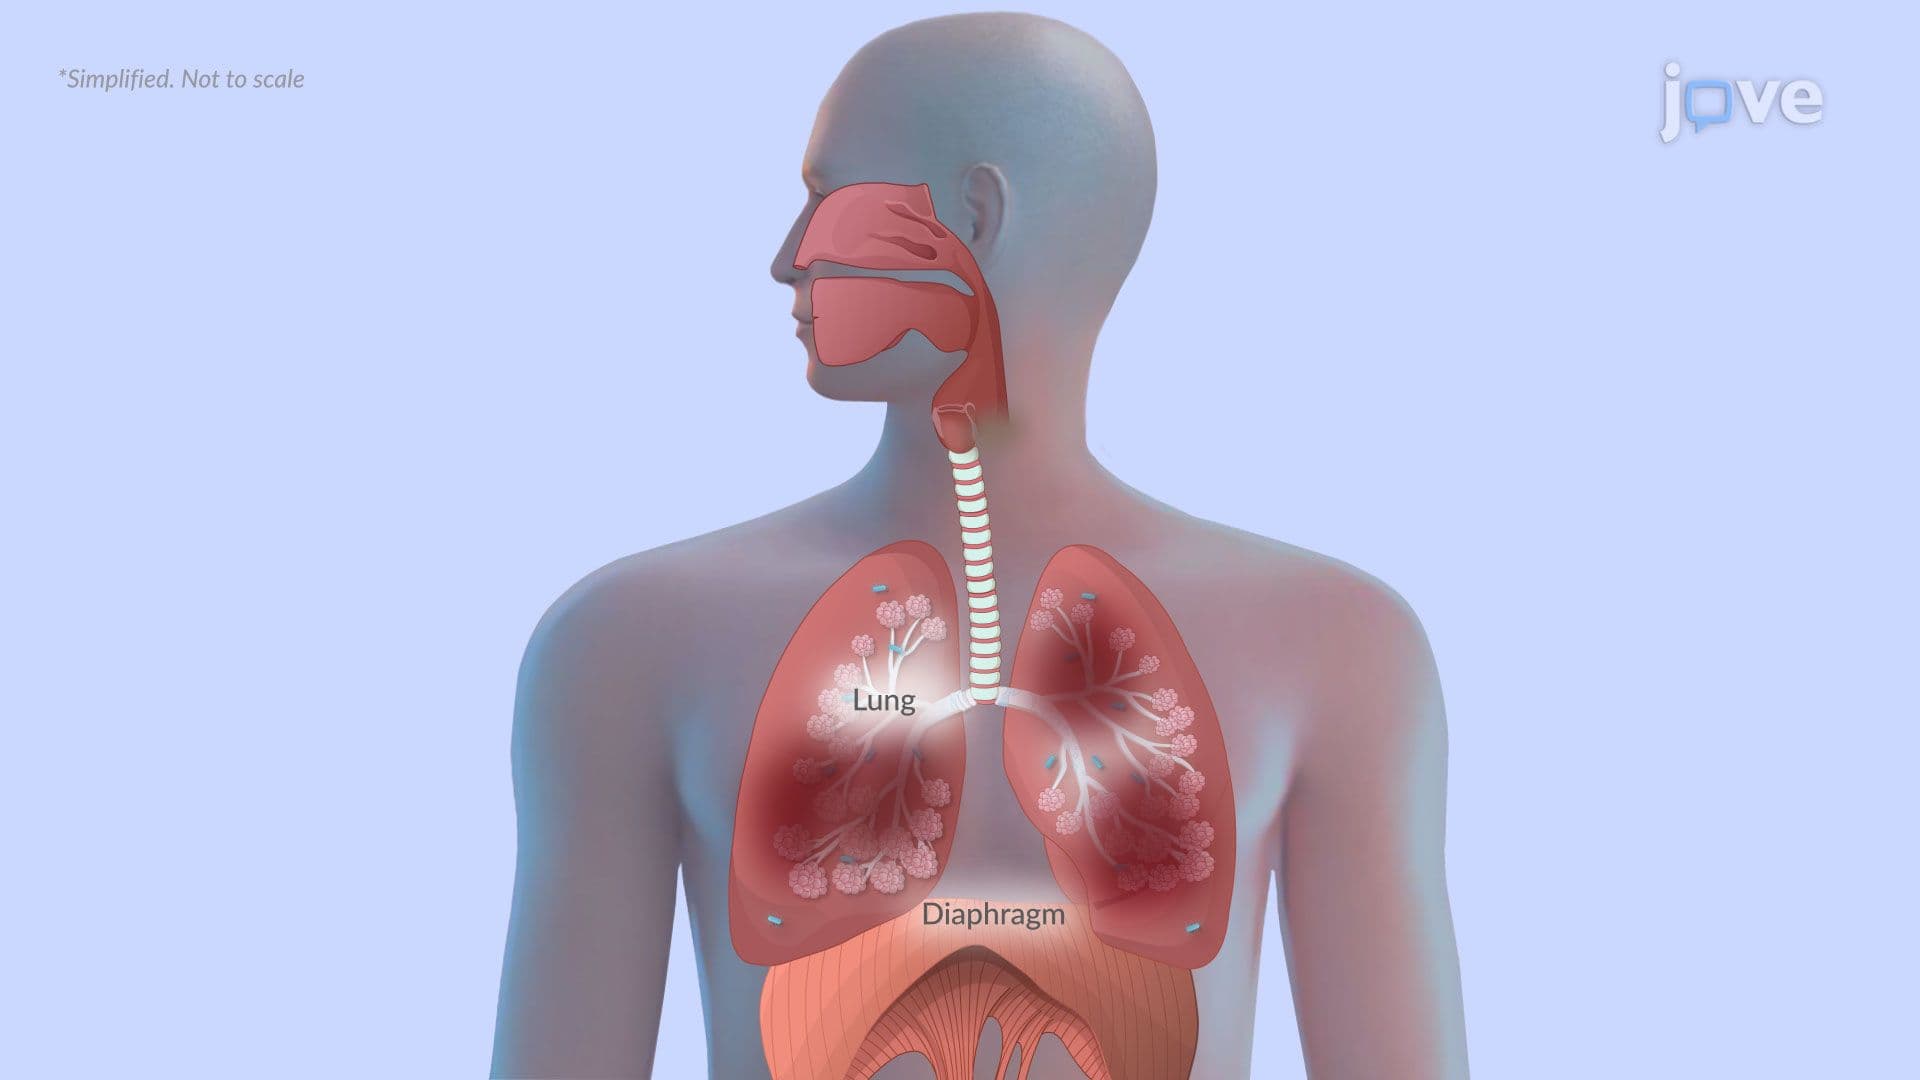
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features