Related Experiment Video
Updated: Jan 4, 2026


Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Prevalence and Impact of Treatment Crossover in Cardiac Surgery Randomized Trials: A Meta-Epidemiologic Study
Mario Gaudino1, Stephen E Fremes2, Marc Ruel3
1Department of Cardiothoracic Surgery Weill Cornell Medicine New York NY.

Abstract:
Background Crossover dilutes treatment effect and reduces statistical power of intention-to-treat analysis. We examined incidence and impact on cardiac surgery randomized controlled trial (RCT) outcomes of crossover from experimental to control interventions, or vice versa. Methods and Results MEDLINE, EMBASE, and Cochrane Library were searched, and RCTs (≥100 patients) comparing ≥2 adult cardiac surgical interventions were included. Crossover from the initial treatment assignment and relative risks (RRs) for each trial's primary end point and mortality at longest available follow-up were extracted. All RRs were calculated as >1 favored control group and <1 favored experimental arm. Primary outcome was the effect estimate for primary end point of each RCT, and secondary outcome was all-cause mortality; both were appraised as RR at the longest follow-up available. Sixty articles reporting on 47 RCTs (25 440 patients) were identified. Median crossover rate from experimental to control group was 7.0% (first quartile, 2.0%; third quartile, 9.7%), whereas from control to experimental group, the rate was 1.3% (first quartile, 0%; third quartile, 3.6%). RRs for primary end point and mortality were higher in RCTs with higher crossover rate from experimental to control group (RR, 1.01 [95% CI, 0.94-1.07] versus RR, 0.80 [95% CI, 0.66-0.97] and RR, 1.02 [95% CI, 0.95-1.11] versus RR, 0.94 [95% CI, 0.82-1.07], respectively). Crossover from control to experimental group did not alter effect estimates for primary end point or mortality (RR, 0.82 [95% CI, 0.63-1.05] versus RR, 0.95 [95% CI, 0.86-1.04] and RR, 0.88 [95% CI, 0.73-1.07] versus RR, 1.02 [95% CI, 0.95-1.09], respectively). Conclusions Crossover from experimental to control group is associated with outcomes of cardiac surgery RCTs. Crossover should be minimized at designing stage and carefully appraised after study completion.
More Related Videos
 05:16
Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
 09:12
Surgical Swine Model of Chronic Cardiac Ischemia Treated by Off-Pump Coronary Artery Bypass Graft Surgery
Published on: March 27, 2018
Related Concept Videos
 01:16
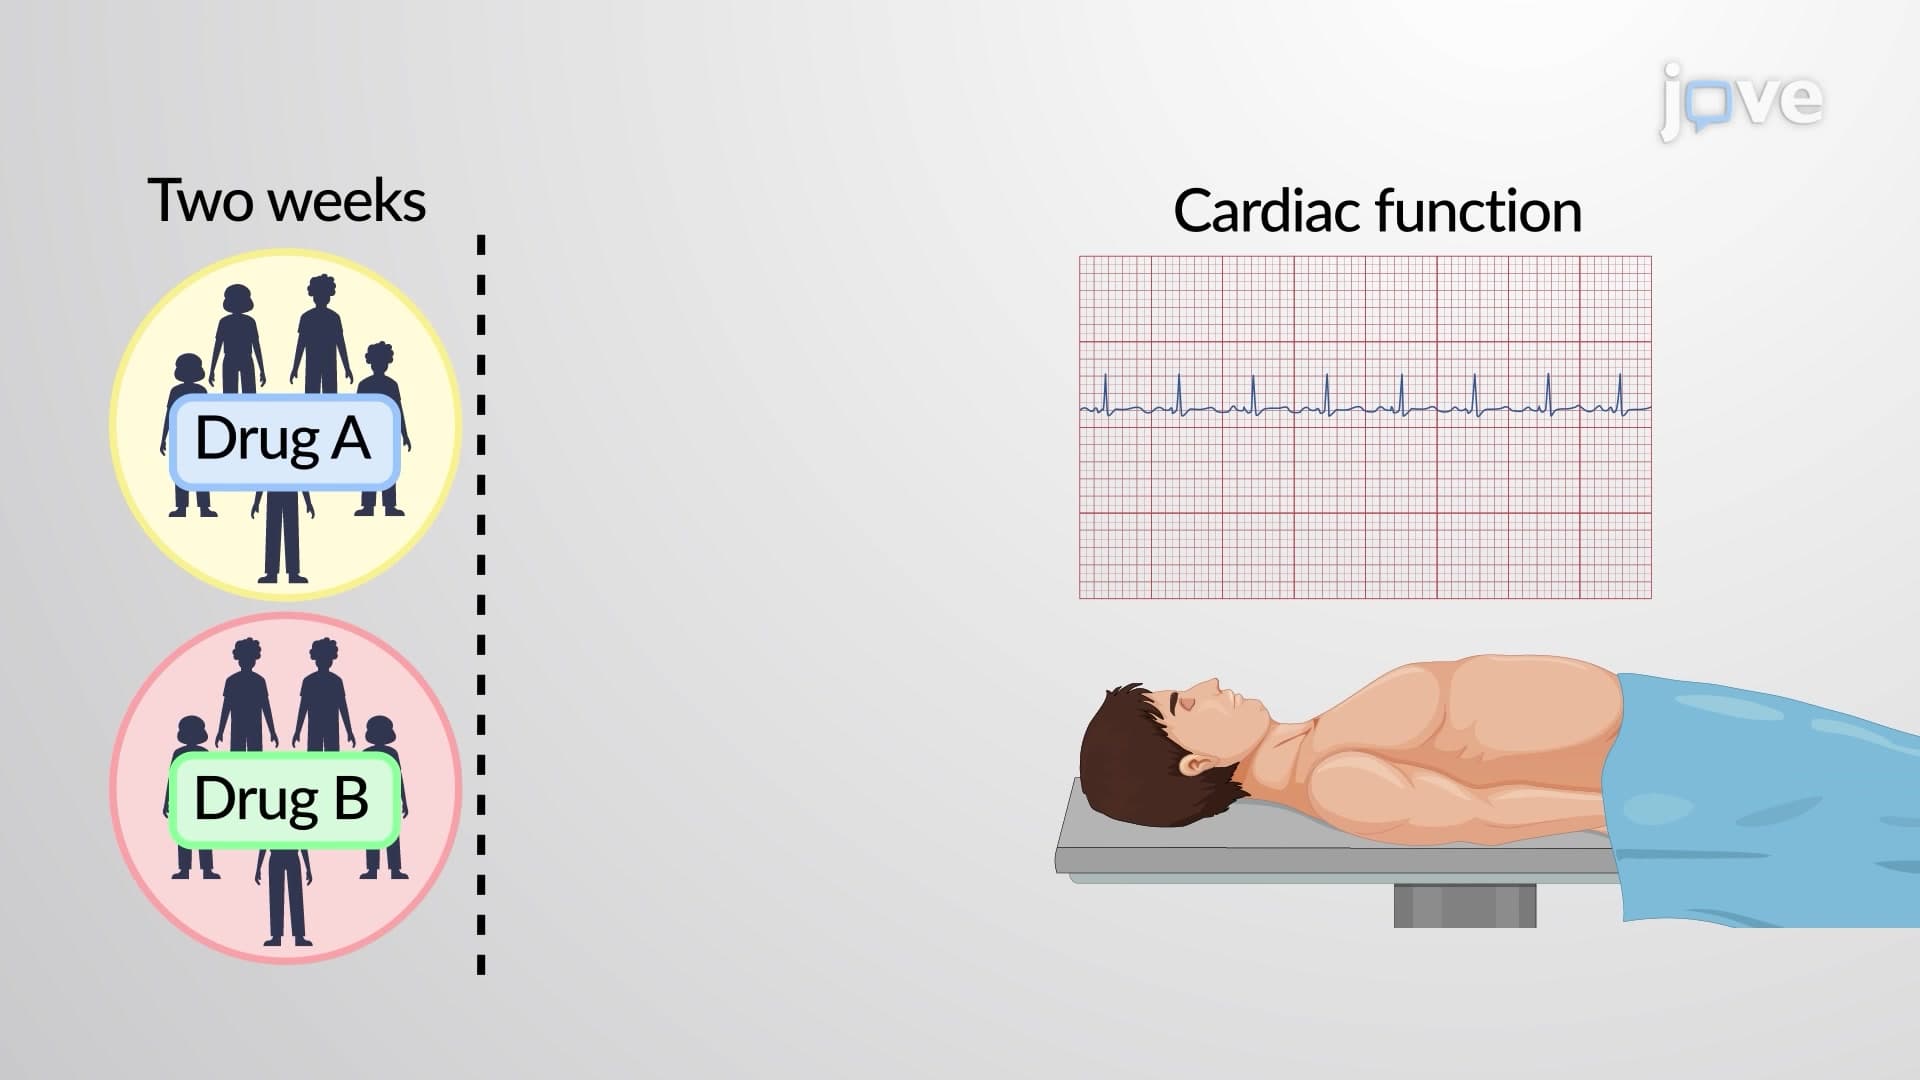
Crossover Experiments
Crossover designs are performed even with smaller sample sizes since the samples can act as their controls. These are better than simple randomized trials since patients are exposed to all the treatments.
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:15
Bioequivalence Experimental Study Designs: Repeated Measures, Cross-Over, Carry-Over, and Latin Square Designs
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:12
Hazard Ratio
For example, in a clinical trial...
 01:11
Clinical Trials: Overview