Related Experiment Video
Updated: Jan 4, 2026
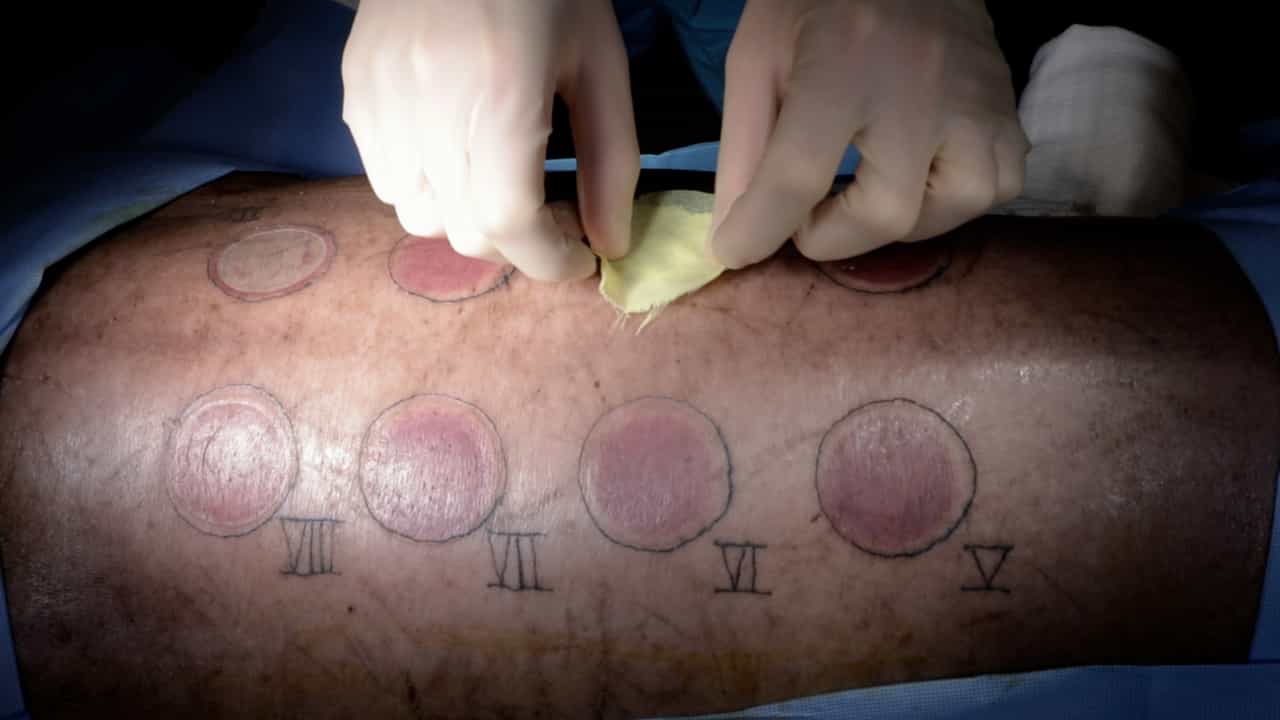

Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
Children Younger Than 18 Years Treated for Nonfatal Burns in US Emergency Departments
Meghan Mitchell1,2, Sandhya Kistamgari1, Thitphalak Chounthirath1
1The Research Institute at Nationwide Children's Hospital, Columbus, OH, USA.

Insights
Pediatric burn treatments in US emergency departments declined significantly from 1990-2014. Despite this decrease, burns remain a major injury source, highlighting the need for enhanced prevention strategies, particularly for young children.
Area of Science:
- Pediatric Emergency Medicine
- Public Health Surveillance
- Injury Prevention
Background:
- Burns are a significant cause of pediatric injury requiring emergency department (ED) treatment.
- Understanding burn mechanisms and demographics is crucial for effective prevention strategies.
Purpose of the Study:
- To analyze trends in pediatric burn injuries treated in US EDs from 1990 to 2014.
- To identify common burn mechanisms and injury locations in children.
- To provide data for enhancing pediatric burn prevention efforts.
Main Methods:
- Utilized data from the National Electronic Injury Surveillance System (NEISS) for children (<18 years) treated for burns in US EDs.
- Analyzed a 25-year period (1990-2014) to identify trends in incidence, demographics, injury types, and mechanisms.
- This is the first study to use a nationally representative sample to investigate burn mechanisms.
Main Results:
- Over 2.5 million pediatric burn cases were treated, with an average of 101,959 annually.
- A significant decrease in burn incidence (30.0%) and rate (38.9%) was observed during the study period (P < .001).
- Young children (<6 years, 64.0%) and boys (58.4%) were most affected; thermal burns (60.2%) were most common, with hands/fingers (37.1%) and head/neck (19.6%) being primary injury sites. Grabbing/touching (18.4%) and spilling/splashing (16.4%) were leading causes.
Conclusions:
- Despite a downward trend, pediatric burns treated in EDs remain a substantial public health concern.
- The findings underscore the critical need for targeted prevention strategies, especially for children under 6.
- This research provides valuable insights into burn mechanisms, informing future injury prevention initiatives.
Abstract:
This study investigated children <18 years old treated for burns in United States (US) emergency departments from 1990 to 2014 using data from the National Electronic Injury Surveillance System. There were 2 548 971 children treated for burns during the study period, averaging 101 959 annually. The number and rate of burns decreased by 30.0% and 38.9%, respectively, (both P < .001) during the study. Most patients (58.4%) were boys, 64.0% were <6 years old, and 7.4% were admitted to the hospital. Thermal burns accounted for 60.2% of injuries. The hand/fingers were most commonly injured (37.1%), followed by head/neck (19.6%). The most common specified mechanism of injury was grabbing/touching (18.4%), followed by spilling/splashing (16.4%). Although the number of children treated for burns has decreased, it remains an important source of pediatric injury, demonstrating the need to increase prevention efforts, especially among young children. This is the first study to use a nationally representative sample to investigate burn mechanisms.
Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:29
Decreased Body Temperature
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:29
Drug Dosing: Infants and Children
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: