Related Experiment Video
Updated: Jan 4, 2026
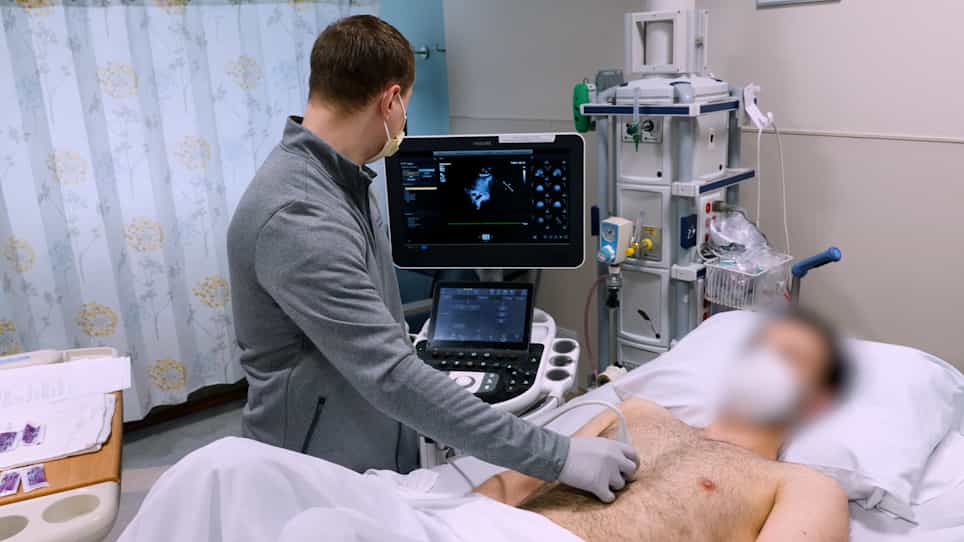
Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Ultrasonographic inferior vena cava diameter response to trauma resuscitation after 1 hour predicts 24-hour fluid
Jay Joseph Doucet1, Paula Ferrada, Sarah Murthi
1From the Division of Trauma, Surgical Critical Care, Burns, and Acute Care Surgery, Department of Surgery (J.D., S.E., E.C.), University of California San Diego, San Diego, California; Trauma, Critical Care and Emergency Surgery (P.F., J.H.), Virginia Commonwealth University, Richmond, Virginia; Department of Surgery, Division of Trauma and Surgical Critical Care (S.M., D.H.), University of Maryland School of Medicine, R Adams Cowley Shock Trauma Center, Baltimore, Maryland; Department of Surgery (R.N., A.S., Y.B.), University of Utah, Salt Lake City, Utah; Department of Radiology (G.C.), University of California San Diego, San Diego; and Riverside University Health System Medical Center (R.C.), Moreno Valley; and Department of Surgery, Loma Linda University School of Medicine, Loma Linda, California.

Background:
Identification of occult hypovolemia in trauma patients is difficult. We hypothesized that in acute trauma patients, the response of ultrasound-measured minimum inferior vena cava diameter (IVCDMIN), IVC Collapsibility Index (IVCCI), minimum internal jugular diameter (IJVDMIN) or IJV Collapsibility Index (IJVCI) after up to 1 hour of fluid resuscitation would predict 24-hour resuscitation intravenous fluid requirements (24FR).
Methods:
An NTI-funded, American Association for the Surgery of Trauma Multi-Institutional Trials Committee prospective, cohort trial was conducted at four Level I Trauma Centers. Major trauma patients were screened for an IVCD of 12 mm or less or IVCCI of 50% or less on initial focused assessment sonographic evaluations for trauma. A second IVCD was obtained 40 minutes to 60 minutes later, after standard-of-care fluid resuscitation. Patients whose second measured IVCD was less than 10 mm were deemed nonrepleted (NONREPLETED), those 10 mm or greater were repleted (REPLETED). Prehospital and initial resuscitation fluids and 24FR were recorded. Demographics, Injury Severity Score, arterial blood gasses, length of stay, interventions, and complications were recorded. Means were compared by ANOVA and categorical variables were compared via χ. Receiver operating characteristic curves analysis was used to compare the measures as 24FR predictors.
Results:
There were 4,798 patients screened, 196 were identified with admission IVCD of 12 mm or IVCCI of 50% or less, 144 were enrolled. There were 86 REPLETED and 58 NONREPLETED. Demographics, initial hemodynamics, or laboratory measures were not significantly different. NONREPLETED had smaller IVCD (6.0 ± 3.7 mm vs. 14.2 ± 4.3 mm, p < 0.001) and higher IVCCI (41.7% ± 30.0% vs. 13.2% ± 12.7%, p < 0.001) but no significant difference in IJVD or IJVCCI. REPLETED had greater 24FR than NONREPLETED (2503 ± 1751 mL vs. 1,243 ± 1,130 mL, p = 0.003). Receiver operating characteristic analysis indicates IVCDMIN predicted 24FR (area under the curve [AUC], 0.74; 95% confidence interval [CI], 0.64-0.84; p < 0.001) as did IVCCI (AUC, 0.75; 95% CI, 0.65-0.85; p < 0.001) but not IJVDMIN (AUC, 0.48; 95% CI, 0.24-0.60; p = 0.747) or IJVCI (AUC, 0.54; 95% CI, 0.42-0.67; p = 0.591).
Conclusion:
Ultrasound assessed IVCDMIN and IVCCI response initial resuscitation predicts 24-hour fluid resuscitation requirements.
Level Of Evidence:
Diagnostic tests or criteria, level II.
More Related Videos
 07:59
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019