Related Experiment Video
Updated: Jan 4, 2026
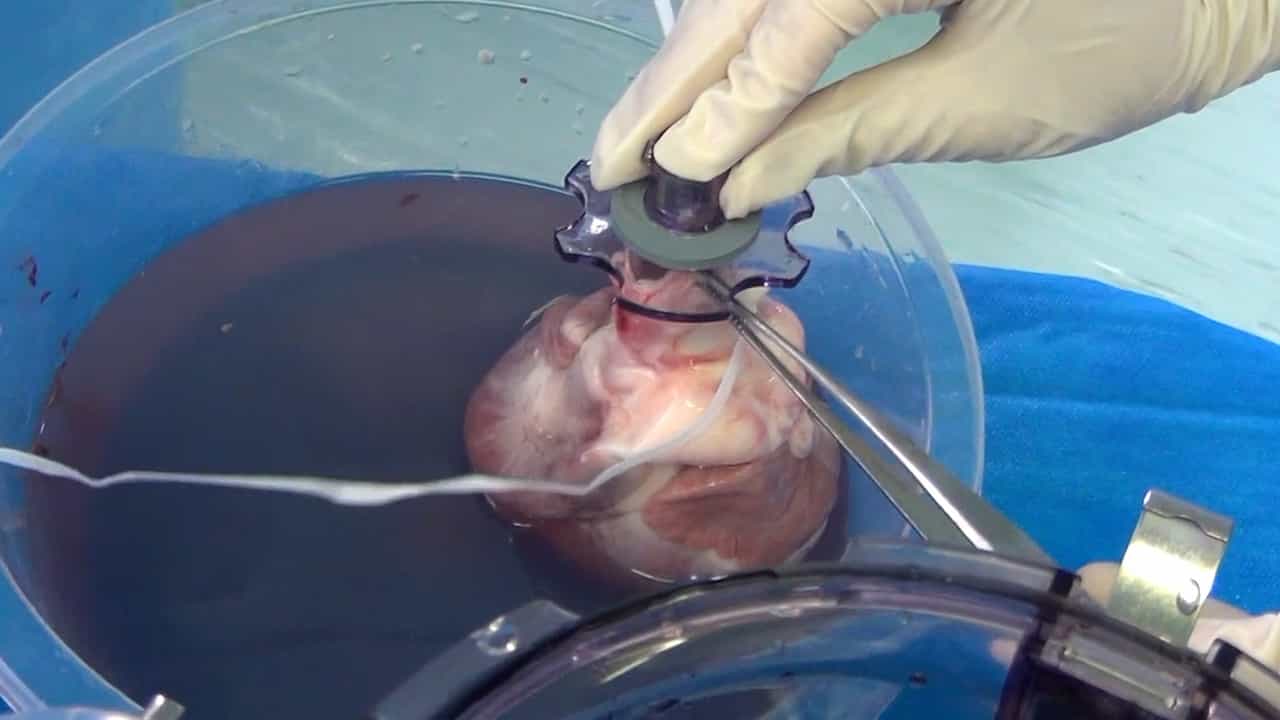
Innovative Strategies for Organ Preservation in Heart Transplantation: Uniform Cooling Preservation and Ex-situ Normothermic Perfusion
Published on: November 28, 2025
Association of Transplant Center With Survival Benefit Among Adults Undergoing Heart Transplant in the United States
William F Parker1,2,3, Allen S Anderson4, Robert D Gibbons1,3
1Department of Medicine, University of Chicago, Chicago, Illinois.

Insights
Transplant centers significantly impact heart transplant survival benefits. Centers with higher survival benefits performed transplants on sicker patients, yet post-transplant survival remained similar across centers.
Area of Science:
- Cardiology
- Transplant Surgery
- Public Health
Background:
- The availability of deceased donor hearts for transplantation in the US is limited.
- The current US heart allocation system prioritizes candidates based on supportive therapies, using transplant centers' assessments as a proxy for medical urgency.
Purpose of the Study:
- To investigate the association between transplant centers and the survival benefit of heart transplantation within the US allocation system.
Main Methods:
- An observational study analyzed data from 29,199 adult heart transplant candidates listed between January 2006 and December 2015.
- Survival benefit was calculated as the difference in 5-year survival between heart transplant recipients and candidates not receiving a transplant.
- Mixed-effects proportional hazards models, adjusted for relevant covariates, were used to estimate each center's mean survival benefit.
Main Results:
- A 5-year survival benefit of 44% was observed for heart transplant recipients compared to non-recipients.
- Significant variation in survival benefit existed across 113 transplant centers, with 27% showing significantly higher and 27% showing significantly lower benefits than the mean.
- Centers with higher survival benefits transplanted patients with lower estimated waiting list survival (29%) compared to lower benefit centers (39%).
Conclusions:
- Transplant center significantly influences the survival benefit associated with heart transplantation.
- Centers with higher survival benefits tend to perform transplants on candidates with greater medical need (lower waiting list survival).
- Despite differences in patient selection, the adjusted 5-year survival post-transplant did not significantly differ between high and low survival benefit centers.
Importance:
In the United States, the number of deceased donor hearts available for transplant is limited. As a proxy for medical urgency, the US heart allocation system ranks heart transplant candidates largely according to the supportive therapy prescribed by transplant centers.
Objective:
To determine if there is a significant association between transplant center and survival benefit in the US heart allocation system.
Design, Setting, And Participants:
Observational study of 29 199 adult candidates for heart transplant listed on the national transplant registry from January 2006 through December 2015 with follow-up complete through August 2018.
Exposures:
Transplant center.
Main Outcomes And Measures:
The survival benefit associated with heart transplant as defined by the difference between survival after heart transplant and waiting list survival without transplant at 5 years. Each transplant center's mean survival benefit was estimated using a mixed-effects proportional hazards model with transplant as a time-dependent covariate, adjusted for year of transplant, donor quality, ischemic time, and candidate status.
Results:
Of 29 199 candidates (mean age, 52 years; 26% women) on the transplant waiting list at 113 centers, 19 815 (68%) underwent heart transplant. Among heart transplant recipients, 5389 (27%) died or underwent another transplant operation during the study period. Of the 9384 candidates who did not undergo heart transplant, 5669 (60%) died (2644 while on the waiting list and 3025 after being delisted). Estimated 5-year survival was 77% (interquartile range [IQR], 74% to 80%) among transplant recipients and 33% (IQR, 17% to 51%) among those who did not undergo heart transplant, which is a survival benefit of 44% (IQR, 27% to 59%). Survival benefit ranged from 30% to 55% across centers and 31 centers (27%) had significantly higher survival benefit than the mean and 30 centers (27%) had significantly lower survival benefit than the mean. Compared with low survival benefit centers, high survival benefit centers performed heart transplant for patients with lower estimated expected waiting list survival without transplant (29% at high survival benefit centers vs 39% at low survival benefit centers; survival difference, -10% [95% CI, -12% to -8.1%]), although the adjusted 5-year survival after transplant was not significantly different between high and low survival benefit centers (77.6% vs 77.1%, respectively; survival difference, 0.5% [95% CI, -1.3% to 2.3%]). Overall, for every 10% decrease in estimated transplant candidate waiting list survival at a given center, there was an increase of 6.2% (95% CI, 5.2% to 7.3%) in the 5-year survival benefit associated with heart transplant.
Conclusions And Relevance:
In this registry-based study of US heart transplant candidates, transplant center was associated with the survival benefit of transplant. Although the adjusted 5-year survival after transplant was not significantly different between high and low survival benefit centers, compared with centers with survival benefit significantly below the mean, centers with survival benefit significantly above the mean performed heart transplant for recipients who had significantly lower estimated expected 5-year waiting list survival without transplant.
More Related Videos

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...