Related Experiment Video
Updated: Jan 4, 2026

Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
Hemoptysis and a cardiac murmur: is it primary or secondary antiphospholipid syndrome?
T Kolitz1, O Fruchter2,3, L Sasson4,3
1Department of Medicine C, Wolfson Medical Center, Holon, Israel.

Insights
Systemic lupus erythematosus (SLE) can cause non-infective endocarditis and diffuse alveolar hemorrhage. Early diagnosis and treatment with corticosteroids and immunoglobulins led to remission in a patient with primary antiphospholipid syndrome.
Area of Science:
- Cardiology
- Rheumatology
- Pathology
Background:
- Systemic lupus erythematosus (SLE) is associated with significant cardiovascular morbidity, including valvular disease and non-infective endocarditis (Libman-Sacks endocarditis).
- Antiphospholipid syndrome (APS) increases the prevalence of Libman-Sacks syndrome in SLE patients.
- Non-infective endocarditis and diffuse alveolar hemorrhage are rare but serious manifestations.
Observation:
- A patient with primary antiphospholipid syndrome presented with hemoptysis and a cardiac murmur.
- Clinical findings included non-infective verrucous vegetations and diffuse alveolar hemorrhage.
- These findings led to the diagnosis of SLE with secondary APS.
Findings:
- Treatment with high-dose corticosteroids and intravenous immunoglobulins resulted in resolution of cardiac vegetations and regression of diffuse alveolar hemorrhage.
- Aortic valve replacement was successfully performed electively with no postoperative complications.
- The patient achieved remission after a 6-month follow-up.
Implications:
- This case highlights the importance of considering SLE in patients with primary APS presenting with cardiac and pulmonary manifestations.
- Prompt diagnosis and multidisciplinary management are crucial for favorable outcomes.
- Understanding the link between SLE, APS, and non-infective endocarditis can improve patient care and treatment strategies.
Abstract:
Endocarditis is most frequently infective in origin, and thus, when a patient presents with a clinical picture suggestive of endocarditis, an extensive work up aimed at finding the infectious agent is warranted. Among systemic lupus erythematosus (SLE) patients, cardiovascular disease is prevalent in more than 50% of patients including valvular disease and non-infective endocarditis, known as Libman-Sacks (LS) endocarditis. The prevalence of LS syndrome among SLE patients with secondary antiphospholipid syndrome (APS) is higher than in SLE without APS. Here, we present a case of a patient diagnosed with primary APS who presented with hemoptysis and a cardiac murmur. The diagnosis of SLE was established following the findings of non-infective verrucous vegetations together with diffuse alveolar hemorrhage (DAH). Treatment with high-dose corticosteroids and intravenous immunoglobulins yielded substantial resolution of the vegetations and regression of the DAH. Hence, aortic valve replacement was successfully performed as an elective procedure and without any postoperative complications. The patient is in remission after a 6-month follow-up. The clinical findings of DAH and double valve non-infectious endocarditis prompted the diagnosis of SLE with secondary APS.
More Related Videos
Related Concept Videos
 01:25
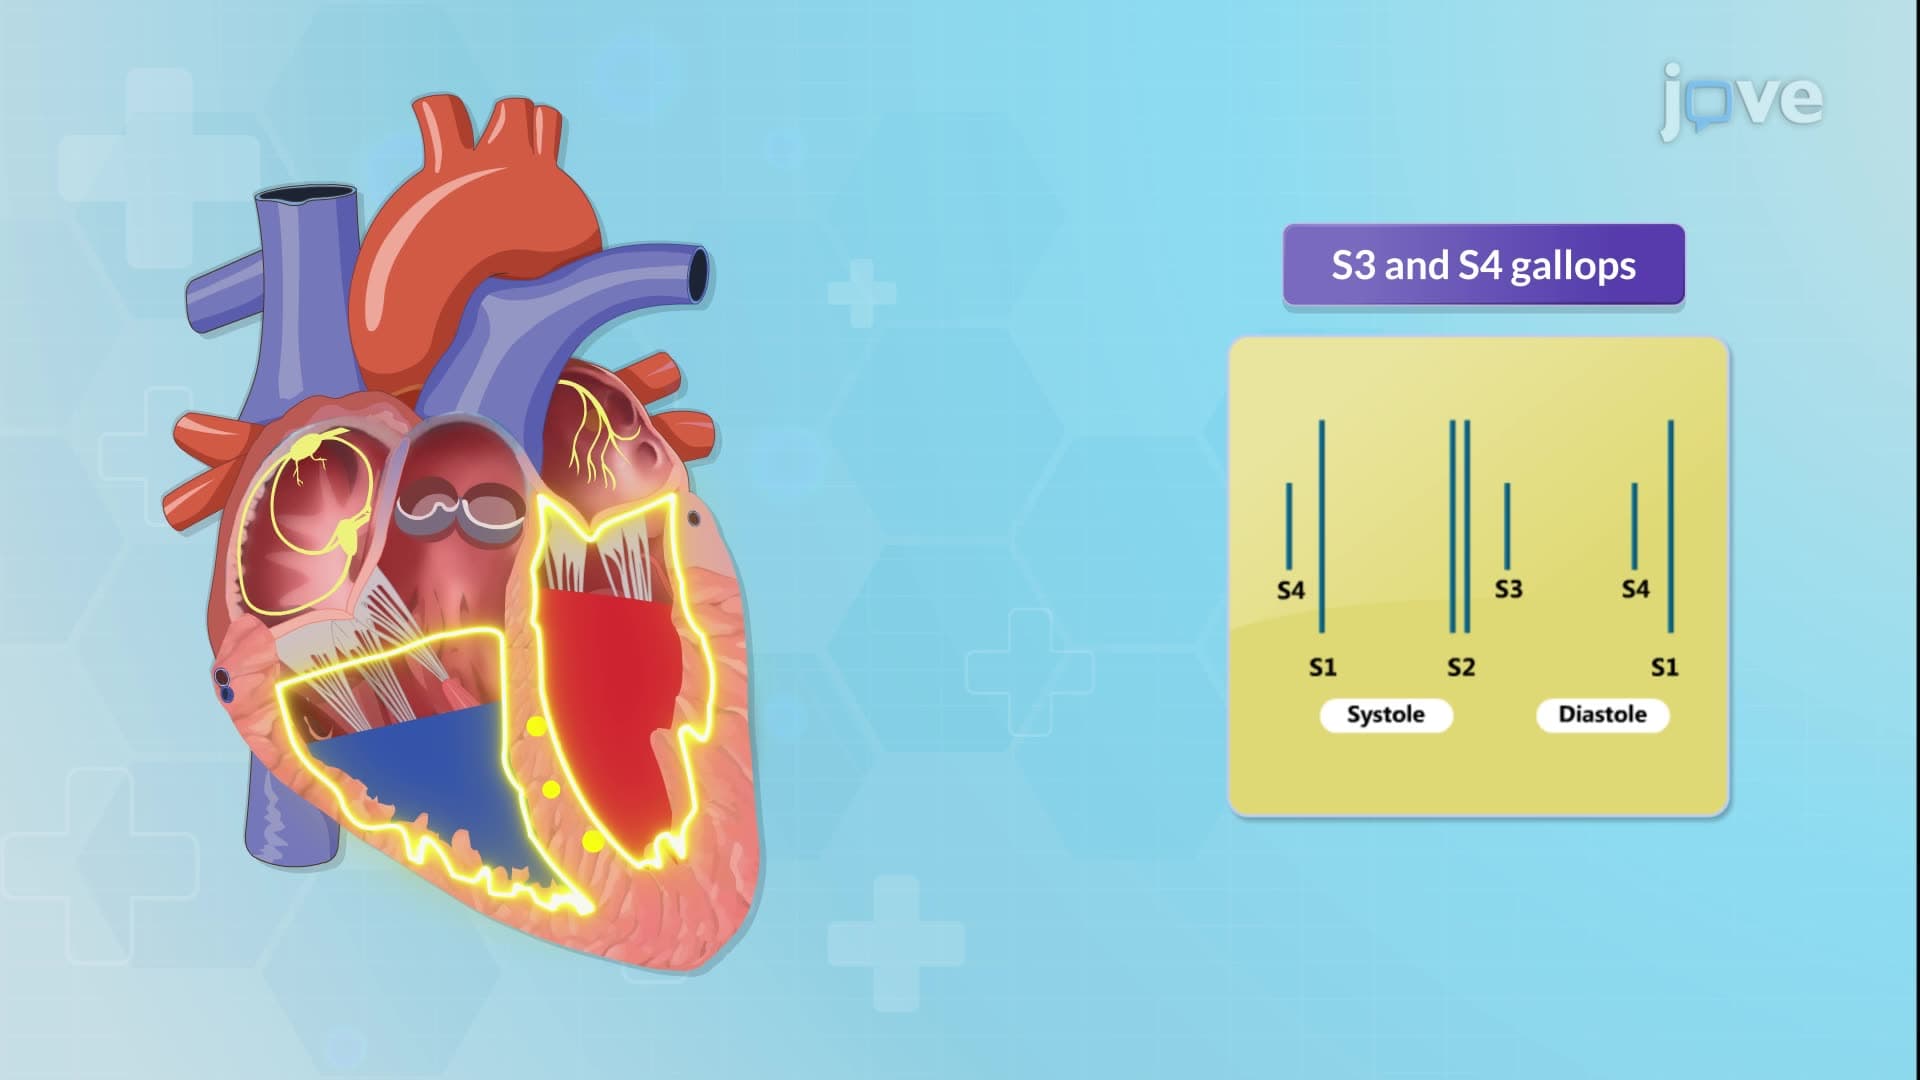
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests