Related Experiment Video
Updated: Jan 3, 2026
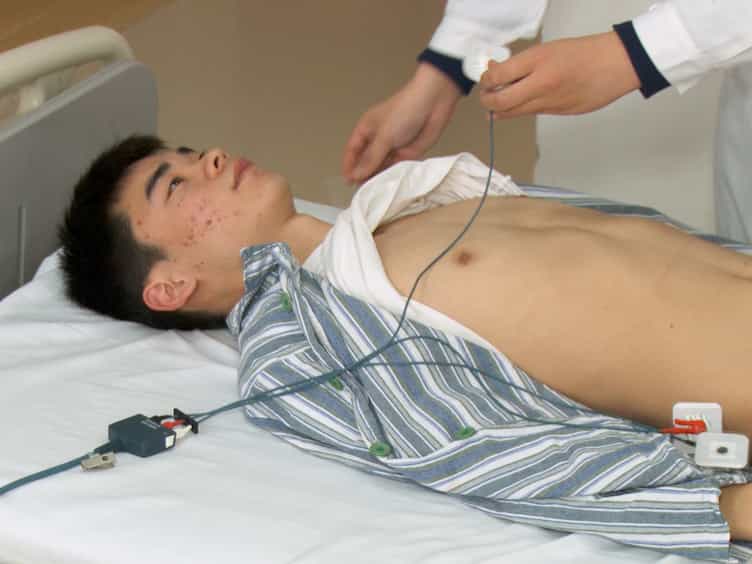
Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Association of increased arterial stiffness with diastolic dysfunction in ischemic stroke patients: the Norwegian
Eigir Einarsen1, Eva Gerdts1, Ulrike Waje-Andreassen2
1Department of Clinical Science, University of Bergen.

Insights
Diastolic dysfunction affects 20% of young and middle-aged ischemic stroke survivors. Increased arterial stiffness is a key independent predictor of this condition, even after accounting for other risk factors.
Area of Science:
- Cardiology
- Neurology
- Vascular Medicine
Background:
- Young and middle-aged ischemic stroke survivors often have hypertension, arterial stiffness, and abnormal left ventricular (LV) geometry.
- These factors are linked to LV diastolic dysfunction, but its prevalence and predictors in this population are not well-established.
Purpose of the Study:
- To investigate the prevalence and associated factors of diastolic dysfunction in ischemic stroke patients aged 15-60 years.
Main Methods:
- Analyzed data from 260 acute ischemic stroke patients.
- Assessed diastolic dysfunction using European guidelines criteria (E, e', E/e' ratio, left atrial volume index, tricuspid regurgitant jet velocity).
- Defined increased arterial stiffness as carotid-femoral pulse wave velocity ≥10 m/s.
Main Results:
- Diastolic dysfunction was present in 20% of patients (13% grade 1, 7% grades 2-3).
- Patients with diastolic dysfunction were older, more likely to have hypertension, overweight, increased arterial stiffness, and higher LV mass.
- Multivariable analysis showed diastolic dysfunction associated with increased arterial stiffness (OR 2.86, P<0.05) independent of other factors.
Conclusions:
- Diastolic dysfunction is prevalent in 20% of young and middle-aged ischemic stroke survivors.
- Increased arterial stiffness is an independent predictor of diastolic dysfunction in this cohort, regardless of age, weight, hypertension, or LV mass.
Background:
Young and middle-aged ischemic stroke survivors have a high prevalence of hypertension, increased arterial stiffness and abnormal left ventricular (LV) geometry, which all are associated with the presence of LV diastolic dysfunction. However, the prevalence and covariates of diastolic dysfunction in these patients have not been reported.
Objectives:
To explore diastolic dysfunction in ischemic stroke patients aged 15-60 years included in the Norwegian Stroke in the Young Study.
Methods:
Data from 260 patients with acute ischemic stroke was analyzed. Diastolic dysfunction was assessed by combining transmitral peak early flow (E), early diastolic mitral annular velocity (e'), E/e' ratio, left atrial volume index and peak tricuspid regurgitant jet velocity, following current European guidelines. Carotid-femoral pulse wave velocity at least 10 m/s by aplanation tonometry was defined as increased arterial stiffness.
Results:
Prevalent diastolic dysfunction was found in 20% of patients (13% with diastolic dysfunction grade 1 and 7% with diastolic dysfunction grades 2-3). Patients with diastolic dysfunction were older and more likely to have hypertension, overweight, increased arterial stiffness, higher LV mass and less percentage nightly reduction in mean blood pressure (BP) (all P < 0.001). In a multivariable logistic regression analysis, diastolic dysfunction was associated with increased arterial stiffness [odds ratio 2.86 (95% confidence interval 1.05-7.79), P < 0.05] independent of age more than 45 years, overweight, hypertension, night-time BP reduction and LV mass.
Conclusion:
Among young and middle-aged ischemic stroke survivors, diastolic dysfunction was found in 20%. The presence of diastolic dysfunction was associated with increased arterial stiffness independent of higher age, overweight, hypertension, night-time BP reduction and LV mass.

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...