Related Experiment Video
Updated: Jul 31, 2026
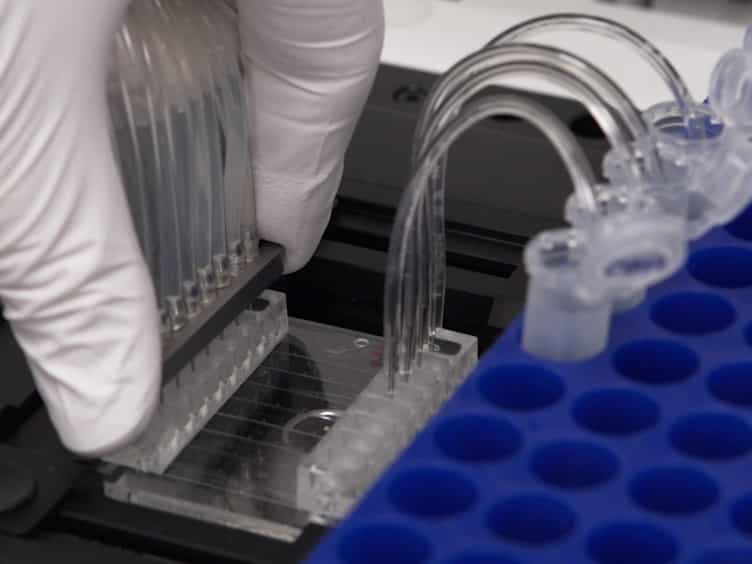

Microfluidic Flow Chambers Using Reconstituted Blood to Model Hemostasis and Platelet Transfusion In Vitro
Published on: March 19, 2016
The hemostatic effect of transfusing fresh whole blood versus platelet concentrates after cardiac operations
R Mohr1, U Martinowitz, J Lavee
1Department of Cardiac Surgery, Chaim Sheba Medical Center, Tel Hashomer, Israel.

The major cause of nonsurgical bleeding after cardiopulmonary bypass is delayed recovery of platelet count and function. Recovery of platelet count and function was compared in 27 patients who were randomized preoperatively to receive after cardiopulmonary bypass either 1 unit of fresh whole blood (15 patients) or 10 units of platelet concentrates (12 patients). Platelet count, bleeding time, platelet aggregation (adenosine diphosphate, collagen, epinephrine, and ristocetin) and platelet thromboxane formation were abnormal after cardiopulmonary bypass in all the patients. The increase of platelet count after 1 unit of fresh whole blood (from 115 +/- 32 X 10(9)/L to 148.5 +/- 36 X 10(9)/L) was similar to that achieved by 4 units of platelets (from 140 +/- 61 X 10(9)/L to 171 +/- 60 X 10(9)/L). The increase was doubled after 10 platelet units (from 140 +/- 61 X 10(9)/L to 209 +/- 55 X 10(9)/L). Bleeding time returned to normal values after fresh whole blood or after 8 platelet units. However, platelet thromboxane formation was higher after 1 unit of fresh whole blood than after 10 platelet units (95 +/- 25 versus 46 +/- 35 ng/ml, p less than 0.05), as was platelet aggregation response to collagen and epinephrine. The 24-hour blood loss was smaller in the fresh whole blood group (560 +/- 420 ml versus 770 +/- 360 ml), although the difference was not statistically significant. The results suggest that the hemostatic effect of 1 unit fresh whole blood after cardiopulmonary bypass is at least equal, if not superior, to the effect of 10 units of platelets.
The major cause of nonsurgical bleeding after cardiopulmonary bypass is delayed recovery of platelet count and function. Recovery of platelet count and function was compared in 27 patients who were randomized preoperatively to receive after cardiopulmonary bypass either 1 unit of fresh whole blood (15 patients) or 10 units of platelet concentrates (12 patients). Platelet count, bleeding time, platelet aggregation (adenosine diphosphate, collagen, epinephrine, and ristocetin) and platelet thromboxane formation were abnormal after cardiopulmonary bypass in all the patients. The increase of platelet count after 1 unit of fresh whole blood (from 115 +/- 32 X 10(9)/L to 148.5 +/- 36 X 10(9)/L) was similar to that achieved by 4 units of platelets (from 140 +/- 61 X 10(9)/L to 171 +/- 60 X 10(9)/L). The increase was doubled after 10 platelet units (from 140 +/- 61 X 10(9)/L to 209 +/- 55 X 10(9)/L). Bleeding time returned to normal values after fresh whole blood or after 8 platelet units. However, platelet thromboxane formation was higher after 1 unit of fresh whole blood than after 10 platelet units (95 +/- 25 versus 46 +/- 35 ng/ml, p less than 0.05), as was platelet aggregation response to collagen and epinephrine. The 24-hour blood loss was smaller in the fresh whole blood group (560 +/- 420 ml versus 770 +/- 360 ml), although the difference was not statistically significant. The results suggest that the hemostatic effect of 1 unit fresh whole blood after cardiopulmonary bypass is at least equal, if not superior, to the effect of 10 units of platelets.

Related Concept Videos
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...