Related Experiment Video
Updated: Jan 3, 2026
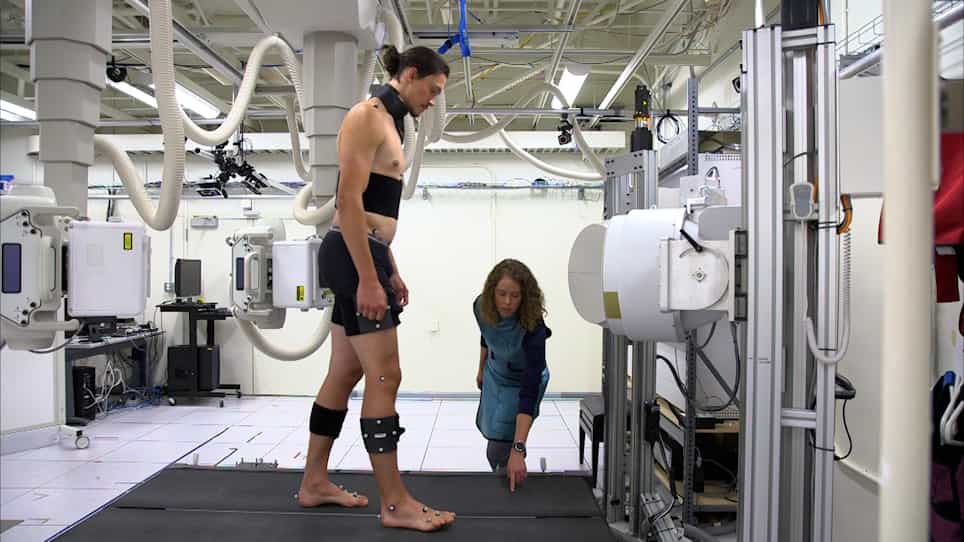

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Spinopelvic Compensatory Mechanisms for Reduced Hip Motion (ROM) in the Setting of Hip Osteoarthritis
Aaron J Buckland1, Leah Steinmetz1, Peter Zhou1
1Department of Orthopaedics, NYU Langone Orthopedic Hospital, 301 East 17th St, New York, NY 10003, USA.

Study Design:
Retrospective review from a single institution.
Objective:
To investigate the effect of hip osteoarthritis (OA) on spinopelvic compensatory mechanisms as a result of reduced hip range of motion (ROM) between sitting and standing.
Summary Of Background Data:
Hip OA results in reduced hip ROM and contracture, causing pain during postural changes. Hip flexion contracture is known to reduce the ability to compensate for spinal deformity while standing; however, the effects of postural spinal alignment change between sitting and standing is not well understood.
Methods:
Sit-stand radiographs of patients without prior spinal fusion or hip prosthesis were evaluated. Hip OA was graded by Kellgren-Lawrence grades and divided into low-grade (LOA; grade 0-2) and severe (SOA; grade 3 or 4) groups. Radiographic parameters evaluated were pelvic incidence (PI), pelvic tilt (PT), lumbar lordosis (LL), PI-LL, thoracic kyphosis (TK), SVA, T1-pelvic angle (TPA), T10-L2, proximal femoral shaft angle (PFSA), and hip flexion (PT change-PFSA change). Changes in sit-stand parameters were compared between LOA and SOA groups.
Results:
548 patients were included (LOA = 311; SOA = 237). After propensity score matching for age, body mass index, and PI, 183 LOA and 183 SOA patients were analyzed. Standing analysis demonstrated that SOA had higher SVA (31.1 vs. 21.7), lower TK (-36.2 vs. -41.1), and larger PFSA (9.1 vs. 7.4) (all p < .05). Sitting analysis demonstrated that SOA had higher PT (29.7 vs. 23.3), higher PI-LL (21.6 vs. 12.4), less LL (31.7 vs. 41.6), less TK (-33.2 vs. -38.6), and greater TPA (27.9 vs. 22.5) (all p < .05). SOA had less hip ROM from standing to sitting versus LOA (71.5 vs. 81.6) (p < .05). Therefore, SOA had more change in PT (15.2 vs. 7.3), PI-LL (20.6 vs. 13.7), LL (-21.4 vs. -13.1), and T10-L2 (-4.9 vs. -1.1) (all p < .001), allowing the femurs to change position despite reduced hip ROM. SOA had greater TPA reduction (15.1 vs. 9.6) and less PFSA change (86.7 vs. 88.8) compared with LOA (both p < .001).
Conclusions:
Spinopelvic compensatory mechanisms are adapted for reduced hip joint motion associated with hip OA in standing and sitting.
Level Of Evidence:
Level III.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 08:40
Author Spotlight: A Novel 3D-Printed Titanium Implant for Minimally Invasive Treatment of Hip Dysplasia in Young Dogs
Published on: April 19, 2024
Related Concept Videos
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:20
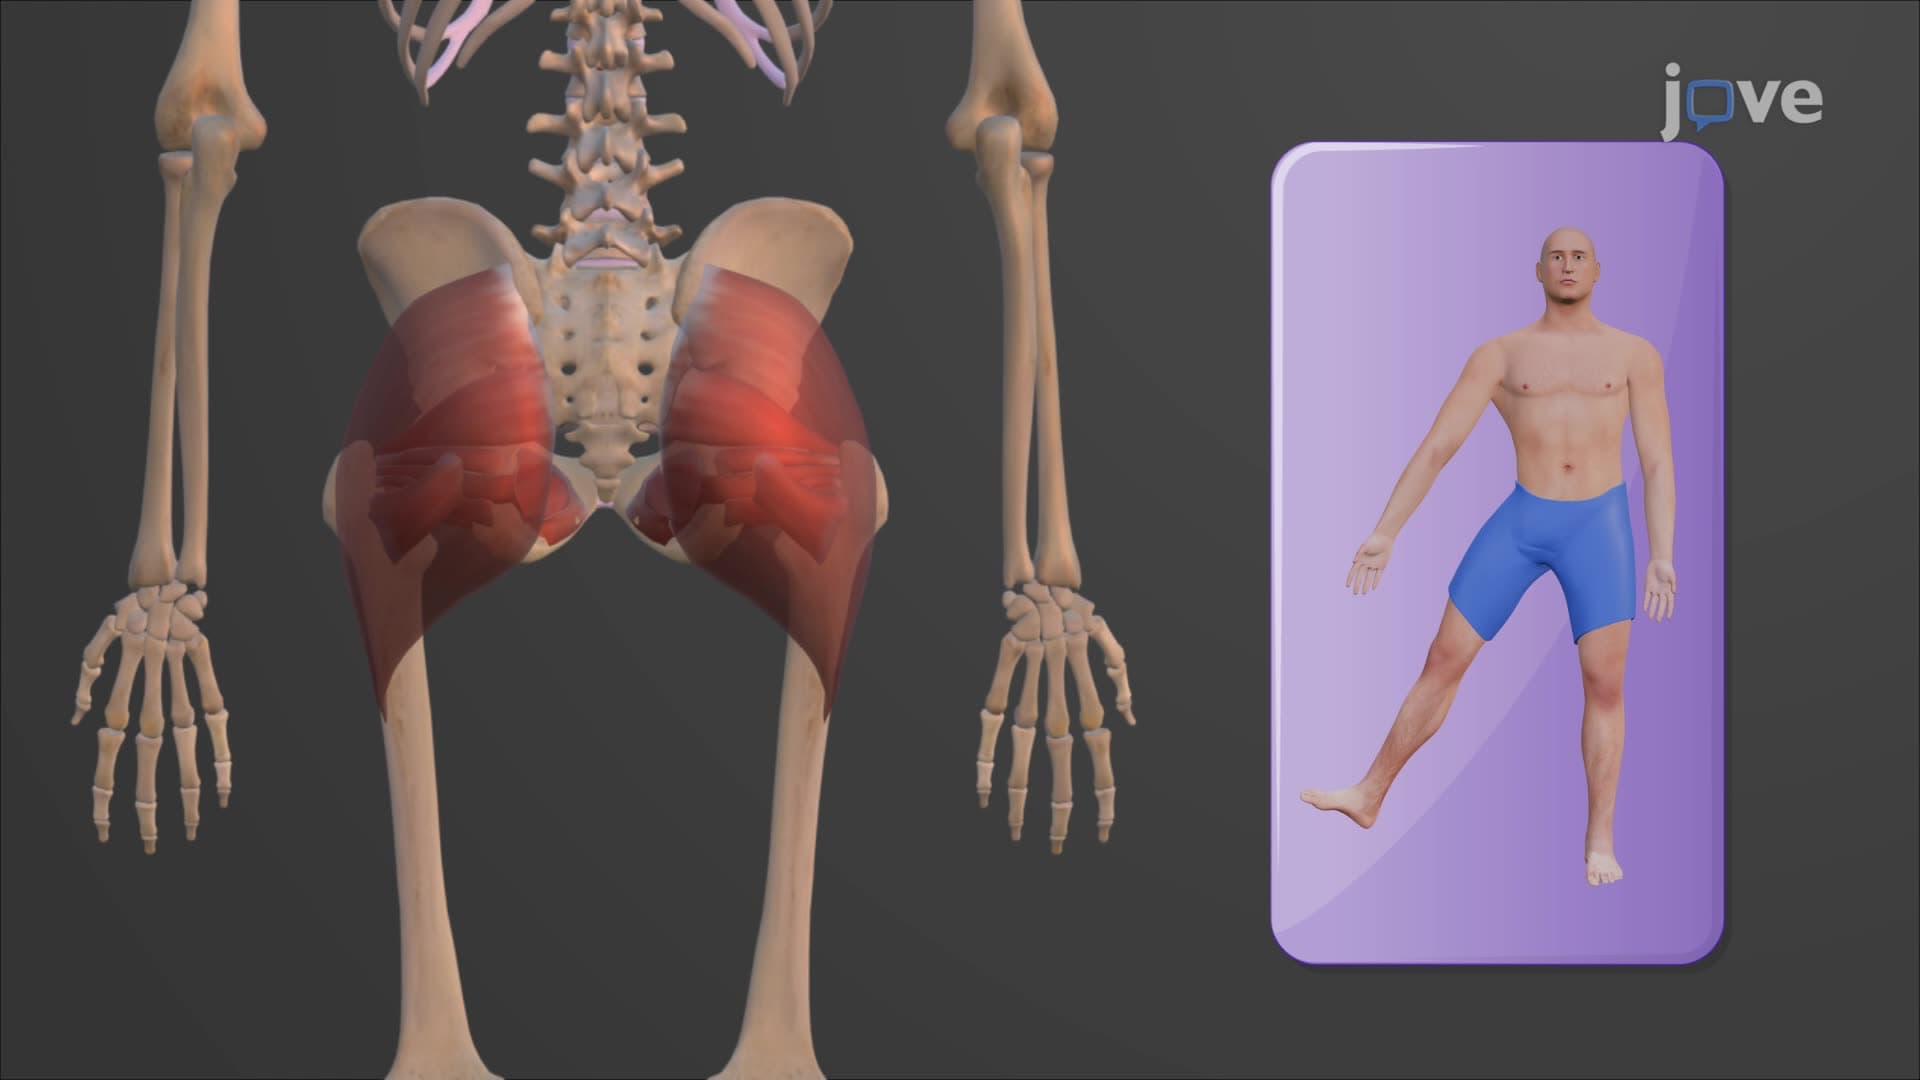
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...
 01:16
Bones of the Lower Limb: Femur and Patella