Related Experiment Video
Updated: Jan 3, 2026


Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
Electrocardiographic Effects of Propofol versus Etomidate in Patients with Brugada Syndrome
Panagiotis Flamée1, Varnavas Varnavas, Wendy Dewals
1From the Department of Anesthesiology and Perioperative Medicine (P.F., H.C., J.T.B., S.B., V.U., C.V., P.F., J.P.) the Heart Rhythm Management Center, Center of Heart and Vascular Disease (V.V., W.D., G-B.,C., P.B., C.d.A.), University Hospital Brussels the Interfaculty Center Data processing & Statistics (W.C.), Free University Brussels, Laarbeeklaan, Brussels, Belgium.

Background:
Brugada Syndrome is an inherited arrhythmogenic disease, characterized by the typical coved type ST-segment elevation in the right precordial leads from V1 through V3. The BrugadaDrugs.org Advisory Board recommends avoiding administration of propofol in patients with Brugada Syndrome. Since prospective studies are lacking, it was the purpose of this study to assess the electrocardiographic effects of propofol and etomidate on the ST- and QRS-segments. In this trial, it was hypothesized that administration of propofol or etomidate in bolus for induction of anesthesia, in patients with Brugada Syndrome, do not clinically affect the ST- and QRS-segments and do not induce arrhythmias.
Methods:
In this prospective, double-blinded trial, 98 patients with established Brugada syndrome were randomized to receive propofol (2 to 3 mg/kg) or etomidate (0.2 to 0.3 mg/kg) for induction of anesthesia. The primary endpoints were the changes of the ST- and QRS-segment, and the occurrence of new arrhythmias upon induction of anesthesia.
Results:
The analysis included 80 patients: 43 were administered propofol and 37 etomidate. None of the patients had a ST elevation greater than or equal to 0.2 mV, one in each group had a ST elevation of 0.15 mV. An ST depression up to -0.15mV was observed eleven times with propofol and five with etomidate. A QRS-prolongation of 25% upon induction was seen in one patient with propofol and three with etomidate. This trial failed to establish any evidence to suggest that changes in either group differed, with most percentiles being zero (median [25th, 75th], 0 [0, 0] vs. 0 [0, 0]). Finally, no new arrhythmias occurred perioperatively in both groups.
Conclusions:
In this trial, there does not appear to be a significant difference in electrocardiographic changes in patients with Brugada syndrome when propofol versus etomidate were administered for induction of anesthesia. This study did not investigate electrocardiographic changes related to propofol used as an infusion for maintenance of anesthesia, so future studies would be warranted before conclusions about safety of propofol infusions in patients with Brugada syndrome can be determined.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 09:20
Microelectrode Array Recording of Sinoatrial Node Firing Rate to Identify Intrinsic Cardiac Pacemaking Defects in Mice
Published on: July 5, 2021
Related Concept Videos
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:30
Cardiac Action Potential
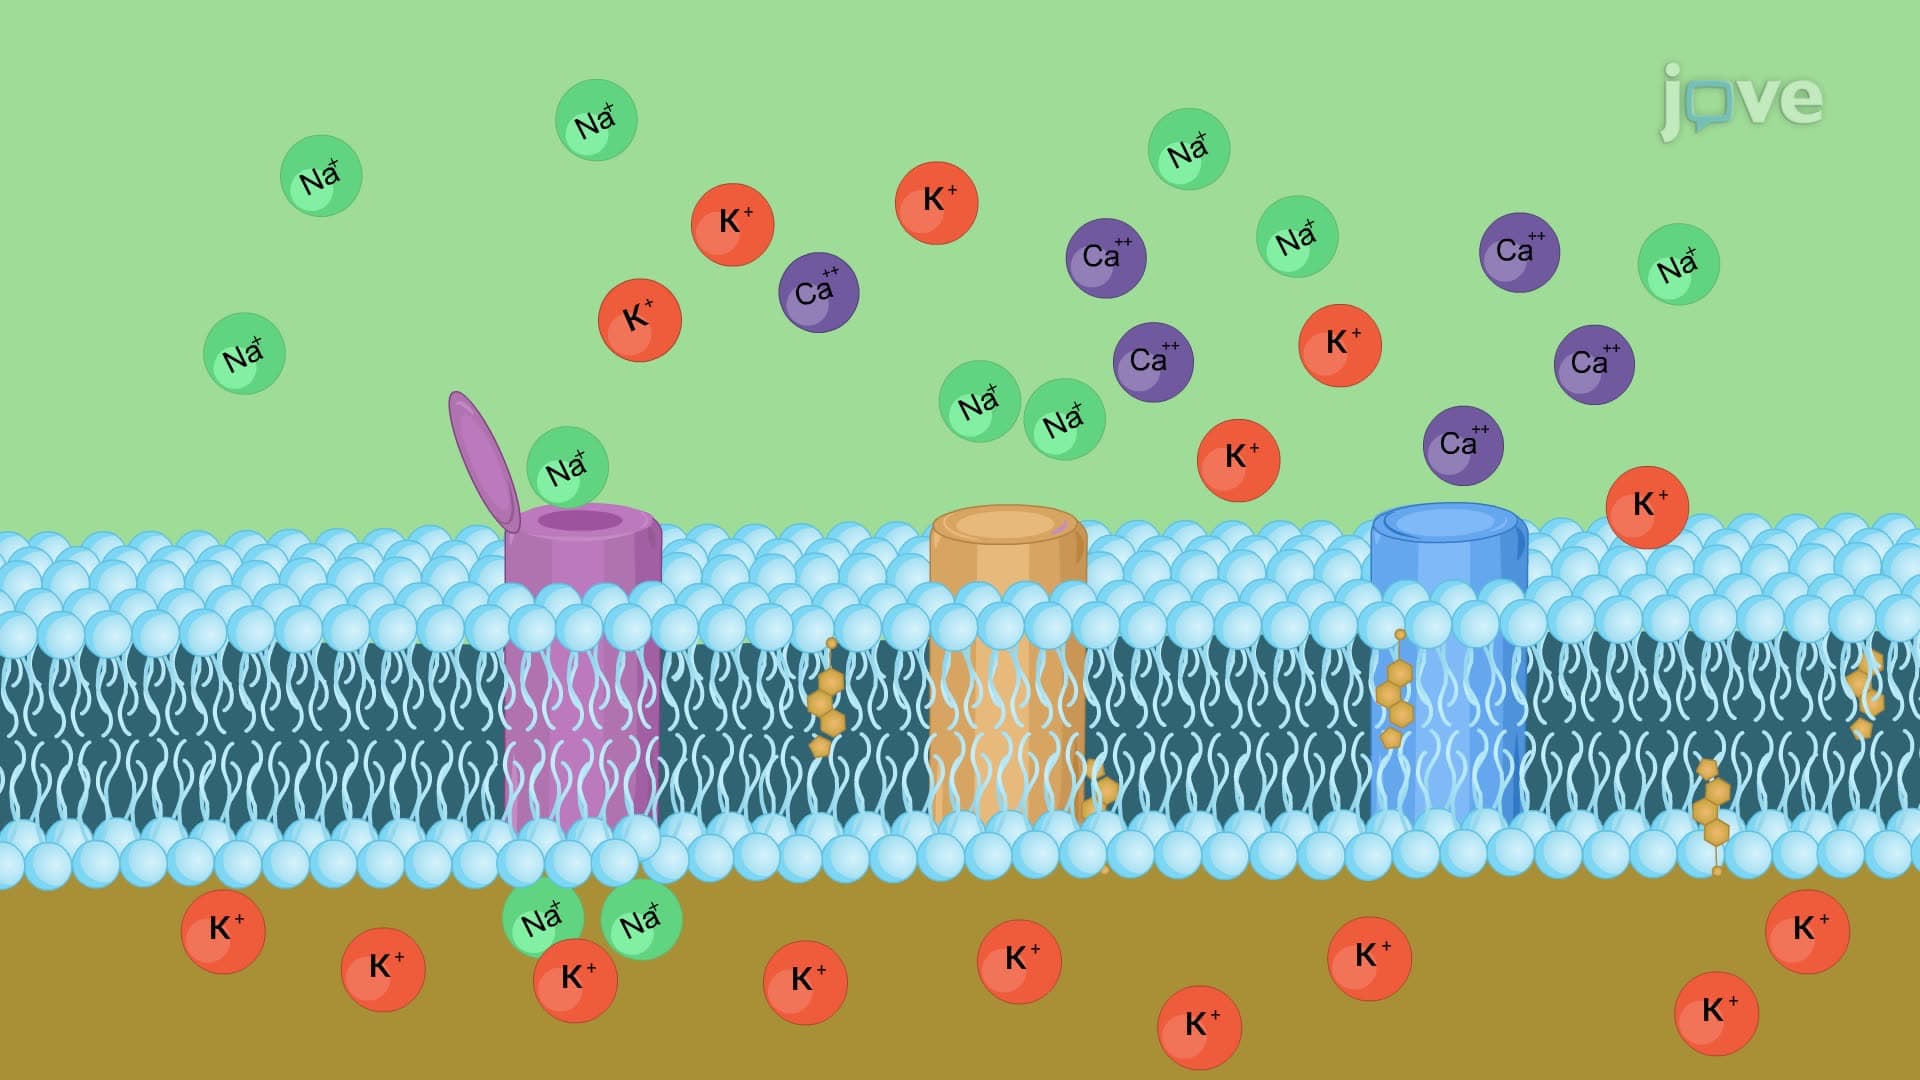
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:28
Mechanism of Cardiac Arrhythmias
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers