Related Experiment Video
Updated: Jan 3, 2026

In Vivo Quantitative Assessment of Myocardial Structure, Function, Perfusion and Viability Using Cardiac Micro-computed Tomography
Published on: February 16, 2016
Quantitative low-dose rest and stress CT myocardial perfusion imaging with a whole-heart coverage scanner improves
I-Lun Huang1,2, Ming-Ting Wu1,2, Chin Hu3
1Radiology, Kaohsiung Veteran General Hospital, Kaohsiung, Taiwan.

Insights
Low-dose CT imaging accurately detects coronary artery disease (CAD) by measuring myocardial blood flow (MBF) and myocardial perfusion reserve (MPR). Combining MPR and MBF significantly improves diagnostic accuracy for identifying significant coronary artery stenosis.
Area of Science:
- Cardiovascular imaging
- Radiology
- Medical diagnostics
Background:
- Coronary artery disease (CAD) diagnosis relies on assessing myocardial perfusion.
- Current methods like SPECT MPI have limitations.
- Low-dose CT offers a potential alternative for quantitative myocardial perfusion assessment.
Purpose of the Study:
- To evaluate the diagnostic accuracy of myocardial blood flow (MBF) and myocardial perfusion reserve (MPR) derived from low-dose dynamic contrast-enhanced (DCE) CT imaging.
- To assess the ability of CT-based MBF and MPR to detect functionally significant CAD.
Main Methods:
- Twenty-one patients with suspected CAD underwent rest and dipyridamole stress CT and SPECT MPI.
- Coronary angiography served as the reference standard.
- Low-dose DCE CT whole-heart coverage was used to generate MBF maps.
- Binomial logistic regression analyzed the diagnostic accuracy of CT-derived MBF and MPR.
Main Results:
- Mean stress MBF and MPR were significantly lower in ischemic segments compared to non-ischemic segments (p < 0.05).
- MPR demonstrated superior diagnostic power (AUC 0.916) compared to stress MBF (AUC 0.869) for differentiating ischemic from non-ischemic segments (p = 0.045).
- Concomitant use of MPR and stress MBF thresholds improved diagnostic accuracy for obstructive coronary lesions (per-vessel: 93.4%; per-segment: 90.0%).
- The estimated effective dose for CT MPI was low (3.04-3.19 mSv).
Conclusions:
- Quantitative rest and stress myocardial perfusion measurements using a large-coverage CT scanner enhance diagnostic accuracy for functionally significant coronary stenosis.
- Low-dose CT-based MBF and MPR show promise for non-invasive CAD detection.
- This technique offers a valuable tool for evaluating coronary artery disease severity.
Objective:
We evaluated the diagnostic accuracy of myocardial blood flow (MBF) and perfusion reserve (MPR) measured from low-dose dynamic contrast-enhanced (DCE) imaging with a whole-heart coverage CT scanner for detecting functionally significant coronary artery disease (CAD).
Methods:
Twenty one patients with suspected or known CAD had rest and dipyridamole stress MBF measurements with CT and SPECT myocardial perfusion imaging (MPI), and lumen narrowing assessment with coronary angiography (catheter and/or CT based) within 6 weeks. SPECT MBF measurements and coronary angiography were used together as reference to determine the functional significance of coronary artery stenosis. In each CT MPI study, DCE images of the whole heart were acquired with breath-hold using a low-dose acquisition protocol to generate MBF maps. Binomial logistic regression analysis was used to determine the diagnostic accuracy of CT-measured MBF and MPR (ratio of stress to rest MBF) for assessing functionally significant coronary stenosis.
Results:
Mean stress MBF and MPR in ischemic segments were lower than those in non-ischemic segments (1.37 ± 0.34 vs. 2.14 ± 0.64 ml/min/g; 1.56 ± 0.41 vs. 2.53 ± 0.70; p < 0.05 for all). The receiver operating characteristic curve analysis revealed that MPR (AUC 0.916, 95%CI: 0.885-0.947) had a superior power than stress MBF (AUC 0.869, 95%CI: 0.830-0.909) for differentiating non-ischemic and ischemic myocardial segments (p = 0.045). On a per-vessel and per-segment analysis, concomitant use of MPR and stress MBF thresholds further improved the diagnostic accuracy compared to MPR or stress MBF alone for detecting obstructive coronary lesions (per-vessel: 93.4% vs. 83.6% and 88.5%, respectively; per-segment: 90.0% vs. 83.7% and 83.1%, respectively). The estimated effective dose of a rest and stress CT MPI study was 3.04 and 3.19 mSv respectively.
Conclusion:
Quantitative rest and stress myocardial perfusion measurement with a large-coverage CT scanner improves the diagnostic accuracy for detecting functionally significant coronary stenosis.


Related Concept Videos
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:26
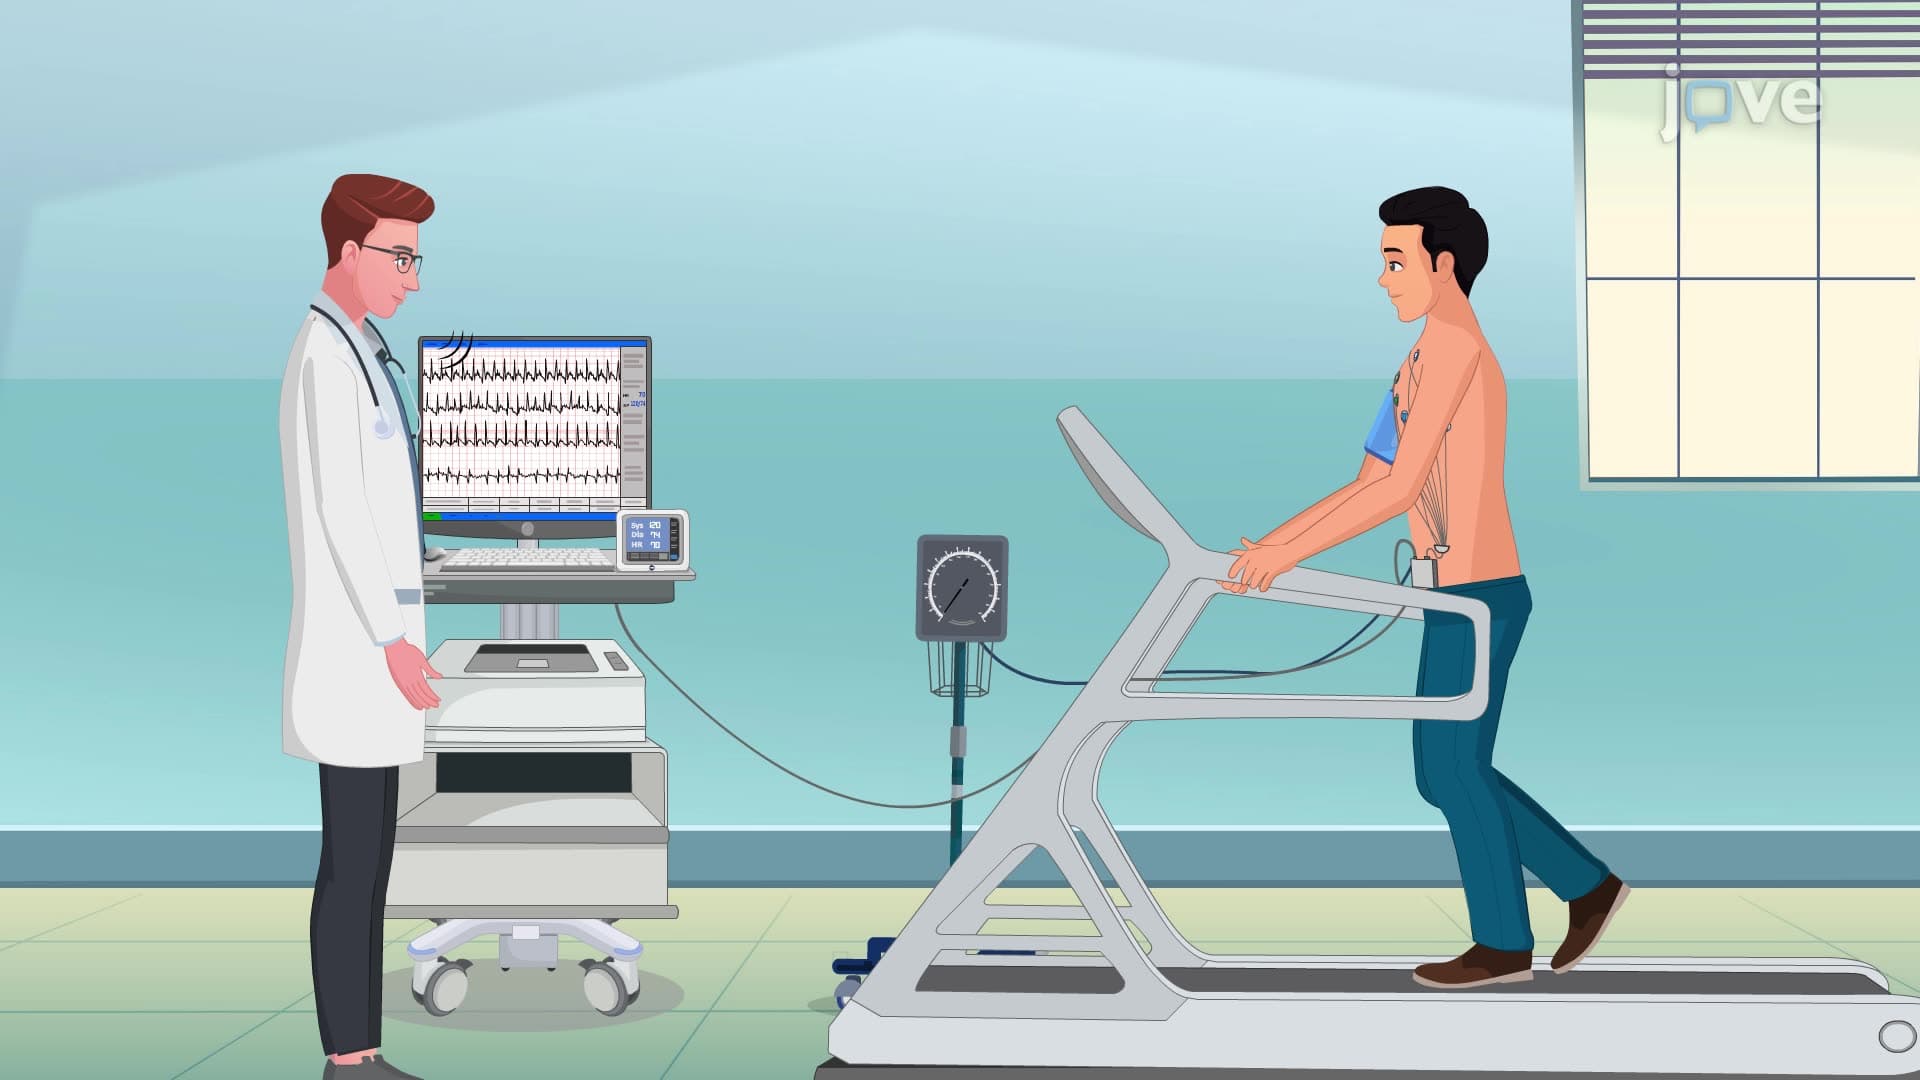
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...