Related Experiment Video
Updated: Jan 3, 2026
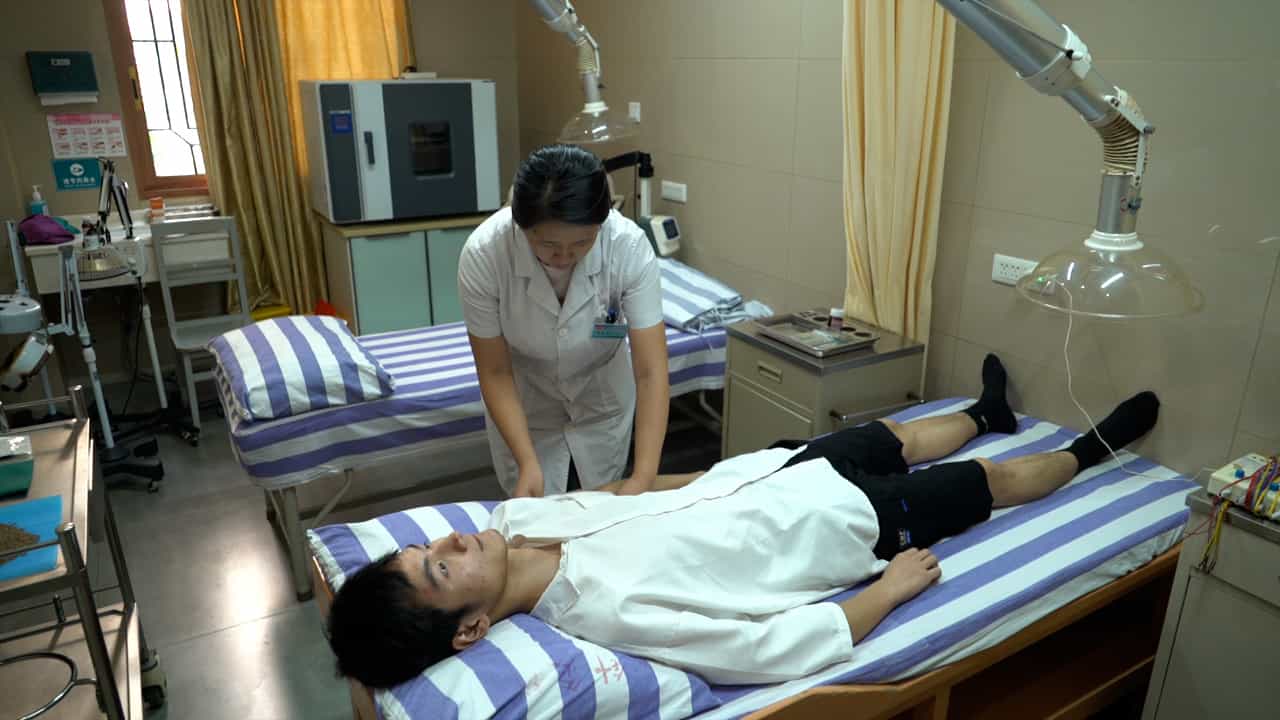

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Impact of treatment for fecal incontinence on constipation symptoms
Uduak U Andy1, J Eric Jelovsek2, Benjamin Carper3
1Department of Obstetrics and Gynecology, University of Pennsylvania, Philadelphia, PA.

Objective:
Defecatory symptoms, such as a sense of incomplete emptying and straining with bowel movements, are paradoxically present in women with fecal incontinence. Treatments for fecal incontinence, such as loperamide and biofeedback, can worsen or improve defecatory symptoms, respectively. The primary aim of this study was to compare changes in constipation symptoms in women undergoing treatment for fecal incontinence with education only, loperamide, anal muscle exercises with biofeedback or both loperamide and biofeedback. Our secondary aim was to compare changes in constipation symptoms among responders and nonresponders to fecal incontinence treatment.
Study Design:
This was a planned secondary analysis of a randomized controlled trial comparing 2 first-line therapies for fecal incontinence in a 2 × 2 factorial design. Women with at least monthly fecal incontinence and normal stool consistency were randomized to 4 groups: (1) oral placebo plus education only, (2) oral loperamide plus education only, (3) placebo plus anorectal manometry-assisted biofeedback, and (4) loperamide plus biofeedback. Defecatory symptoms were measured using the Patient Assessment of Constipation Symptoms questionnaire at baseline, 12 weeks, and 24 weeks. The Patient Assessment of Constipation Symptoms consists of 12 items that contribute to a global score and 3 subscales: stool characteristics/symptoms (hardness of stool, size of stool, straining, inability to pass stool), rectal symptoms (burning, pain, bleeding, incomplete bowel movement), and abdominal symptoms (discomfort, pain, bloating, cramps). Scores for each subscale as well as the global score range from 0 (no symptoms) to 4 (maximum score), with negative change scores representing improvement in defecatory symptoms. Responders to fecal incontinence treatment were defined as women with a minimally important clinical improvement of ≥5 points on the St Mark's (Vaizey) scale between baseline and 24 weeks. Intent-to-treat analysis was performed using a longitudinal mixed model, controlling for baseline scores, to estimate changes in Patient Assessment of Constipation Symptoms scores from baseline through 24 weeks.
Results:
At 24 weeks, there were small changes in Patient Assessment of Constipation Symptoms global scores in all 4 groups: oral placebo plus education (-0.3; 95% confidence interval, -0.5 to -0.1), loperamide plus education (-0.1, 95% confidence interval, -0.3 to0.0), oral placebo plus biofeedback (-0.3, 95% confidence interval, -0.4 to -0.2), and loperamide plus biofeedback (-0.3, 95% confidence interval, -0.4 to -0.2). No differences were observed in change in Patient Assessment of Constipation Symptoms scores between women randomized to placebo plus education and those randomized to loperamide plus education (P = .17) or placebo plus biofeedback (P = .82). Change in Patient Assessment of Constipation Symptoms scores in women randomized to combination loperamide plus biofeedback therapy was not different from that of women randomized to treatment with loperamide or biofeedback alone. Responders had greater improvement in Patient Assessment of Constipation Symptoms scores than nonresponders (-0.4; 95% confidence interval, -0.5 to -0.3 vs -0.2; 95% confidence interval, -0.3 to -0.0, P < .01, mean difference, 0.2, 95% confidence interval, 0.1-0.4).
Conclusion:
Change in constipation symptoms following treatment of fecal incontinence in women are small and are not significantly different between groups. Loperamide treatment for fecal incontinence does not worsen constipation symptoms among women with normal consistency stool. Women with clinically significant improvement in fecal incontinence symptoms report greater improvement in constipation symptoms.

Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:22
Drugs Affecting GI Tract Motility: Bulk-Forming and Stimulant Laxatives
Bulk-forming laxatives, such as psyllium, methylcellulose, and polycarbophil, absorb water in the intestine, increasing stool bulk and promoting bowel movement. This...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...