Related Experiment Video
Updated: Jan 3, 2026


Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
A Case of Ileocecal IgG4-Related Sclerosing Mesenteritis Diagnosed by Endoscopic Ultrasound-Guided Fine Needle
Yuichi Takano1, Fumitaka Niiya1, Takahiro Kobayashi1
1Division of Gastroenterology, Department of Internal Medicine, Showa University Fujigaoka Hospital, Yokohama, Kanagawa, Japan.

A 25-year-old woman had undergone removal of a cryptogenic tumor in the left maxillary sinus 1 year prior to presentation. The patient experienced abdominal pain for 4 days with repeated vomiting episodes; therefore, she was transferred to our hospital by an ambulance. Contrast-enhanced computed tomography revealed a 3-cm tumor in the ileocecal region, which caused small bowel obstruction. Contrast imaging of the ileus tube showed extrinsic compression of the ileocecal region. Forward-viewing linear echoendoscope revealed an irregular hypoechoic tumor measuring 3 cm outside the gastrointestinal tract. Using a 25G needle, endoscopic ultrasound-guided fine needle aspiration (EUS-FNA) was performed. Pathological finding was an inflammatory fibrous tissue with diffuse lymphoplasmacytic infiltration, with more than 10 IgG4-positive cells detected in a high-power field. Re-examination of a pathology specimen of the maxillary sinus tumor provided by the previous attending physician revealed that the inflammatory tissue had diffuse lymphoplasmacytic infiltration, which were accompanied by storiform fibrosis and obliterative phlebitis. Immunostaining revealed more than 50 IgG4-positive cells in a high-power field, a finding suggestive of IgG4-related disease. The serum IgG4 level was 21 mg/dl, which was within the normal range. Treatment was initiated with prednisolone at a dose of 50 mg/day, and the dose was later tapered off. CT and MRI performed 2 months later showed complete disappearance of the ileocecal tumor. The final diagnosis was asynchronously occurring IgG4-related maxillary sinusitis and sclerosing mesenteritis.
A 25-year-old woman had undergone removal of a cryptogenic tumor in the left maxillary sinus 1 year prior to presentation. The patient experienced abdominal pain for 4 days with repeated vomiting episodes; therefore, she was transferred to our hospital by an ambulance. Contrast-enhanced computed tomography revealed a 3-cm tumor in the ileocecal region, which caused small bowel obstruction. Contrast imaging of the ileus tube showed extrinsic compression of the ileocecal region. Forward-viewing linear echoendoscope revealed an irregular hypoechoic tumor measuring 3 cm outside the gastrointestinal tract. Using a 25G needle, endoscopic ultrasound-guided fine needle aspiration (EUS-FNA) was performed. Pathological finding was an inflammatory fibrous tissue with diffuse lymphoplasmacytic infiltration, with more than 10 IgG4-positive cells detected in a high-power field. Re-examination of a pathology specimen of the maxillary sinus tumor provided by the previous attending physician revealed that the inflammatory tissue had diffuse lymphoplasmacytic infiltration, which were accompanied by storiform fibrosis and obliterative phlebitis. Immunostaining revealed more than 50 IgG4-positive cells in a high-power field, a finding suggestive of IgG4-related disease. The serum IgG4 level was 21 mg/dl, which was within the normal range. Treatment was initiated with prednisolone at a dose of 50 mg/day, and the dose was later tapered off. CT and MRI performed 2 months later showed complete disappearance of the ileocecal tumor. The final diagnosis was asynchronously occurring IgG4-related maxillary sinusitis and sclerosing mesenteritis.
Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:27
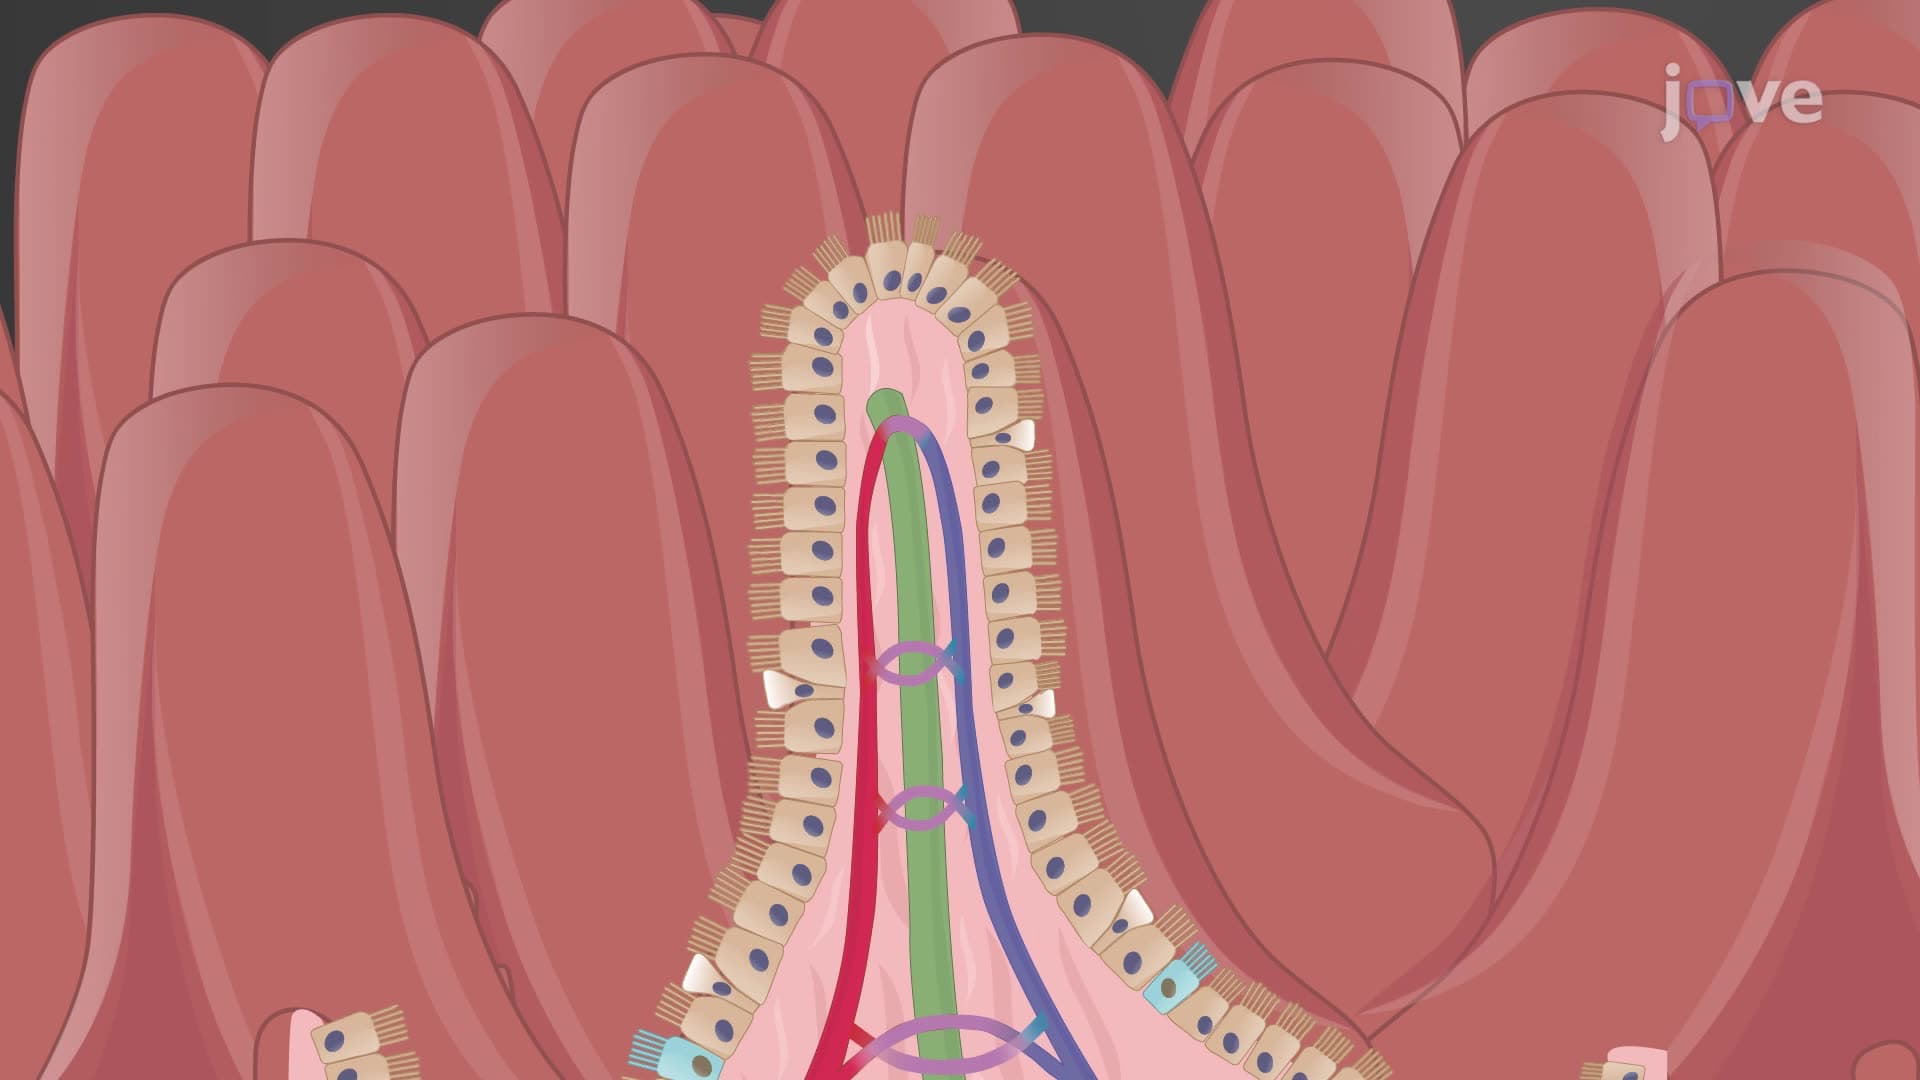
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are: