Related Experiment Video
Updated: Jan 2, 2026

Isolation and Identification of Waterborne Antibiotic-Resistant Bacteria and Molecular Characterization of their Antibiotic Resistance Genes
Published on: March 3, 2023
The effect of varying multidrug-resistence (MDR) definitions on rates of MDR gram-negative rods
Aline Wolfensberger1, Stefan P Kuster1, Martina Marchesi2
11Division of Infectious Diseases and Hospital Epidemiology, University Hospital and University of Zurich, Rämistrasse 100, CH-8091 Zurich, Switzerland.

Background:
A multitude of definitions determining multidrug resistance (MDR) of Gram-negative organisms exist worldwide. The definitions differ depending on their purpose and on the issueing country or organization. The MDR definitions of the European Centre for Disease Prevention and Control (ECDC) were primarily chosen to harmonize epidemiological surveillance. The German Commission of Hospital Hygiene and Infection Prevention (KRINKO) issued a national guideline which is mainly used to guide infection prevention and control (IPC) measures. The Swiss University Hospital Zurich (UHZ) - in absentia of national guidelines - developed its own definition for IPC purposes. In this study we aimed to determine the effects of different definitions of multidrug-resistance on rates of Gram-negative multidrug-resistant organisms (GN-MDRO).
Methods:
MDR definitions of the ECDC, the German KRINKO and the Swiss University Hospital Zurich were applied on a dataset comprising isolates of Escherichia coli, Klebsiella pneumoniae, Enterobacter sp., Pseudomonas aeruginosa, and Acinetobacter baumannii complex. Rates of GN-MDRO were compared and the percentage of patients with a GN-MDRO was calculated.
Results:
In total 11'407 isolates from a 35 month period were included. For Enterobacterales and P. aeruginosa, highest MDR-rates resulted from applying the 'ECDC-MDR' definition. 'ECDC-MDR' rates were up to four times higher compared to 'KRINKO-3/4MRGN' rates, and up to six times higher compared to UHZ rates. Lowest rates were observed when applying the 'KRINKO-4MRGN' definitions. Comparing the 'KRINKO-3/4MRGN' with the UHZ definitions did not show uniform trends, but yielded higher rates for E. coli and lower rates for P. aeruginosa. On the patient level, the percentages of GN-MDRO carriers were 2.1, 5.5, 6.6, and 18.2% when applying the 'KRINKO-4MRGN', 'UHZ-MDR', 'KRINKO-3/4MRGN', and the 'ECDC-MDR' definition, respectively.
Conclusions:
Different MDR-definitions lead to considerable variation in rates of GN-MDRO. Differences arise from the number of antibiotic categories required to be resistant, the categories and drugs considered relevant, and the antibiotic panel tested. MDR definitions should be chosen carefully depending on their purpose and local resistance rates, as definitions guiding isolation precautions have direct effects on costs and patient care.
More Related Videos
 05:06
Author Spotlight: Advancing Antibiotic Resistance Research Using an Efflux-Deficient Bacterial Strain and a Single-Copy Gene Expression System
Published on: January 5, 2024
 08:04
Quantitative Examination of Antibiotic Susceptibility of Neisseria gonorrhoeae Aggregates Using ATP-utilization Commercial Assays and Live/Dead Staining
Published on: February 8, 2019
Related Concept Videos
 01:30
Development of Antibiotic Resistance
 01:28
Antimicrobial Effectiveness
 01:15
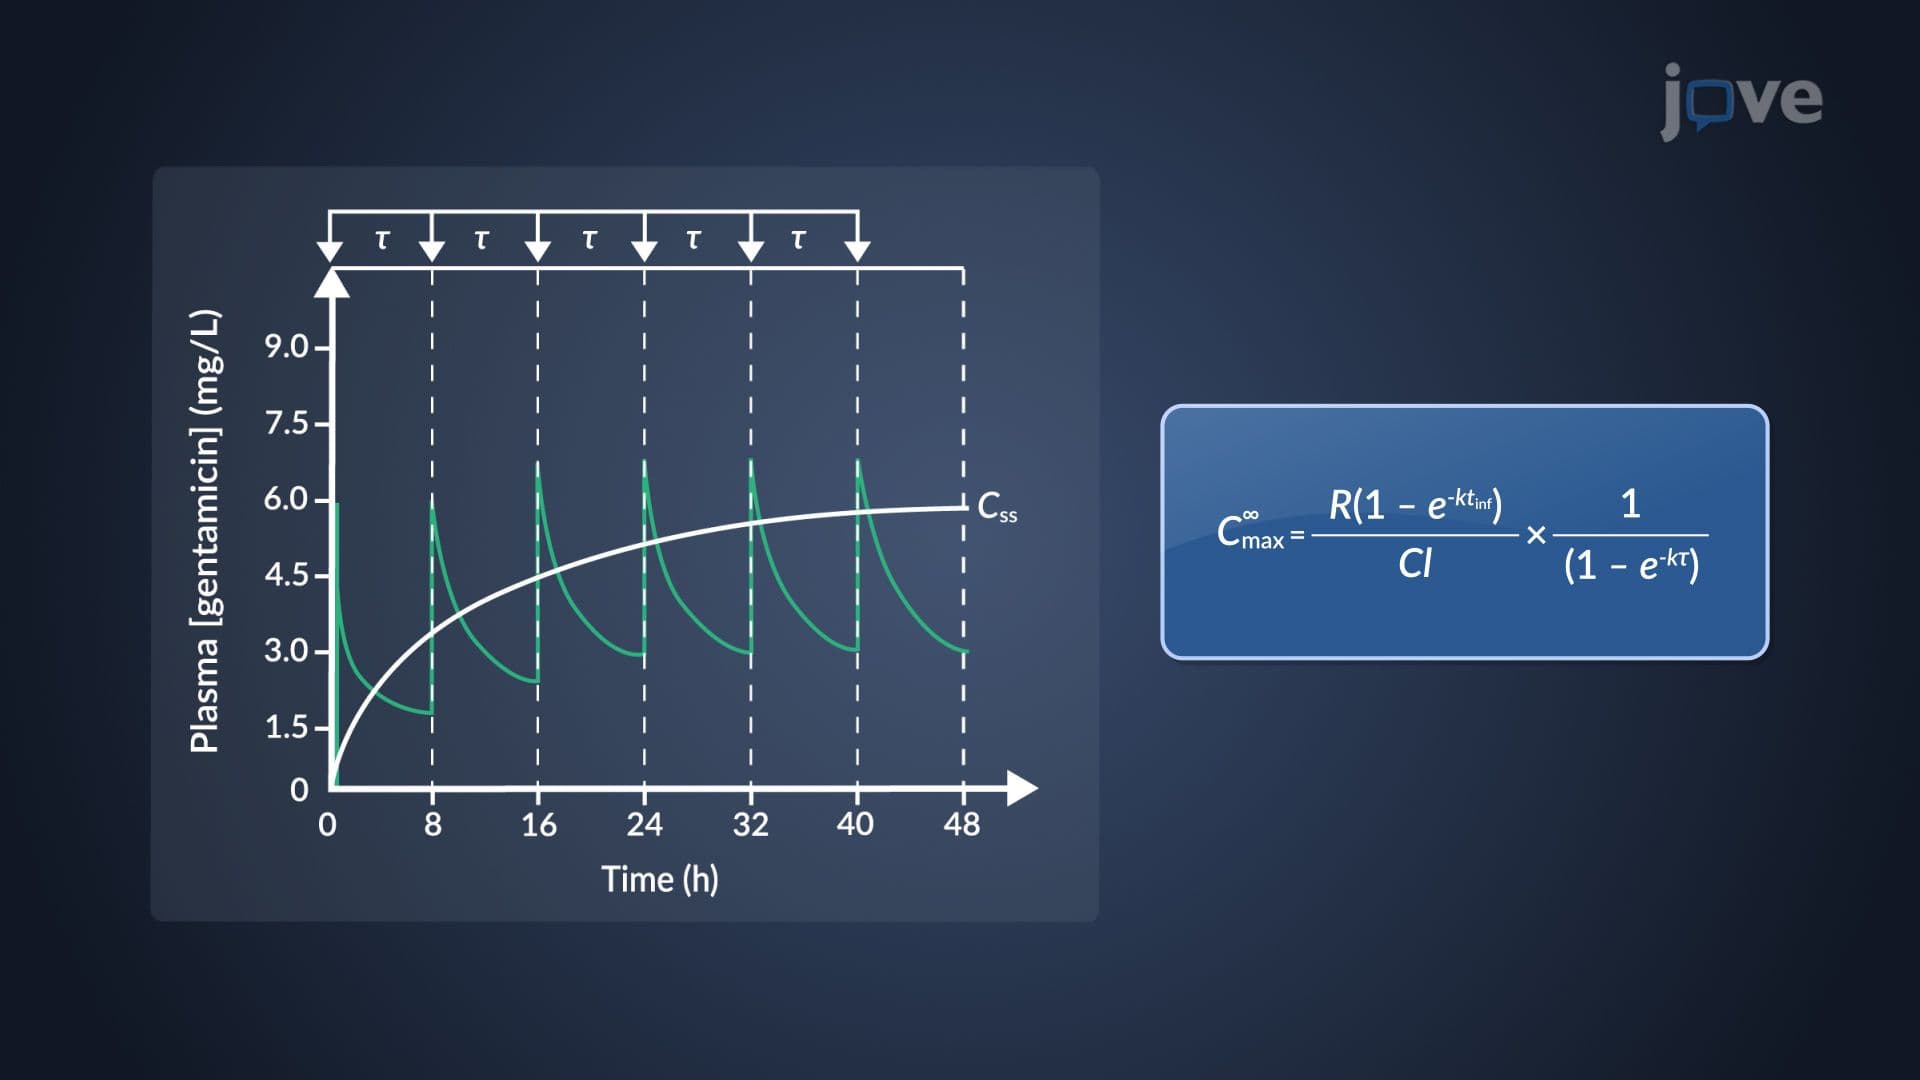
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations