Related Experiment Video
Updated: Aug 9, 2026


Detection of Disease-associated α-synuclein by Enhanced ELISA in the Brain of Transgenic Mice Overexpressing Human A53T Mutated α-synuclein
Published on: May 30, 2015
Primary immunodeficiency-related bronchiectasis in adults: comparison with bronchiectasis of other etiologies in a
Hélène Goussault1, Hélène Salvator2,3,4, Emilie Catherinot1
1Service de Pneumologie, Hôpital Foch, Suresnes, France.

Background:
Bronchiectasis is a heterogeneous disease depending on etiology. It represents the most frequent non-infectious pulmonary complication of primary immunodeficiencies (PID). We investigated whether bronchiectasis associated with PID had a distinct course in comparison to bronchiectasis of other causes.
Methods:
Retrospective single-center study of adult patients diagnosed with non-cystic fibrosis bronchiectasis with more than 5 years of follow-up and at least 4 pulmonary functional tests available at one year apart. They were divided into three groups: PID- related bronchiectasis, idiopathic/post infectious-related bronchiectasis and other causes of bronchiectasis. Respiratory functional data and clinical outcomes were compared.
Results:
Of 329 patients with bronchiectasis diagnosed in Foch Hospital (Suresnes, France), 98 patients fulfilled the selected criteria (20 PID-related cases, 39 idiopathic or post-infectious cases, and 39 cases with other causes). Median time of follow-up was 9.5 years. Groups were similar concerning initial characteristics (female 70.4%, never smokers 59.2%, mild severity bronchiectasis according to the FACED score and median FEV1 at diagnosis 73.5% predicted values [Q1-Q3: 53.75-90.5]), except PID patients who were younger (median age of 51.5 vs 62 years, p = 0.02). Eighty-five percent of PID patients received immunoglobulin substitution (median trough level was measured at 10.5 g/dl [10;10.92]). Global median FEV1 annual decline was 25.03 ml/year [8.16;43.9] and 19.82 ml/year [16.08;48.02] in the PID patients group. Forty-five percent of patients had bacterial colonization, pneumoniae occurred in 56% of patients and median exacerbation annual rate was 0.8 [0.3-1.4]. Hemoptysis occurred in 31.6% of patients. Global mortality rate was 11.2%. We did not record any significant difference for all clinical and functional outcomes between patients with PID and other etiologies. The median decline in FEV1 was similar in the three groups.
Conclusions:
The course of PID-related bronchiectasis was similar to bronchiectasis of other causes. Provided that patients receive immunoglobulin replacement, the course of PID-related bronchiectasis seems to be independent of the underlying immune disorder.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease
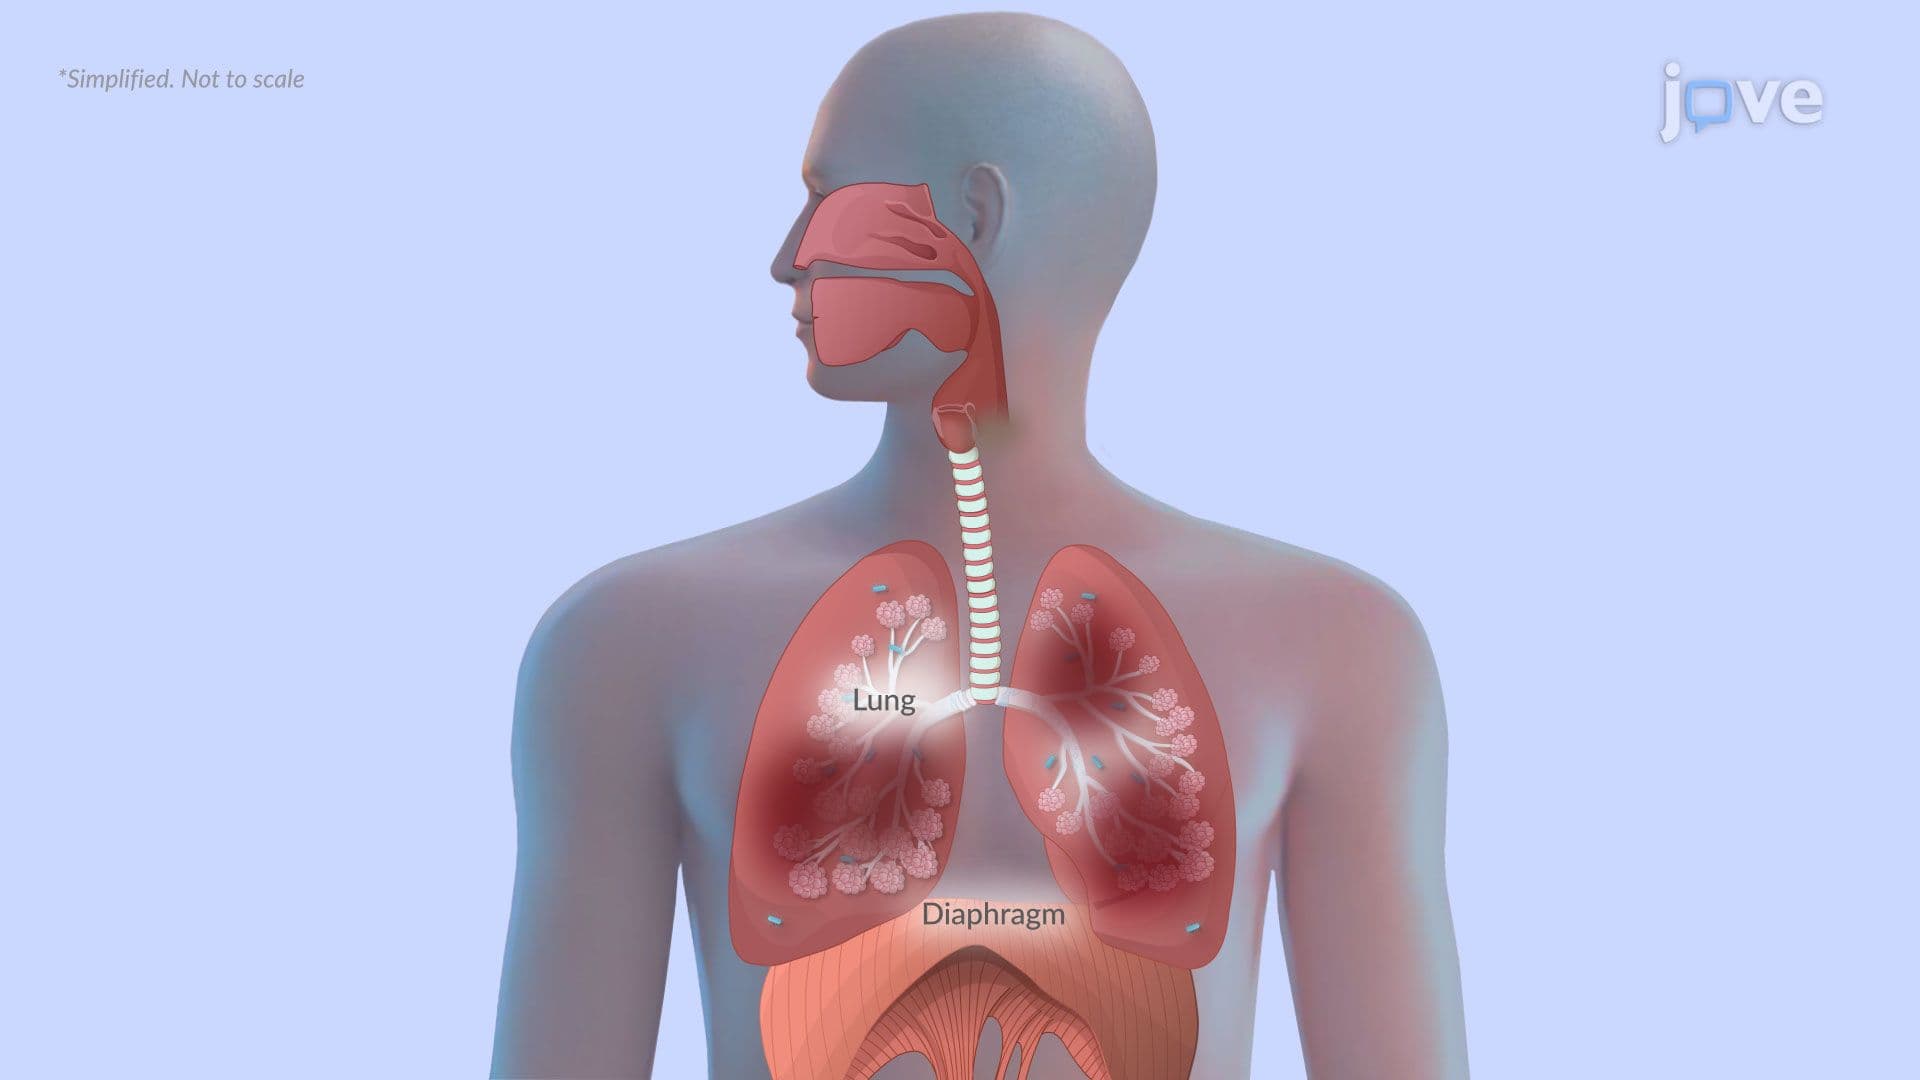
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations