
Sedation with midazolam worsens the diaphragm function than dexmedetomidine and propofol during mechanical
Shao-Ping Li1, Xian-Long Zhou1, Yan Zhao1
1169 Donghu Road, Emergency Center, Zhongnan Hospital of Wuhan University, Wuhan, Hubei, 430071, China.

Background:
Mechanical ventilation (MV) is identified as an independent contributor to diaphragmatic atrophy and contractile dysfunction. Appropriate sedation is also essential during MV, and anesthetics may have direct adverse effects on the diaphragm. However, there is a lack of research into the effects of different anesthetics on diaphragm function during MV.
Objectives:
In the present study, we aim to examine the effect of midazolam, dexmedetomidine, and propofol on diaphragm function during MV.
Design:
Animal study.
Setting:
University research laboratory.
Subjects:
Male Wistar rats.
Interventions:
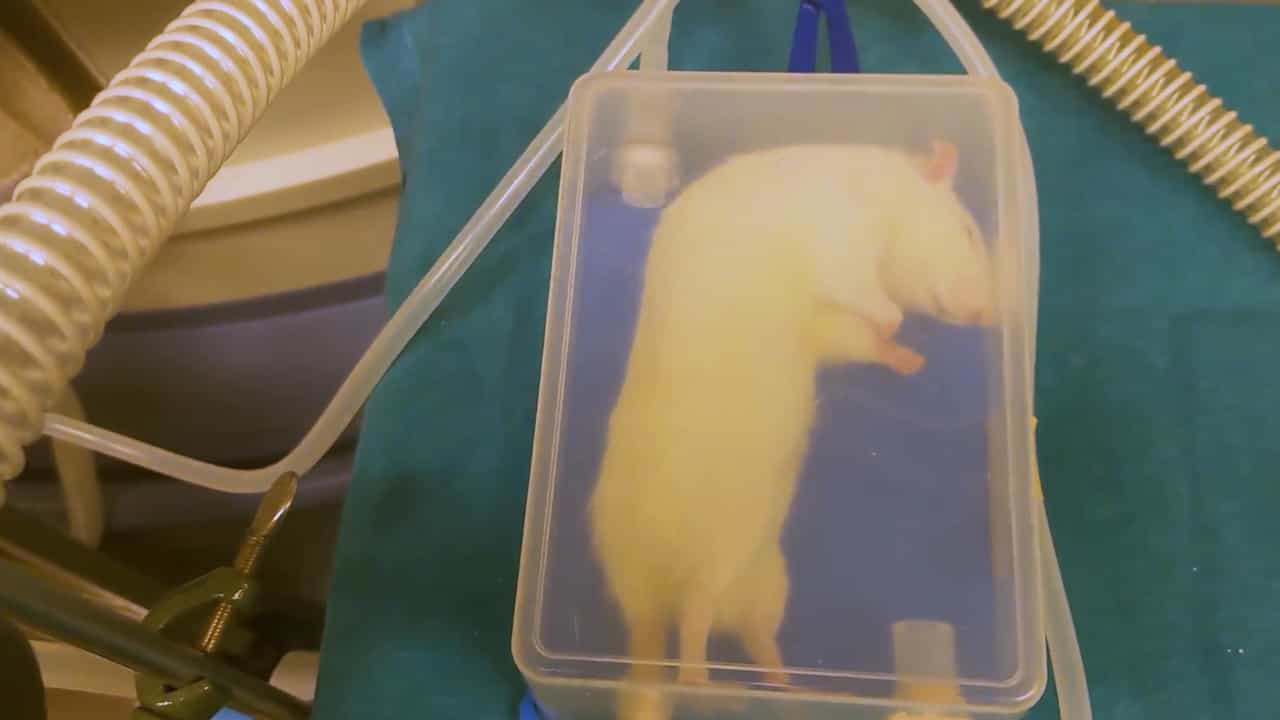
Animals were experienced 12 h of MV or spontaneous breathing (SB) with continuous anesthetics infusion. Diaphragm contractile properties, cross-sectional areas, microcirculation, oxidative stress, and proteolysis were examined.
Measurements And Main Results:
Diaphragmatic specific force was markedly reduced in the midazolam group compared with the dexmedetomidine (-60.4 ± 3.01%, p < 0.001) and propofol group (-58.3 ± 2.60%, p < 0.001) after MV. MV sedated with midazolam induced more atrophy of type II fibers compared with dexmedetomidine (-21.8 ± 2.11%, p = 0.0001) and propofol (-8.2 ± 1.53%, p = 0.003). No significant differences of these indices were found in the midazolam, dexmedetomidine, and propofol groups under SB condition (all p > 0.05, respectively). Twelve hours of MV resulted in a time dependent reduction in diaphragmatic functional capillary density (PB -25.1%, p = 0.0001; MZ -21.6%, p = 0.0003; DD -15.2%, p = 0.022; PP -24.8%, p = 0.0001, respectively), which did not occur in the gastrocnemius muscle. The diaphragmatic lipid peroxidation adducts 4-HNE and HIF-1α levels were significantly lower in dexmedetomidine group and propofol group compared to midazolam group (p < 0.05, respectively). Meanwhile, the catalase and SOD levels were also relatively lower (p < 0.05, respectively) in midazolam group compared to dexmedetomidine group and propofol group.
Conclusions:
Twelve hours of mechanical ventilation during midazolam sedation led to a more severe diaphragm dysfunction than dexmedetomidine and propofol, possibly caused by its relative weaker antioxidant capacity.
Insights
Midazolam sedation during mechanical ventilation (MV) significantly impairs diaphragm function and causes atrophy more than dexmedetomidine or propofol. This suggests midazolam may have a weaker antioxidant effect, impacting diaphragm health during MV.
Area of Science:
- Critical Care Medicine
- Anesthesiology
- Respiratory Physiology
Background:
- Mechanical ventilation (MV) is a known cause of diaphragmatic atrophy and dysfunction.
- Anesthetics used during MV may also adversely affect diaphragm function.
- Limited research exists on the comparative effects of different anesthetics on the diaphragm during MV.
Purpose of the Study:
- To investigate the impact of midazolam, dexmedetomidine, and propofol on diaphragm function during mechanical ventilation.
- To compare the effects of these anesthetics on diaphragmatic contractile properties, muscle fiber atrophy, microcirculation, and oxidative stress.
Main Methods:
- An animal study involving male Wistar rats.
- Rats underwent 12 hours of mechanical ventilation or spontaneous breathing with continuous anesthetic infusion.
- Evaluated diaphragmatic contractile properties, cross-sectional areas, microcirculation, oxidative stress (4-HNE, HIF-1α), and antioxidant enzyme levels (catalase, SOD).
Main Results:
- Midazolam sedation during MV significantly reduced diaphragmatic specific force and increased type II fiber atrophy compared to dexmedetomidine and propofol.
- MV led to reduced diaphragmatic functional capillary density in all anesthetic groups, with no significant difference from gastrocnemius muscle.
- Midazolam group showed lower antioxidant capacity (catalase, SOD) and higher oxidative stress markers (4-HNE, HIF-1α) compared to dexmedetomidine and propofol groups.
Conclusions:
- Midazolam sedation during 12 hours of MV results in more severe diaphragm dysfunction and atrophy than dexmedetomidine or propofol.
- The increased diaphragm dysfunction with midazolam may be attributed to its weaker antioxidant capacity.
- These findings highlight the importance of anesthetic choice in mitigating diaphragm injury during mechanical ventilation.


Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:22
Stages of General Anesthesia
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:20
Inhalational Anesthetics: Overview
 01:19
Depolarizing Blockers: Pharmocokinetics