Related Experiment Video
Updated: Jan 2, 2026


E-Patient Counseling Trial E-PACO: Computer Based Education versus Nurse Counseling for Patients to Prepare for Colonoscopy
Published on: August 1, 2019
Pretest and Post-test Probabilities of Diagnoses of Rectal Evacuation Disorders Based on Symptoms, Rectal Exam, and
Justin Brandler1, Michael Camilleri1
1Clinical Enteric Neuroscience Translational and Epidemiological Research (CENTER), Division of Gastroenterology and Hepatology, Mayo Clinic, Rochester, Minnesota.

Background & Aims:
There is controversy over the utility of symptoms, examination, and tests for diagnosis of rectal evacuation disorders (REDs) or slow-transit constipation (STC). We aimed to ascertain the pooled prevalence, sensitivity, specificity, and likelihood ratios for clinical parameters to determine pretest and post-test probabilities of diagnoses of RED and STC without RED.
Methods:
We searched the MEDLINE and PUBMED databases since 1999 for studies that used binary data to calculate sensitivity, specificity, and likelihood ratios to determine the diagnostic utility of history, symptoms, and tests for RED and STC. RED and STC were defined based on confirmation by at least 1 objective anorectal test or colonic transit test. Controls had normal test results based on the specific protocol in each study.
Results:
We reviewed 100 articles; 63 studies of RED and 61 studies of STC met the inclusion criteria. Among 3364 patients with chronic constipation, objective tests demonstrated RED alone, 27.2%; normal transit constipation alone, 37.2%; STC alone, 19.0%; and RED with STC, 16.6%. To diagnose RED, discriminant features were urinary symptoms (specificity, 100%; likelihood ratio, above 10; 58 patients), less than 2 findings of dyssynergia in a digital rectal exam (sensitivity, 83.2%; negative likelihood ratio, 0.2; 462 patients) and rectoanal pressure gradient below -40 mm Hg with high anal pressure during straining (specificity, 100%; likelihood ratio, above 10; 101 patients). The features most strongly associated with STC alone were call to stool (specificity, 91.5%; likelihood ratio, 10.5; 75 patients) and absence of abdominal distension, fullness, or bloating (sensitivity, 92.9%; negative likelihood ratio, 0.1; 93 patients).
Conclusions:
In a systematic review, we found specific symptoms, lack of dyssynergia in a digital rectal exam, and findings on anorectal manometry to be highly informative and critical in evaluation of RED and STC.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems...
 01:27
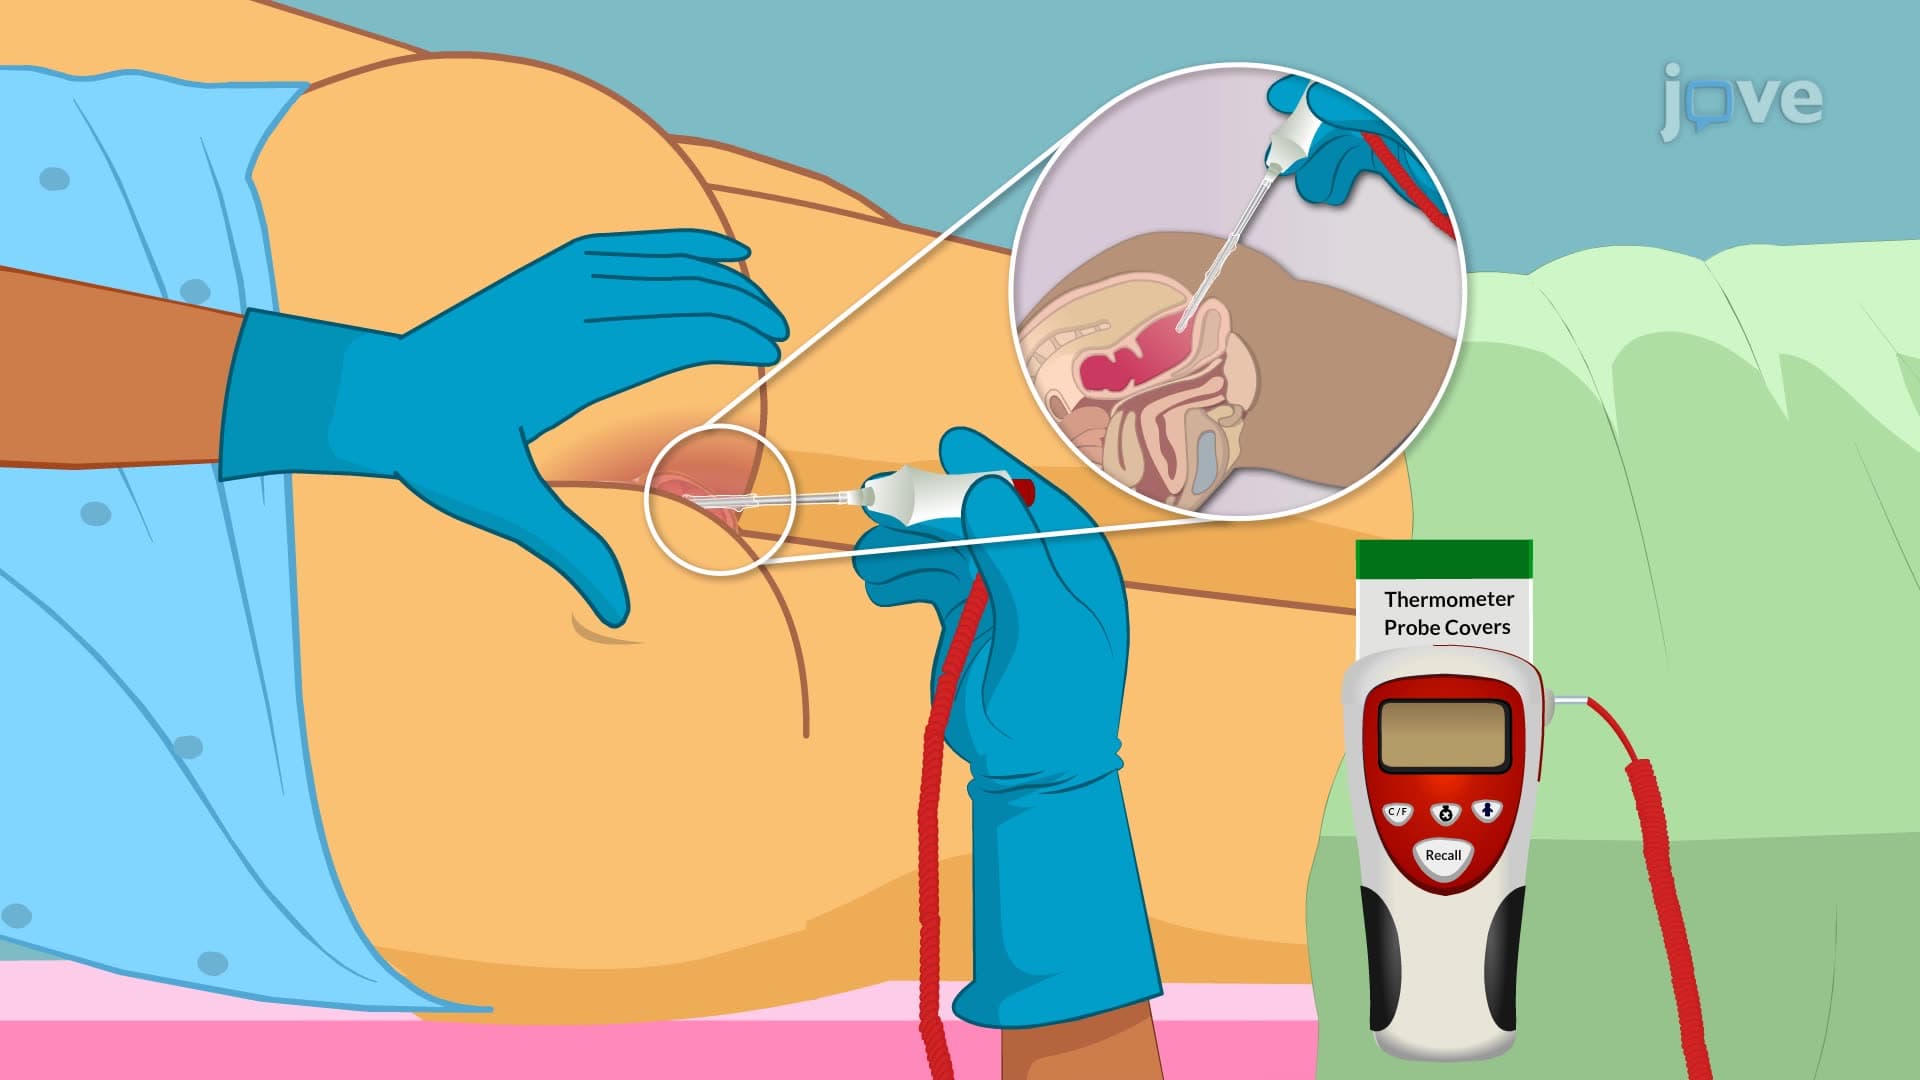
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and...
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...