Related Experiment Video
Updated: Jan 2, 2026
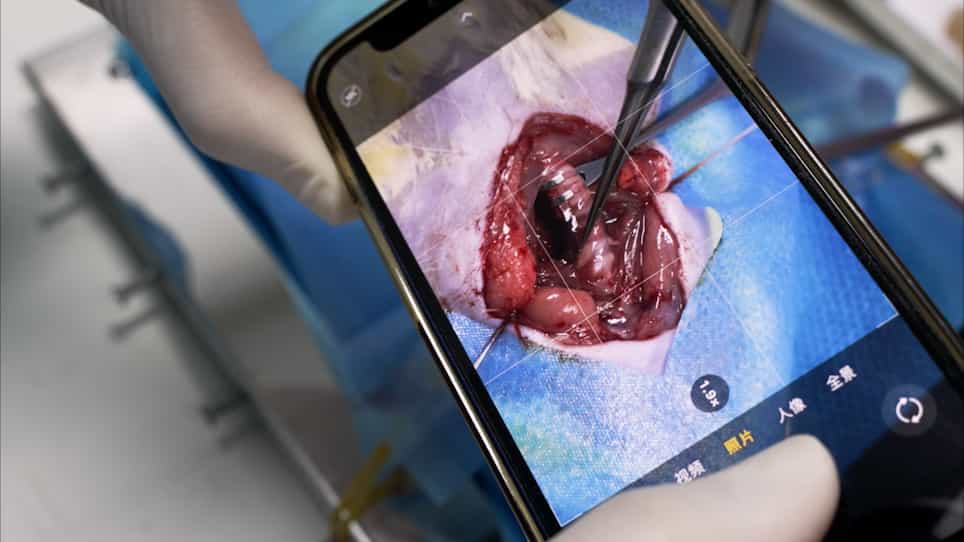

Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Complex management decisions in a woman with concurrent primary hyperparathyroidism and metastatic papillary thyroid
Lorena Arnez1, Victor Lawrence1
1St Mary's Hospital, Isle of Wight NHS Trust, Newport, UK.

Summary:
A 40-year-old woman was hospitalised at 25-week gestation following a diagnosis of severe symptomatic hypercalcaemia (adjusted serum calcium 3.02 mmol/L). A diagnosis of primary hyperparathyroidism (PHP) was made on the basis of elevated parathyroid hormone (PTH) 11.2 pmol/L (reference range 1.5-6.9) and exclusion of familial hypocalciuric hypercalcaemia. Ultrasound examination of the neck did not convincingly demonstrate an abnormal or enlarged parathyroid gland and parathyroid scintigraphy was not performed due to maternal choice relating to perceived radiation risk to the foetus. At neck exploration during the 28th week of pregnancy a right lower pole parathyroid lesion was excised together with two abnormal lymph nodes (largest 1.6 cm). Histology confirmed a parathyroid adenoma and also papillary thyroid carcinoma deposits in the two resected lymph nodes. Post-operatively, levels of adjusted serum calcium normalised and pregnancy progressed uneventfully to term. Total thyroidectomy was performed 2 weeks after delivery revealing two small foci of papillary micro-carcinoma (largest 2.3 mm, one in each thyroid lobe) with no evidence of further metastatic tumour in lymph nodes removed during functional neck dissection. Radioiodine remnant ablation (RRA) was performed 2 months post thyroidectomy to allow for breast involution. The patient remains in full clinical and biochemical remission 9 years later. We present and review the difficult management decisions faced in relation to the investigation and treatment of PHP in pregnancy, further complicated by incidentally discovered locally metastatic pT1aN1aM0 papillary thyroid carcinoma.
Learning Points:
PHP may have serious consequences during pregnancy and usually requires surgical management during pregnancy to reduce the risk of maternal and foetal complications. The indications for and optimal timing of surgical management are discussed. Localisation by parathyroid scintigraphy is controversial during pregnancy: modified dose regimes may be considered in preference as an alternative to unguided neck exploration. Breastfeeding is contraindicated for 6-8 weeks before radioactive-iodine remnant ablation (RRA) to prevent increased breast uptake. Breastfeeding is further contra-indicated until after a subsequent pregnancy. Incidentally discovered differentiated thyroid carcinoma (DTC) in cervical lymph nodes in some cases may be managed expectantly because in one quarter of thyroidectomies the primary tumour remains occult.

Related Concept Videos
 00:59
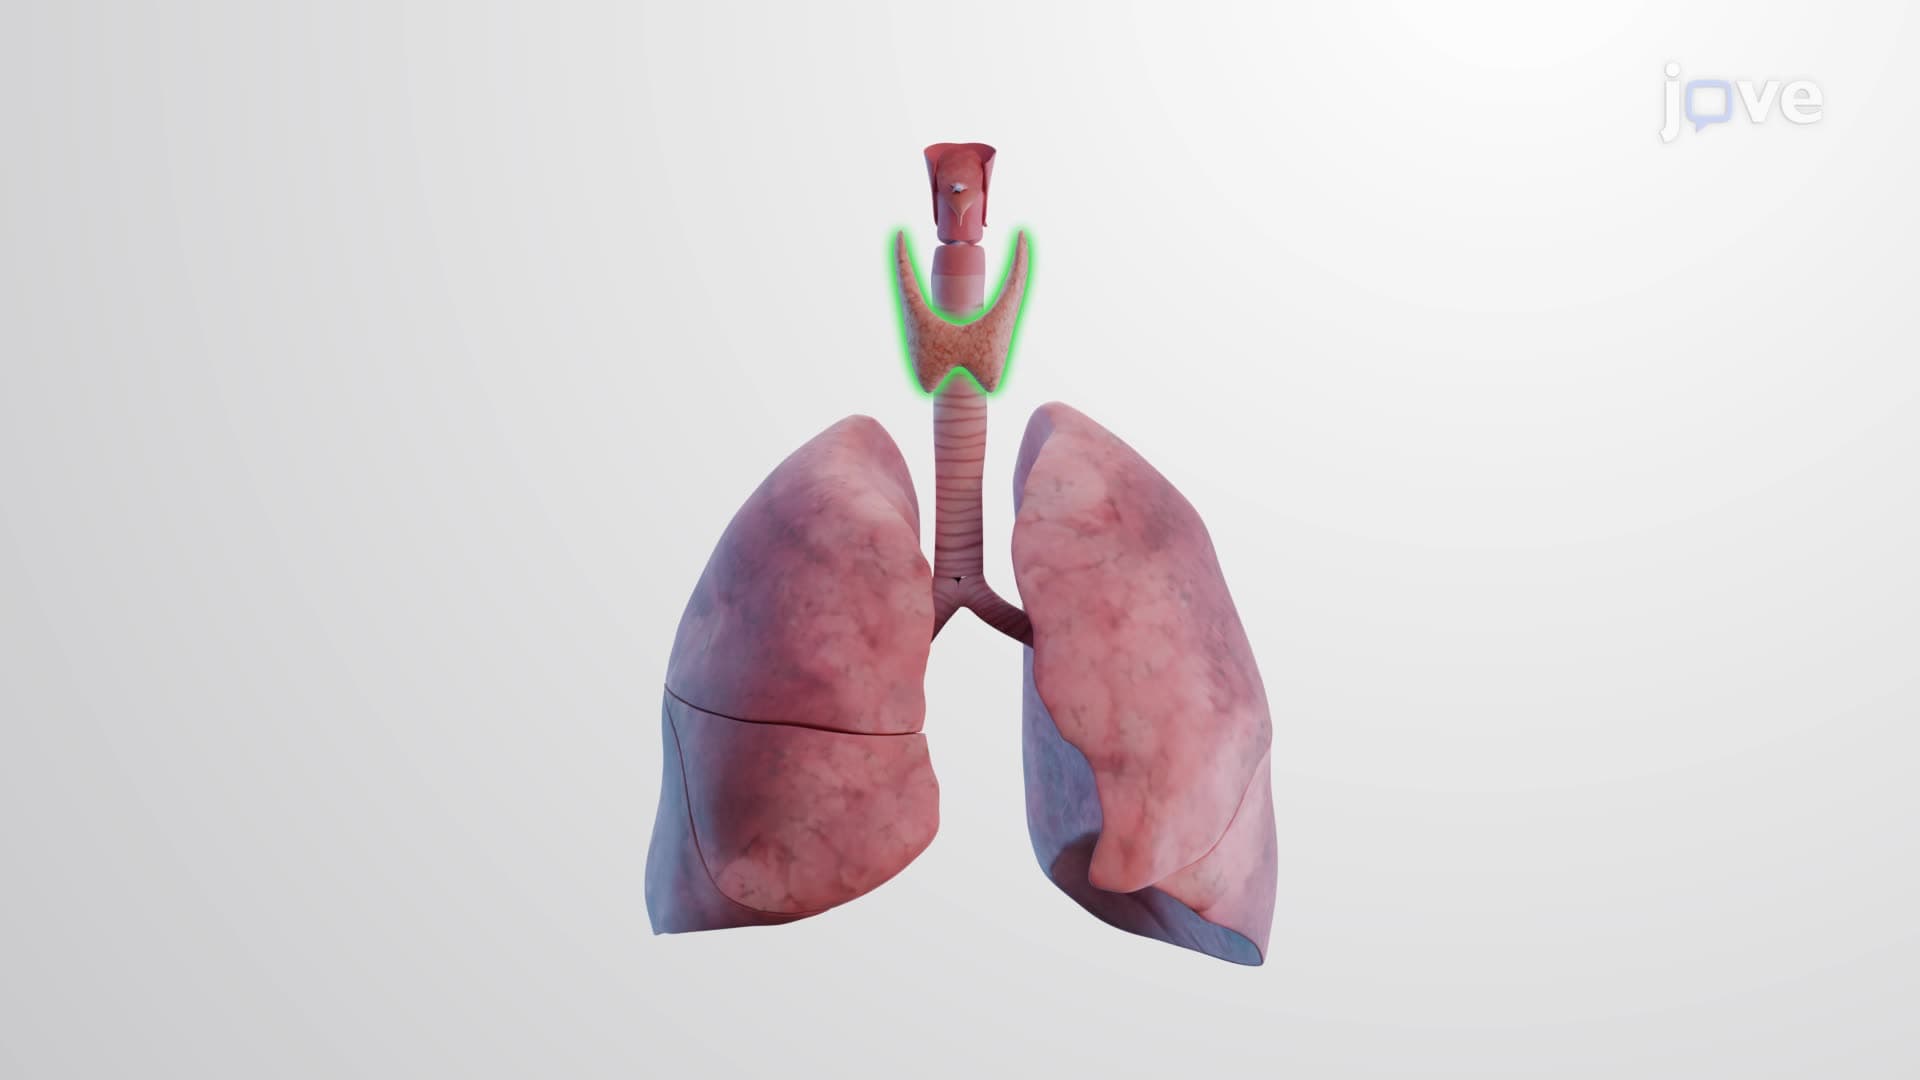
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:28
Urinary Tract Calculi V: Nursing Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:25
Peritoneal Dialysis III: Nursing Management