High Cervical Carotid Endarterectomy-Outcome Analysis
Tomomasa Kondo1, Nakao Ota1, Felix Göhre2
1Department of Neurosurgery and Stroke Center, Sapporo Teishinkai Hospital, Higashi-ku, Sapporo, Hokkaido.

Insights
Carotid endarterectomy (CEA) for high cervical lesions yields outcomes comparable to non-high cervical cases. Careful blood pressure management post-surgery is crucial to prevent perioperative-related cerebral infarction.
Area of Science:
- Vascular Surgery
- Cerebrovascular Disease
- Surgical Technique
Background:
- Carotid endarterectomy (CEA) for high cervical internal carotid artery stenosis presents technical challenges due to distal dissection difficulties.
- Effective surgical strategies are needed to improve outcomes for these complex cases.
Purpose of the Study:
- To report a specific surgical technique for CEA in high cervical lesions.
- To analyze the surgical outcomes and identify risk factors for complications in these patients.
Main Methods:
- Retrospective analysis of 98 patients undergoing CEA between December 2013 and June 2018.
- Definition of high cervical lesions as plaque rostral to the C2 vertebral level (n=34).
- Detailed description of surgical steps including incision extension, nerve exposure, and anatomical structure retraction.
Main Results:
- Surgical outcomes for high cervical lesions were equivalent to non-high cervical lesions.
- No significant difference in technique-related or perioperative-related cerebral infarction (PRCI) between high and non-high cervical groups.
- Postoperative diastolic blood pressure changes identified as a risk factor for PRCI (P=0.033).
Conclusions:
- CEA for high cervical lesions can achieve outcomes similar to those for non-high cervical lesions.
- Prudent blood pressure management in the early postoperative period is essential to mitigate the risk of PRCI.
Objective:
Carotid endarterectomy (CEA) for high cervical internal carotid artery stenosis is considered to be technically demanding because of the difficulty in dissecting the distal end. We report the surgical technique and outcome analysis of CEA for high cervical lesions.
Methods:
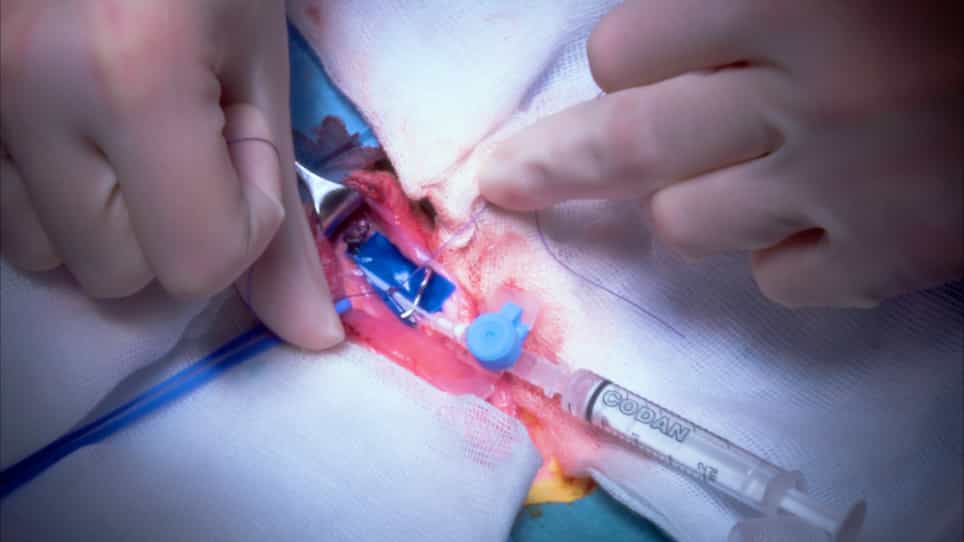
We retrospectively analyzed the records of 98 patients treated by CEA from December 2013 to June 2018. The plaque positions rostral to the C2 vertebral level was defined as the high cervical lesions (n = 34). The surgical technique is to successfully expose the distal end, as follows: 1) extend the skin incision; 2) expose the great auricular nerve maximally; 3) dissect between the SCM and parotid gland fascia; 4) resect the internal deep cervical lymph nodes; and 5) retract the digastric muscle, hypoglossal nerve, and occipital artery.
Results:
There were 8 cases (high cervical group, 4 cases; non-high cervical group, 4 cases) of postoperative diffusion-weighted imaging high signal and 6 cases (high cervical group, 3 cases; non-high cervical group, 3 cases) of symptomatic ischemic lesion. Four cases belonged to the technique-related cerebral infarction group and 4 cases to the perioperative-related cerebral infarction (PRCI) group. High cervical lesion is not considered to be a risk factor for either PRCI (P = 0.610) or technique-related cerebral infarction (P = 0.610). The difference of the diastolic blood pressure between the preoperative period and the second postoperative day showed a risk factor of PRCI (P = 0.033).
Conclusions:
The surgical outcomes for high cervical lesions are equivalent to that of non-high cervical lesions. Excessive blood pressure management from the early postoperative days is a risk of PRCI.