Related Experiment Video
Updated: Jan 2, 2026
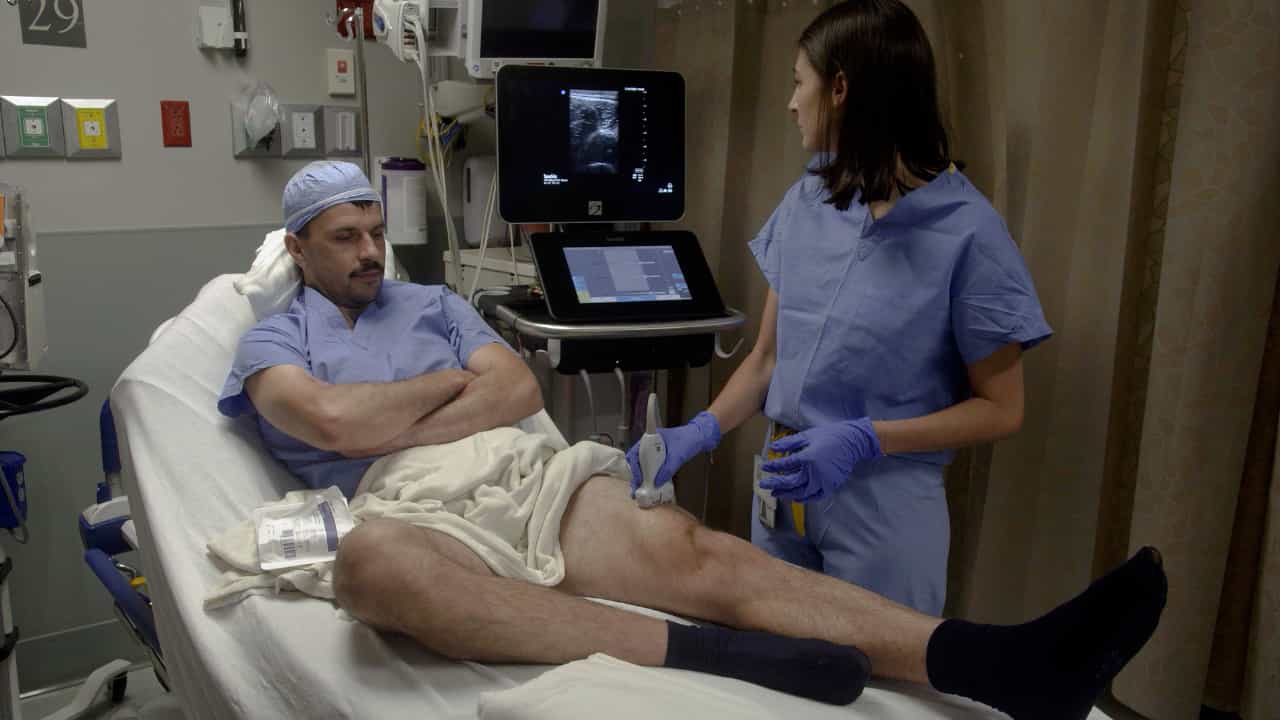
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Deficit Accumulation and Phenotype Assessments of Frailty Both Poorly Predict Duration of Hospitalization and Serious
Abraham Sonny1, Andrea Kurz, Linda A Skolaris
1From the Departments of General Anesthesiology (A.K., L.A.S., L.B., A.R., K.C.C.) Outcomes Research (A.K., N.M., D.Y., D.I.S.) Anesthesiology Institute (A.S.) the Nursing Institute (L.A.S., L.B., A.R.) the Department of Quantitative Health Sciences (N.M., D.Y.), Cleveland Clinic, Cleveland, Ohio. Current positions: Department of Anesthesia, Critical Care and Pain Medicine, Massachusetts General Hospital, Boston, Massachusetts (A.S.).

Background:
Frailty is associated with adverse postoperative outcomes, but it remains unclear which measure of frailty is best. This study compared two approaches: the Modified Frailty Index, which is a deficit accumulation model (number of accumulated deficits), and the Hopkins Frailty Score, which is a phenotype model (consisting of shrinking, weakness, exhaustion, slowness, and low physical activity). The primary aim was to compare the ability of each frailty score to predict prolonged hospitalization. Secondarily, the ability of each score to predict 30-day readmission and/or postoperative complications was compared.
Methods:
This study prospectively enrolled adults presenting for preanesthesia evaluation before elective noncardiac surgery. The Hopkins Frailty Score and Modified Frailty Index were both determined. The ability of each frailty score to predict the primary outcome (prolonged hospitalization) was compared using a ratio of root-mean-square prediction errors from linear regression models. The ability of each score to predict the secondary outcome (readmission and complications) was compared using ratio of root-mean-square prediction errors from logistic regression models.
Results:
The study included 1,042 patients. The frailty rates were 23% (Modified Frailty Index of 4 or higher) and 18% (Hopkins Frailty Score of 3 or higher). In total, 12.9% patients were readmitted or had postoperative complications. The error of the Modified Frailty Index and Hopkins Frailty Score in predicting the primary outcome was 2.5 (95% CI, 2.2, 2.9) and 2.6 (95% CI, 2.2, 3.0) days, respectively, and their ratio was 1.0 (95% CI, 1.0, 1.0), indicating similarly poor prediction. Similarly, the error of respective frailty scores in predicting the probability of secondary outcome was high, specifically 0.3 (95% CI, 0.3, 0.4) and 0.3 (95% CI, 0.3, 0.4), and their ratio was 1.00 (95% CI, 1.0, 1.0).
Conclusions:
The Modified Frailty Index and Hopkins Frailty Score were similarly poor predictors of perioperative risk. Further studies, with different frailty screening tools, are needed to identify the best method to measure perioperative frailty.


Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:17
Pathophysiology of Heart Failure
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Heart Failure III: Clinical Manifestations
 01:30
Heart Failure VII: Nursing Interventions