Related Experiment Video
Updated: Jan 1, 2026
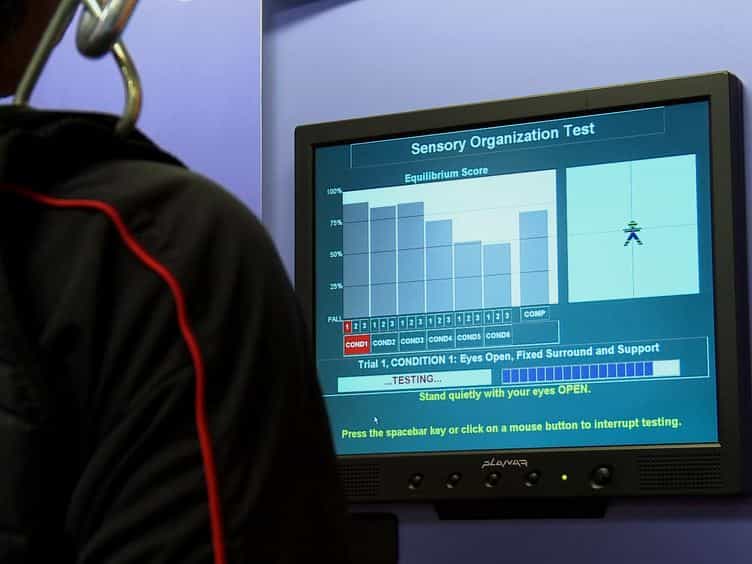

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Patients undergoing interventions for claudication experience low perioperative morbidity but are at risk for
Scott R Levin1, Alik Farber1, Thomas W Cheng1
1Division of Vascular and Endovascular Surgery, Boston Medical Center, Boston University School of Medicine, Boston, Mass.

Insights
Peripheral vascular interventions (PVIs) for intermittent claudication are common, but some treatments lack strong evidence. While perioperative risks are low, patients face functional decline and limb loss risks at one year.
Area of Science:
- Vascular Surgery
- Interventional Cardiology
- Public Health
Background:
- Intermittent claudication management guidelines emphasize long-term benefit and low complication risk.
- Contemporary interventional approaches for claudication require evaluation of their patterns and functional outcomes.
Purpose of the Study:
- To evaluate current patterns of peripheral vascular interventions (PVIs) for intermittent claudication.
- To assess the functional outcomes of these interventions at one year.
Main Methods:
- Analysis of the Vascular Study Group of New England database (2003-2018).
- Inclusion of peripheral vascular interventions (PVIs), infrainguinal bypasses, and suprainguinal bypasses for claudication.
- Evaluation of perioperative and one-year outcomes.
Main Results:
- Over 7000 PVIs, 2500 infrainguinal, and 800 suprainguinal bypasses were performed for claudication.
- Common interventions targeted iliac and femoral-popliteal arteries; isolated tibial interventions were infrequent.
- Perioperative complications were low, but 1-year outcomes showed risks of functional decline and limb loss.
Conclusions:
- Multisegment PVI is the most frequent intervention, though some treatments have limited evidence.
- Despite low perioperative morbidity and mortality, careful patient selection and optimization are crucial for long-term functional status and limb salvage.
Objective:
Interventional approaches to managing intermittent claudication vary widely. According to Society for Vascular Surgery guidelines, any invasive treatment of claudication must offer long-term benefit at low risk of complications. Our aim was to evaluate contemporary claudication intervention patterns and functional outcomes.
Methods:
The Vascular Study Group of New England database (2003-2018) was queried for peripheral vascular interventions (PVIs), infrainguinal bypasses, and suprainguinal bypasses for claudication. Perioperative and 1-year outcomes were evaluated.
Results:
There were 7051 PVIs, 2527 infrainguinal bypasses, and 849 suprainguinal bypasses performed for claudication. Treatment levels were iliac (52.2%), femoral-popliteal (54%), and tibial (5.7%). Isolated tibial interventions were completed in 1.7% of patients. Infrainguinal bypasses were most often to the popliteal artery (81.2%); however, in 18.8% of cases, bypasses were to tibial targets. Suprainguinal bypasses originated primarily from the abdominal aorta (88.6%) but also from the axillary artery (10.6%) and thoracic aorta (0.8%). Common perioperative complications were access site hematoma in 4.9% of PVIs and cardiac complications in 3.7% of infrainguinal bypasses and 11.3% of suprainguinal bypasses. Overall, 30-day mortality was 0.4% to 2%. After 1 year, of patients initially ambulating without assistance, 2.4% to 3.6% required assistance and 0.3% to 1.3% were nonambulatory. Ipsilateral reintervention/amputation-free survival, major amputation-free survival, and survival at 1 year were 81.4% to 90.6%, 92.9% to 94.1%, and 95.3% to 97%, respectively.
Conclusions:
Multisegment PVI was the most commonly performed intervention for claudication; however, a subset of patients received treatments supported by limited evidence, including isolated tibial PVI and bypasses with axillary inflow and tibial outflow. Interventions had low perioperative morbidity and mortality, yet patients were still at risk for worse functional status and limb loss at 1 year, emphasizing the importance of careful patient selection, medical optimization, and informed consent.
More Related Videos
 08:16
High-Resolution Three-Dimensional Imaging of the Footpad Vasculature in a Murine Hindlimb Gangrene Model
Published on: March 16, 2022
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:26
Cardiac Catheterization IV: Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management