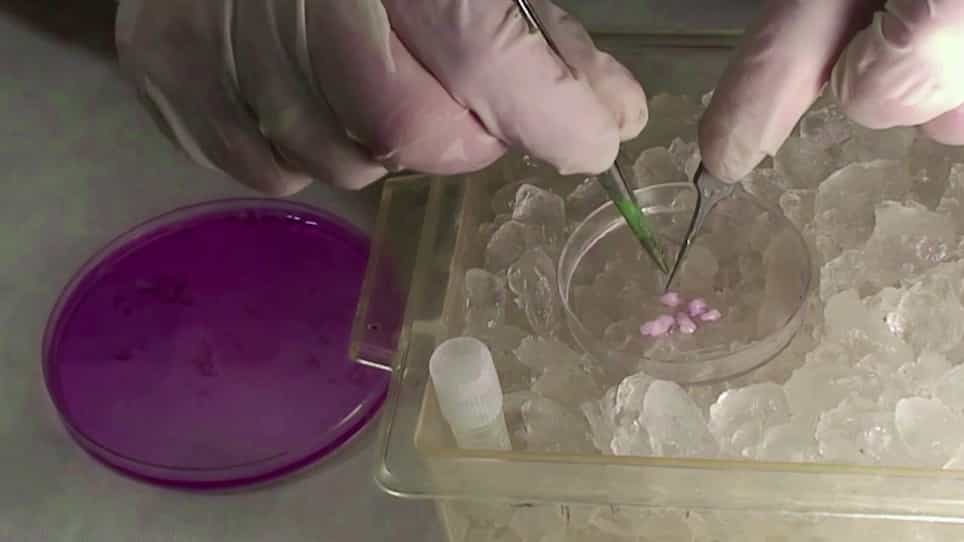
Related Experiment Video
Updated: Jan 1, 2026


An Ex Vivo Brain Slice Model to Study and Target Breast Cancer Brain Metastatic Tumor Growth
Published on: September 22, 2021
Capivasertib Plus Paclitaxel Versus Placebo Plus Paclitaxel As First-Line Therapy for Metastatic Triple-Negative
Peter Schmid1,2, Jacinta Abraham3, Stephen Chan4
1Barts ECMC, Barts Cancer Institute, Queen Mary University of London, London, United Kingdom.

Purpose:
The phosphatidylinositol 3-kinase (PI3K)/AKT signaling pathway is frequently activated in triple-negative breast cancer (TNBC). The AKT inhibitor capivasertib has shown preclinical activity in TNBC models, and drug sensitivity has been associated with activation of PI3K or AKT and/or deletions of PTEN. The PAKT trial was designed to evaluate the safety and efficacy of adding capivasertib to paclitaxel as first-line therapy for TNBC.
Patients And Methods:
This double-blind, placebo-controlled, randomized phase II trial recruited women with untreated metastatic TNBC. A total of 140 patients were randomly assigned (1:1) to paclitaxel 90 mg/m2 (days 1, 8, 15) with either capivasertib (400 mg twice daily) or placebo (days 2-5, 9-12, 16-19) every 28 days until disease progression or unacceptable toxicity. The primary end point was progression-free survival (PFS). Secondary end points included overall survival (OS), PFS and OS in the subgroup with PIK3CA/AKT1/PTEN alterations, tumor response, and safety.
Results:
Median PFS was 5.9 months with capivasertib plus paclitaxel and 4.2 months with placebo plus paclitaxel (hazard ratio [HR], 0.74; 95% CI, 0.50 to 1.08; 1-sided P = .06 [predefined significance level, 1-sided P = .10]). Median OS was 19.1 months with capivasertib plus paclitaxel and 12.6 months with placebo plus paclitaxel (HR, 0.61; 95% CI, 0.37 to 0.99; 2-sided P = .04). In patients with PIK3CA/AKT1/PTEN-altered tumors (n = 28), median PFS was 9.3 months with capivasertib plus paclitaxel and 3.7 months with placebo plus paclitaxel (HR, 0.30; 95% CI, 0.11 to 0.79; 2-sided P = .01). The most common grade ≥ 3 adverse events in those treated with capivasertib plus paclitaxel versus placebo plus paclitaxel, respectively, were diarrhea (13% v 1%), infection (4% v 1%), neutropenia (3% v 3%), rash (4% v 0%), and fatigue (4% v 0%).
Conclusion:
Addition of the AKT inhibitor capivasertib to first-line paclitaxel therapy for TNBC resulted in significantly longer PFS and OS. Benefits were more pronounced in patients with PIK3CA/AKT1/PTEN-altered tumors. Capivasertib warrants further investigation for treatment of TNBC.
Insights
Adding capivasertib to paclitaxel significantly improved progression-free survival (PFS) and overall survival (OS) for triple-negative breast cancer (TNBC) patients. The combination therapy showed greater benefits in patients with PIK3CA/AKT1/PTEN-altered tumors.
Area of Science:
- Oncology
- Pharmacology
Background:
- The phosphatidylinositol 3-kinase (PI3K)/AKT pathway is often overactive in triple-negative breast cancer (TNBC).
- The AKT inhibitor capivasertib has demonstrated preclinical efficacy in TNBC models.
- Sensitivity to capivasertib may be linked to PI3K/AKT activation or PTEN loss.
Purpose of the Study:
- To assess the safety and efficacy of combining capivasertib with paclitaxel as a first-line treatment for TNBC.
- The PAKT trial investigated this combination therapy in a phase II setting.
Main Methods:
- A double-blind, placebo-controlled, randomized phase II trial involving 140 women with untreated metastatic TNBC.
- Patients received paclitaxel plus either capivasertib or a placebo every 28 days until disease progression or toxicity.
- Primary endpoint was progression-free survival (PFS); secondary endpoints included overall survival (OS) and outcomes in specific genetic subgroups.
Main Results:
- Median PFS was 5.9 months with capivasertib plus paclitaxel versus 4.2 months with placebo (HR, 0.74; P=.06).
- Median OS was 19.1 months with capivasertib plus paclitaxel versus 12.6 months with placebo (HR, 0.61; P=.04).
- In patients with PIK3CA/AKT1/PTEN alterations (n=28), median PFS was 9.3 months with capivasertib versus 3.7 months with placebo (HR, 0.30; P=.01).
Conclusions:
- Adding capivasertib to first-line paclitaxel significantly improved PFS and OS in TNBC patients.
- The therapeutic benefit was more pronounced in patients with PIK3CA/AKT1/PTEN-altered tumors.
- Capivasertib warrants further investigation for TNBC treatment.