Acute cholecystitis or simple biliary colic after an emergency presentation: why it matters
Related Experiment Video
Updated: Jan 1, 2026
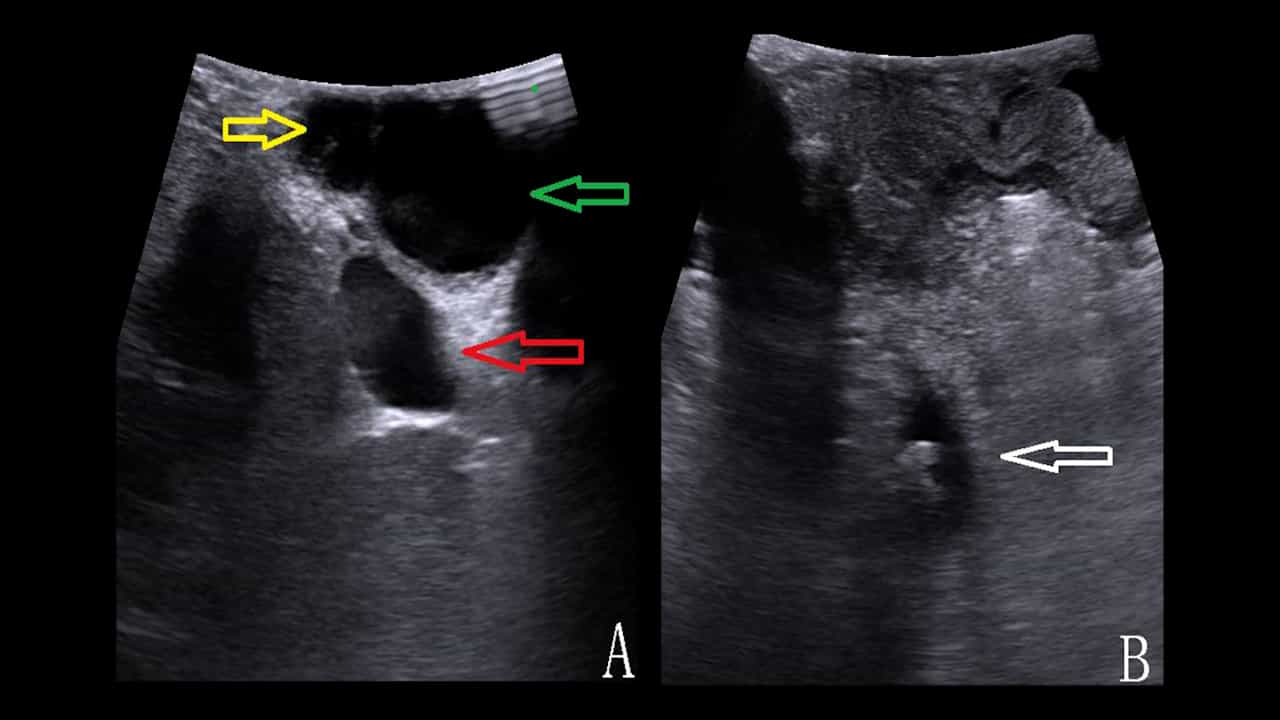
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Chu Luan Nguyen1, Aafke van Dijk2, Garett Smith1,3
1Upper Gastrointestinal Surgical Unit, Royal North Shore Hospital and North Shore Private Hospital, Sydney, New South Wales, Australia.

Background:
Laparoscopic cholecystectomy (LC) is often performed during the index admission after emergency presentation for acute biliary pain. Many patients have acute cholecystitis (AC) that may increase operative difficulty and complications. Our primary aim was to assess the validity of Tokyo Guidelines (TG18) for diagnosing AC by comparison with the admitting team diagnosis, operative findings and histopathology. The secondary aim was to assess outcomes after same-admission or delayed LC.
Methods:
Retrospective analysis of patients who underwent LC after presenting to a tertiary hospital emergency department over a 12-month period was conducted.
Results:
A total of 139 patients underwent LC with no mortality or bile duct injury. A diagnosis of AC made by the admitting surgical team had sensitivity of 84% and specificity of 57%. The TG18 diagnosis had sensitivity of 84% and specificity of 53%. A diagnosis of AC by the admitting surgical team correlated well with TG18 criteria diagnosis. There was poor correlation between clinical and histopathological diagnoses. Nine percent of patients had complications and 4% required conversion to open procedure. Patients with a clinical diagnosis of AC had longer post-operative length of stay and more complications compared with those who had non-AC diagnosis. There was no difference in outcomes between same-admission LC or delayed LC.
Conclusion:
TG18 diagnosis of AC does not improve accuracy of diagnosis or predictability of a poor outcome over the admitting surgical team diagnosis. Same-admission LC for patients with AC is associated with similar outcomes compared to those who undergo delayed LC.
More Related Videos
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:26
Endoscopic Procedures V: ERCP
Patient...