Related Experiment Video
Updated: Jan 1, 2026
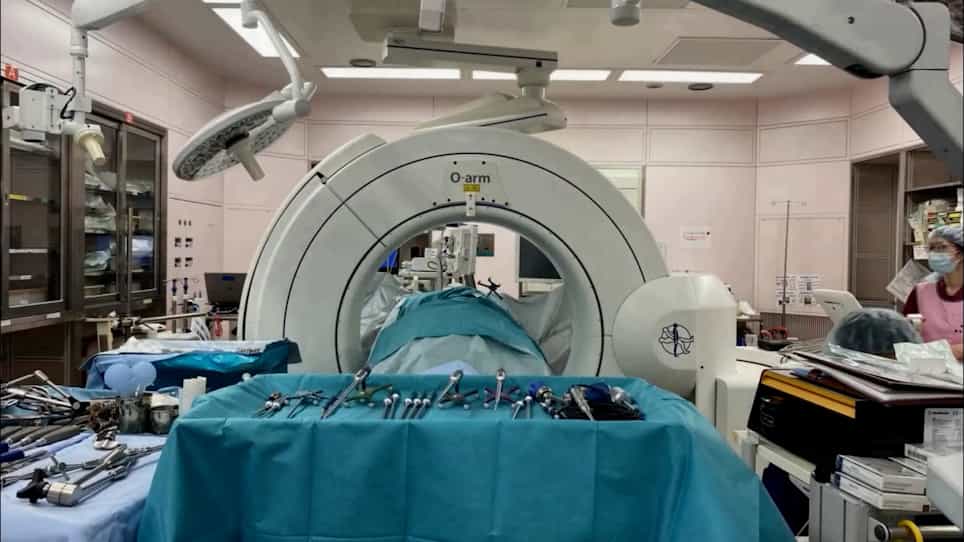
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Latarjet with cortical button fixation is associated with an increase of the risk of recurrent dislocation compared
Alexandre Hardy1, Vincent Sabatier2, Bradley Schoch3
1Clinique du Sport, Paris, France.

Purpose:
The purpose of this study was to compare the clinical results of the Latarjet procedure using two cortical buttons vs two screws. It was hypothesized that cortical button would result in similar rates of recurrent dislocations, but a lower rate of reoperation compared to screw fixation.
Methods:
A retrospective comparative case-cohort analysis was performed for all patients undergoing a Latarjet procedure for recurrent anterior glenohumeral instability. Patient demographics, number of dislocations prior surgery, arm dominance, shoulder hyperlaxity, level of sport, type of sport and ISIS score were collected. Shoulders were separated into two groups based on surgical fixation (screws vs cortical button). Postoperatively, shoulders were evaluated for recurrent dislocation, revision surgery, post-operative Walch-Duplay score, and the Simple shoulder test (SST). Two hundred and thirty-six patients were included in the screw fixation group (group A) and 72 in button fixation group (group B) and were evaluated at a mean follow-up of 3.4 ± 0.8 years. Demographics of the two groups were similar with the exception of operative side hand dominance, which was more common in group B [50 (69.4%) vs 128 (54.2%), p = 0.02].
Results:
Recurrent dislocation was significantly lower in Group A: 6 (2.5%) vs 6(8.3%) (p = 0.02). Reoperation was more common in group A [14 (5.9%) vs 0 (0%)]. At follow-up, Walch-Duplay scores and simple shoulder tests were similar in both groups.
Conclusion:
Button fixation for Latarjet showed higher rates of recurrent dislocation compared to screw fixation. However, the increased stability afforded by screw fixation needs to be weighed against the increased risk of reoperation for hardware prominence.
Level Of Evidence:
III.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025