Related Experiment Video
Updated: Jan 1, 2026
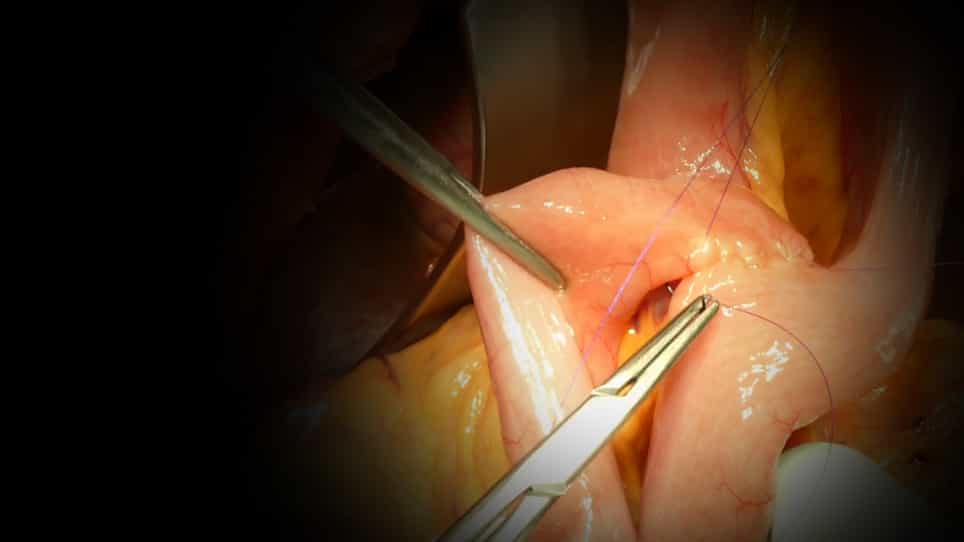
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Postoperative Outcomes and Functional Recovery After Preoperative Combination Chemotherapy for Pancreatic Cancer: A
Nicolò Pecorelli1, Michele Pagnanelli2, Lorenzo Cinelli2
1Division of Pancreatic Surgery, Pancreas Translational & Clinical Research Center, San Raffaele Scientific Institute, Milan, Italy.

Abstract:
Introduction: Previous studies show encouraging oncologic outcomes for neoadjuvant chemotherapy (NACT) in the setting of pancreatic ductal adenocarcinoma (PDAC). However, recent literature reported an increased clinical burden in patients undergoing pancreaticoduodenectomy (PD) following NACT. Therefore, the aim of our study was to assess the impact of NACT on postoperative outcomes and recovery after PD. Methods: A retrospective propensity score-matched study was performed including all patients who underwent PD for PDAC in a single center between 2015 and 2018. Patients treated with NACT for resectable, borderline resectable or locally advanced PDAC were matched based on nearest neighbor propensity scores in a 1:1 ratio to patients who underwent upfront resection. Propensity scores were calculated using 7 perioperative variables, including gender, age, BMI, ASA score, Charlson-Deyo comorbidity score, fistula risk score (FRS), vascular resection. Primary outcome was the number and severity of complications at 90-days after surgery measured by the comprehensive complication index (CCI). Data are reported as median (IQR) or number of patients (%). Results: Of 283 resected patients, 95 (34%) were treated with NACT. Before matching, NACT patients were younger, had less comorbidities (Charlson-Deyo score 0 vs. 1, p = 0.04), similar FRS [2 (0-3) for both groups], and more vascular resections performed [n = 28 (30%) vs. n = 26 (14%), p < 0.01]. After propensity-score matching, preoperative and intraoperative characteristics were comparable. Postoperatively, CCI was similar between groups [8.7 (0-29.6) for both groups, p = 0.59]. NACT patients had a non-statistically significant increase in superficial incisional surgical site infections [n = 12 (13%) vs. 6 (6%), p = 0.14], while no difference was found for overall infectious complications and organ-space SSI. The occurrence of clinically-relevant pancreatic fistula was similar between groups [10 (11%) vs. 13 (14%), p = 0.51]. No difference was found between groups for length of hospital stay [8 (7-15) vs. 8 (7-14) days, p = 0.62], and functional recovery outcomes. Conclusion: After propensity score adjustment for perioperative risk factors, NACT did not worsen postoperative outcomes and functional recovery following PD for PDAC compared to upfront resection.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management