Related Experiment Video
Updated: Jan 1, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Evaluation of Concentration Errors and Inappropriate Dose Tailoring of Tacrolimus Caused by Sampling-Time Deviations
Junyan Wang1, Peng Gao, Huifen Zhang
1Department of Pharmacy, Children's Hospital, Zhejiang University School of Medicine, Hangzhou, Zhejiang, China.

Background:
Tacrolimus dosing is routinely tailored based on its trough level (C0) drawn by therapeutic drug monitoring in pediatric patients with primary nephrotic syndrome. However, this concentration is often inaccurate owing to inappropriate practice, such as deviation of sampling time (DST). The quantitative relationship between DST and C0 remains unclear.
Methods:
Tacrolimus concentration at nominal sampling times (12 hours after last dose) and 32 deviation scenarios (12 ± 4 hours every 15 minutes) was predicted using a previously validated population pharmacokinetic model based on 162 scenarios of 100 primary nephrotic syndrome patients involved in the population pharmacokinetic model and derived virtual patients. Concentration error (CE) and relative CE (RCE) were evaluated, and the correlation between DST and RCE was evaluated by subgroup analysis using linear regression. Ultimately, the inappropriate dosing possibly misled by incorrect C0 was simulated in a real-patient cohort according to the target range (5-10 ng/mL).
Results:
Approximately 7% of RCE was caused at every 1-hour of DST. DST was the most major contributor of RCE (r = 0.773-0.804). Patients with early sampling, older age, high body weight, high dose, low aspartate transaminase level, high corticosteroid dose, and without combination of azole antifungal agents were revealed to have high RCE. Approximately 7%-36% and 9%-25% of inappropriate dose tailoring may be caused by early and delayed sampling, respectively. In addition, patients with early sampling or high-dose tacrolimus had a higher risk of inappropriate dosing than patients with delayed sampling [hazard ratio = 1.53, 95% confidence interval (CI): 1.03-2.27, P = 0.048], and low-dose tacrolimus (P < 0.0001).
Conclusions:
A moderate bias of concentration and dose tailoring was revealed within 4 hours of DST. In addition, a high risk of bias was found in patients with early sampling and high-dose tacrolimus.
More Related Videos

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:15
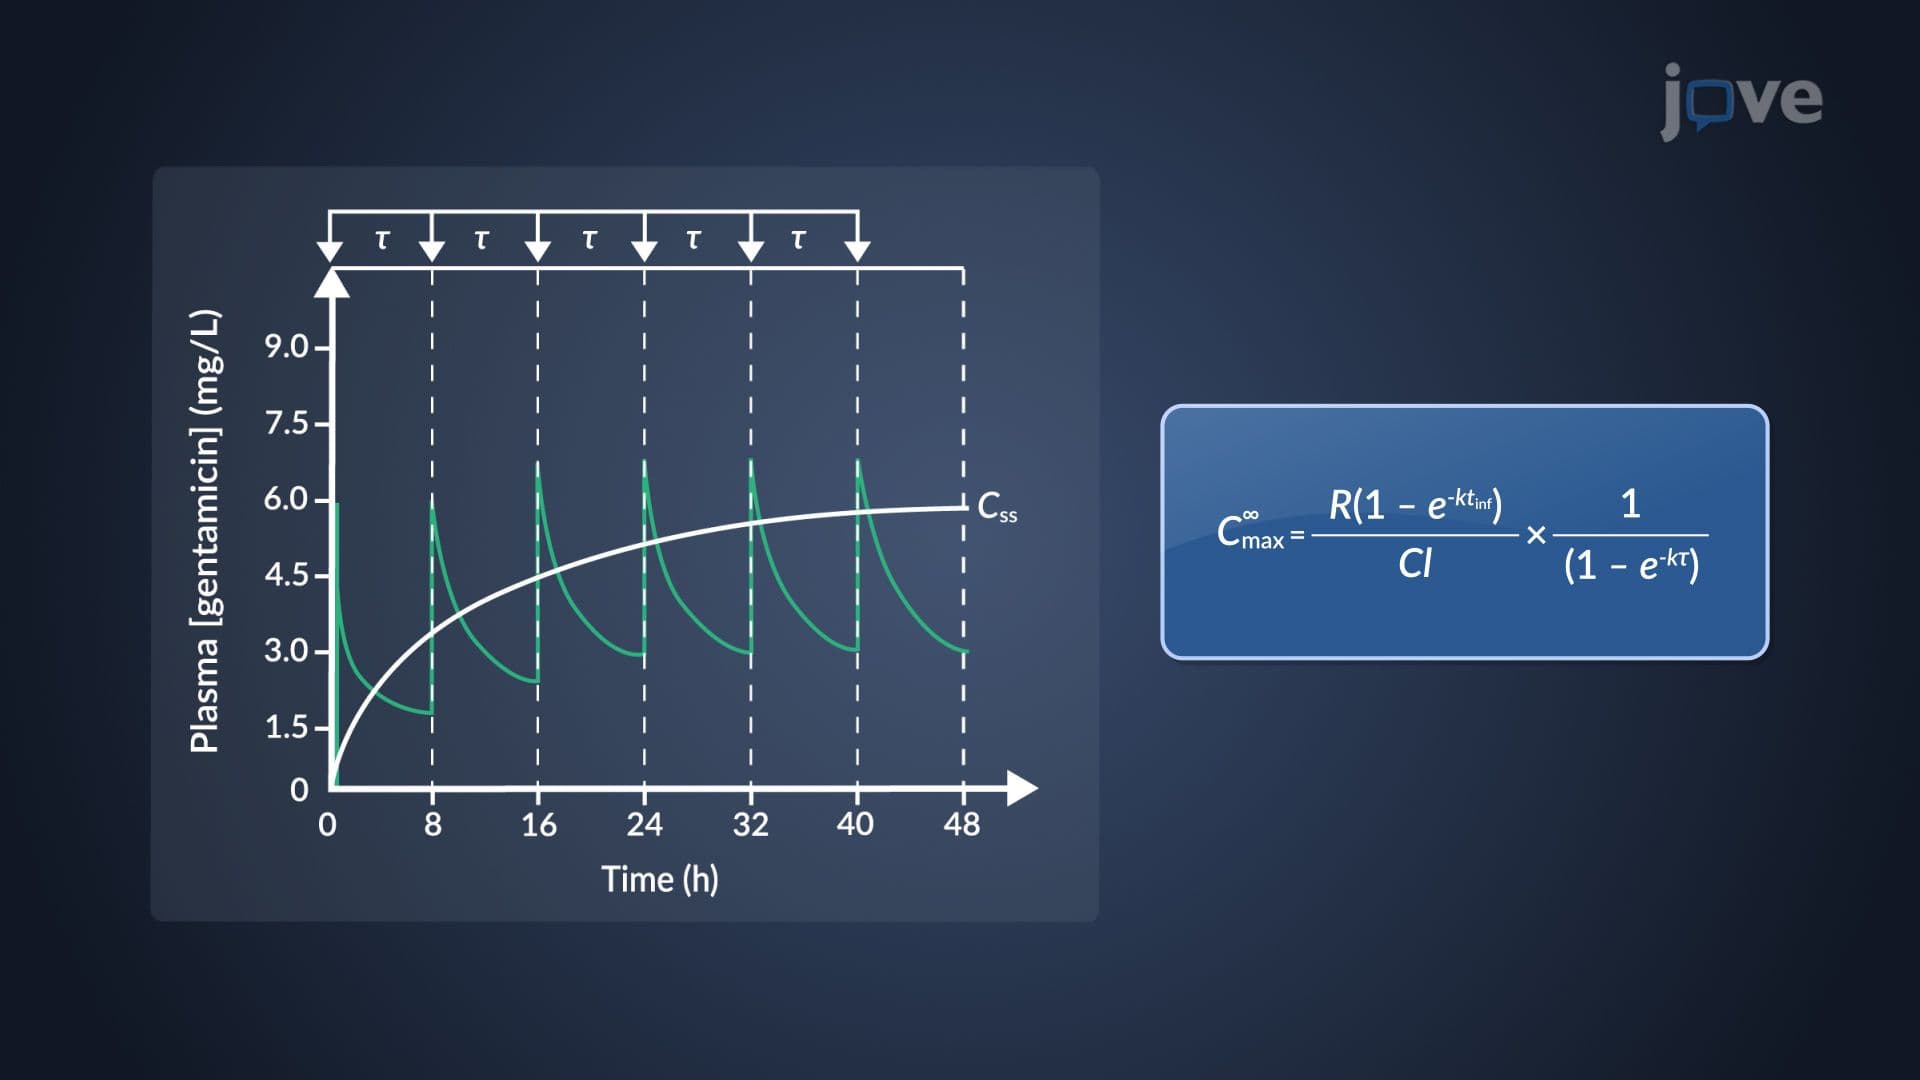
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:29
Drug Dosing: Infants and Children