Related Experiment Video
Updated: Jan 1, 2026

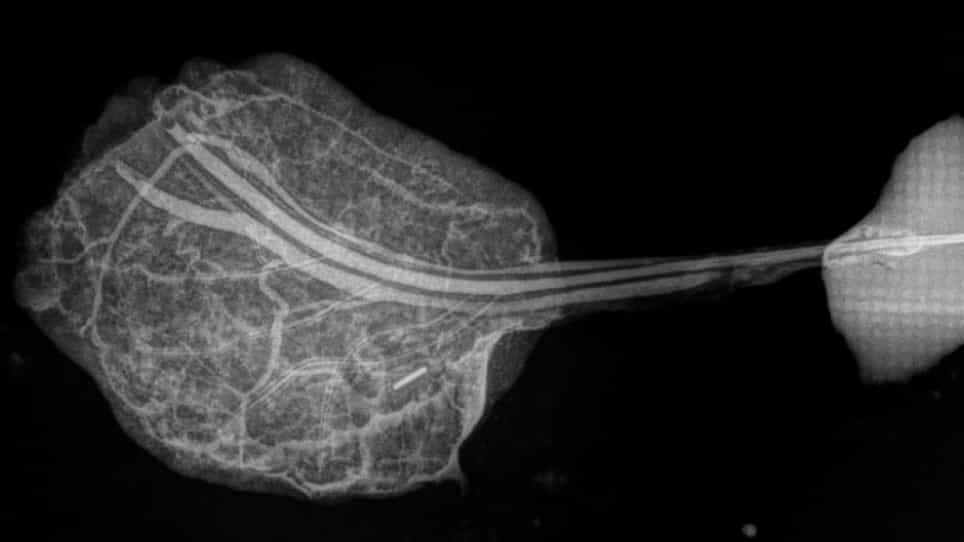
An Experimental Human DIEP Flap Model to Investigate Preservation Strategies for Vascularized Composite Allografts and Free Flaps
Published on: December 5, 2025
In vivo perfusion of free skin flaps using extracorporeal membrane oxygenation
Klaus-Dietrich Wolff1, Lucas M Ritschl1, Achim von Bomhard1
1Technical University of Munich, School of Medicine, Department of Oral and Maxillofacial Surgery, Ismaninger Str. 22, Munich, 81675, Germany.

Background:
The vessel-depleted, irradiated, and frozen neck, as well as severe atherosclerosis of recipient vessels represent challenging problems in free flap transfer. Extracorporeal free flap perfusion theoretically allows free flap reconstructions in the absence of local donor vessels, but is associated with a number of technical issues. In this study, a novel technique is presented using a commercially available system for extracorporeal membrane oxygenation (ECMO), modified for small blood volumes.
Methods:
After preclinical testing, an ECMO system certified for lung support was used to establish blood flow through the flap's artery with oxygenation, decarboxylation and warming of diluted packed blood cells. Venous blood was allowed to flow passively into a separate container. Perfusion was performed for 15 min at intervals of 4 h over 4-6 days.
Results:
Five patients with soft tissue defects requiring free flap reconstruction were included. Either primarily thinned anterolateral thigh (ALT) flaps (n = 3) or radial forearm flaps (n = 2) were used. We observed infection of the perfusate, with consequent subtotal flap loss, in one patient, complete epithelial loss in two patients, venous congestion in one case, and almost uneventful healing in the fifth patient. With conservative wound care and a split thickness skin graft in one case, stable wound coverage was achieved in all patients except one, who had secondary healing. None of the patients required a second flap for sufficient coverage.
Conclusions:
The technique described is associated with the risks of infection, flap congestion, nutritive hypoperfusion, and consequent tissue loss. Nevertheless, stable defect closure seems to be achievable even in patients with depleted recipient vessels.