Related Experiment Video
Updated: Jan 1, 2026
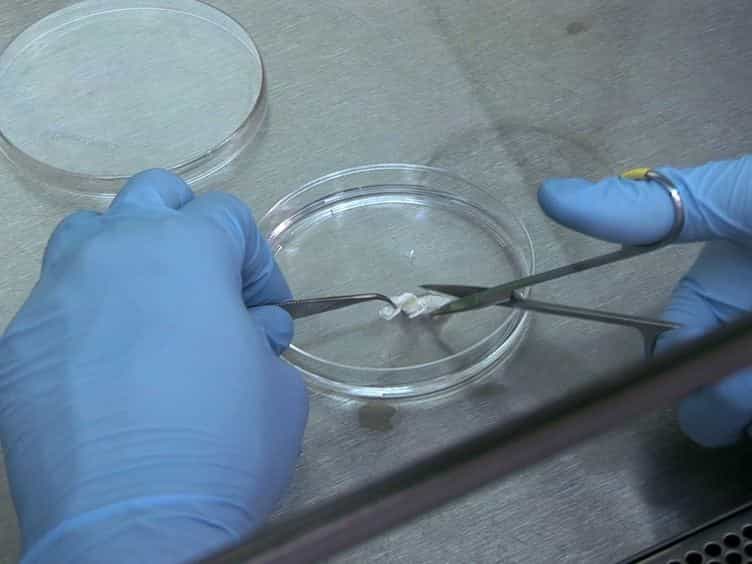
Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Rotatory Knee Laxity Exists on a Continuum in Anterior Cruciate Ligament Injury
Jayson Lian1,2, Theresa Diermeier1,3, Mitchell Meghpara1
1Department of Orthopaedic Surgery, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania.

Background:
The purpose of this investigation was to compare the magnitude of rotatory knee laxity in patients with a partial anterior cruciate ligament (ACL) tear, those with a complete ACL tear, and those who had undergone a failed ACL reconstruction. It was hypothesized that rotatory knee laxity would increase with increasing injury grade, with knees with partial ACL tears demonstrating the lowest rotatory laxity and knees that had undergone failed ACL reconstruction demonstrating the highest rotatory laxity.
Methods:
A prospective multicenter study cohort of 354 patients who had undergone ACL reconstruction between 2012 and 2018 was examined. All patients had both injured and contralateral healthy knees evaluated using standardized, preoperative quantitative pivot shift testing, determined by a validated, image-based tablet software application and a surface-mounted accelerometer. Quantitative pivot shift was compared with the contralateral healthy knee in 20 patients with partial ACL tears, 257 patients with complete ACL tears, and 27 patients who had undergone a failed ACL reconstruction. Comparisons were made using 1-way analysis of variance (ANOVA) with post hoc 2-sample t tests with Bonferroni correction. Significance was set at p < 0.05.
Results:
There were stepwise increases in side-to-side differences in quantitative pivot shift in terms of lateral knee compartment translation for patients with partial ACL tears (mean [and standard deviation], 1.4 ± 1.5 mm), those with complete ACL tears (2.5 ± 2.1 mm), and those who had undergone failed ACL reconstruction (3.3 ± 1.9 mm) (p = 0.01) and increases in terms of lateral compartment acceleration for patients with partial ACL tears (0.7 ± 1.4 m/s), those with complete ACL tears (2.3 ± 3.1 m/s), and those who had undergone failed ACL reconstruction (2.4 ± 5.5 m/s) (p = 0.01). A significant difference in lateral knee compartment translation was found when comparing patients with partial ACL tears and those with complete ACL tears (1.2 ± 2.1 mm [95% confidence interval (CI), 0.2 to 2.1 mm]; p = 0.02) and patients with partial ACL tears and those who had undergone failed ACL reconstruction (1.9 ± 1.7 mm [95% CI, 0.8 to 2.9 mm]; p = 0.001), but not when comparing patients with complete ACL tears and those who had undergone failed ACL reconstruction (0.8 ± 2.1 [95% CI, -0.1 to 1.6 mm]; p = 0.09). Increased lateral compartment acceleration was found when comparing patients with partial ACL tears and those with complete ACL tears (1.5 ± 3.0 m/s [95% CI, 0.8 to 2.3 m/s]; p = 0.0002), but not when comparing patients with complete ACL tears and those who had undergone failed ACL reconstruction (0.1 ± 3.4 m/s [95% CI, -2.2 to 2.4 m/s]; p = 0.93) or patients with partial ACL tears and those who had undergone failed ACL reconstruction (1.7 ± 4.2 m/s [95% CI, -0.7 to 4.0 m/s]; p = 0.16). An increasing lateral compartment translation of the contralateral, ACL-healthy knee was found in patients with partial ACL tears (0.8 mm), those with complete ACL tears (1.2 mm), and those who had undergone failed ACL reconstruction (1.7 mm) (p < 0.05).
Conclusions:
A progressive increase in rotatory knee laxity, defined by side-to-side differences in quantitative pivot shift, was observed in patients with partial ACL tears, those with complete ACL tears, and those who had undergone failed ACL reconstruction. These results may be helpful when assessing outcomes and considering indications for the management of high-grade rotatory knee laxity.
Level Of Evidence:
Prognostic Level III. See Instructions for Authors for a complete description of levels of evidence.
More Related Videos
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025
 05:07
Author Spotlight: Implementing the Enhanced Recovery After Surgery Concept in Rehabilitation Following Anterior Cruciate Ligament Reconstruction
Published on: March 1, 2024
Related Concept Videos
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:23
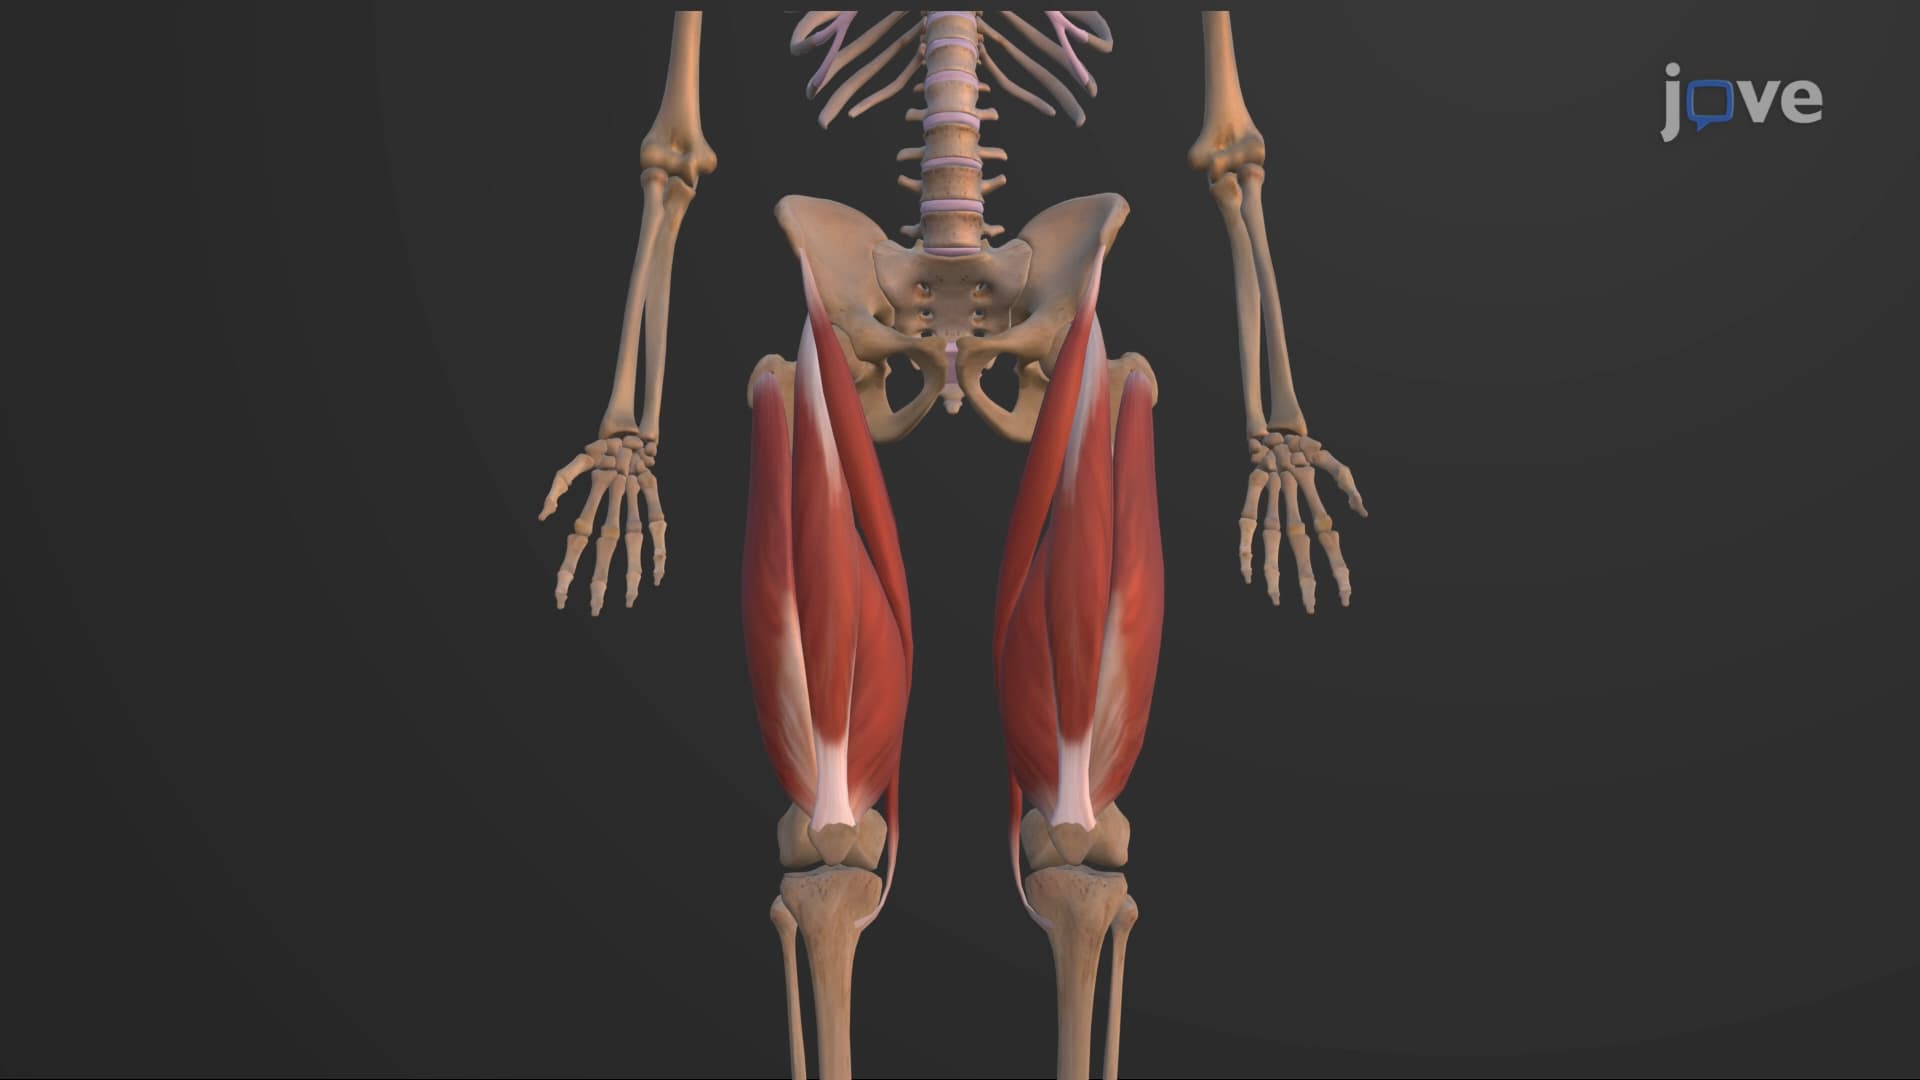
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:10
Ankle Joint
 01:13
Angle of Twist - Elastic Range
 01:09
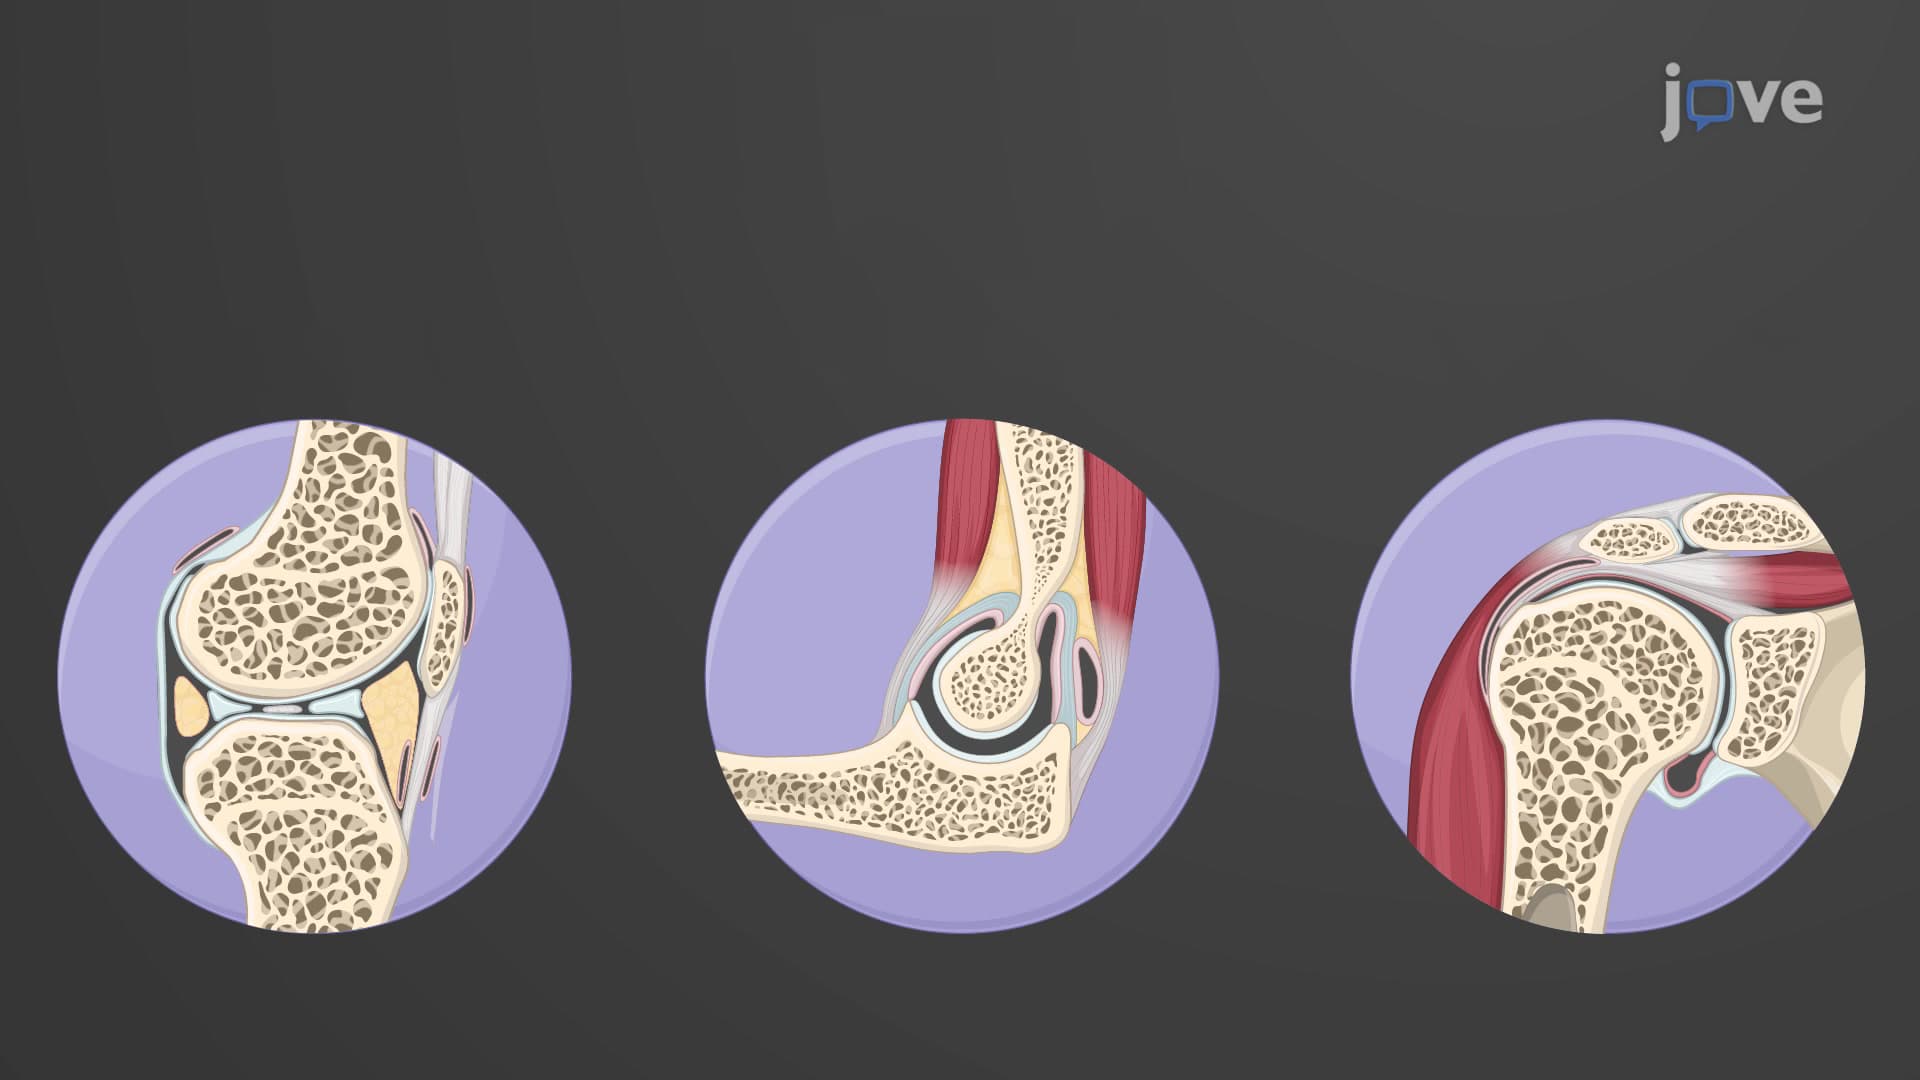
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...