Related Experiment Video
Updated: Jan 1, 2026

An Educational Video Demonstration of How to Prone a Critically Ill Intubated Patient
Published on: November 30, 2022
Prone ventilation in H1N1 virus-associated severe acute respiratory distress syndrome: A case series
Jyoti Narayan Sahoo1, Mohan Gurjar2, Krantimaya Mohanty1
1Department of Critical Care Medicine, Sunshine Hospital, Bhubaneswar, Odisha, India.

Background:
Management of H1N1 viral infection-associated acute respiratory distress syndrome (ARDS) has primarily been focused on lung protective ventilation strategies, despite that mortality remains high (up to 45%). Other measures to improve survival are prone position ventilation (PPV) and extracorporeal membrane oxygenation. There is scarcity of literature on the use of prone ventilation in H1N1-associated ARDS patients.
Methods:
In this retrospective study, all adult patients admitted to medical intensive care unit (ICU) with H1N1 viral pneumonia having severe ARDS and requiring prone ventilation as a rescue therapy for severe hypoxemia were reviewed. The patients were considered to turn prone if PaO2/FiO2 ratio was <100 cmH2O and PaCO2 was >45 cmH2O; if no progressive improvement was seen in PaO2/FiO2 over a period of 4 h, then patients were considered to turn back to supine. Measurements were obtained in supine (baseline) and PPV, after 30-60 min and then 4-6 hourly.
Results:
Eleven adult patients with severe ARDS were ventilated in prone position. Their age range was 26-59 years. The worst PaO2/FiO2 ratio range on the day of invasive ventilation was 48-100 (median 79). A total of 39 PPV sessions were done, with a range of 1-8 prone sessions per patient (median three sessions). Out of the 39 PPV sessions, PaO2/FiO2 ratio and PaCO2 responder were 38 (97.4%) and 27 (69.2%) sessions, respectively. The median ICU stay and mechanical ventilation days were 15 (range: 3-26) and 12 (range: 2-22) days, respectively. The common complication observed due to PPV was pressure ulcer. At ICU discharge, all except two patients survived.
Conclusion:
PPV improves oxygenation when started early with adequate duration and should be considered in all severe ARDS cases secondary to H1N1 viral infection.
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:14
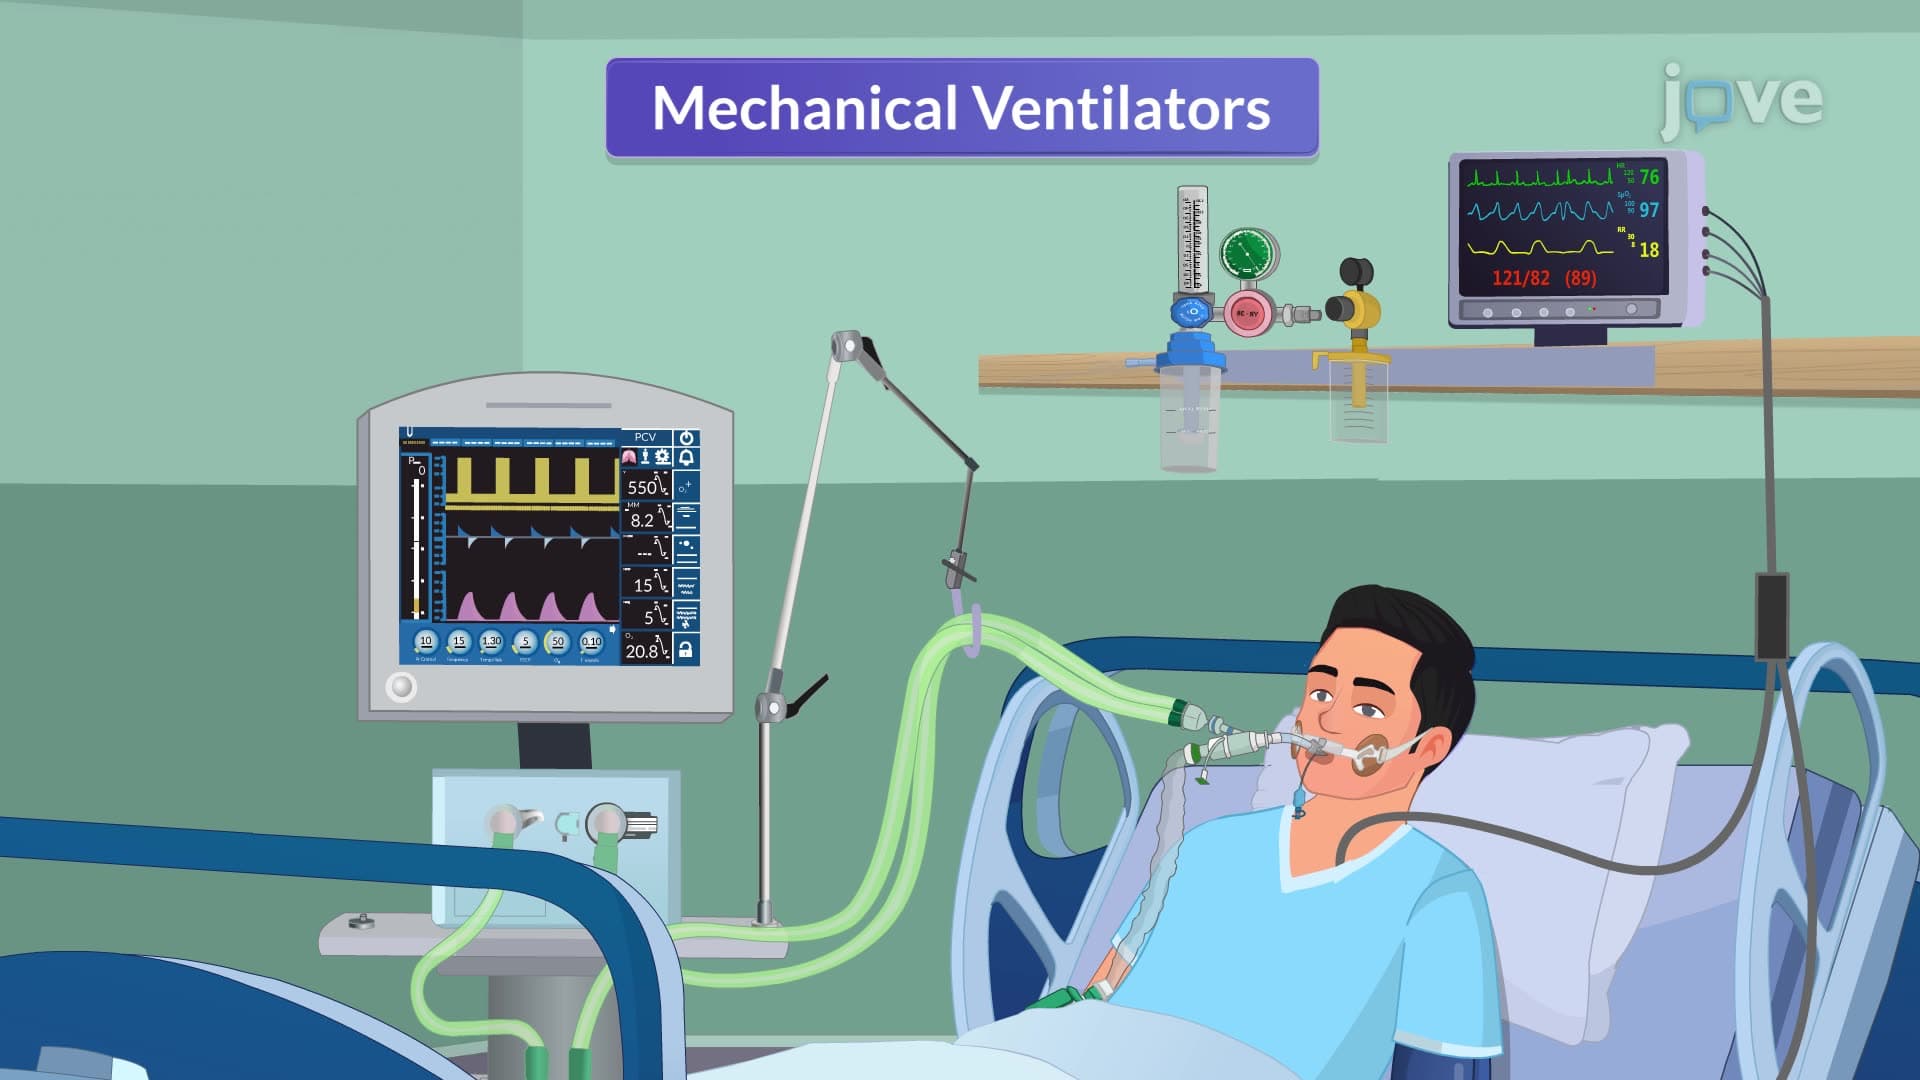
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...