Related Experiment Video
Updated: Dec 31, 2025
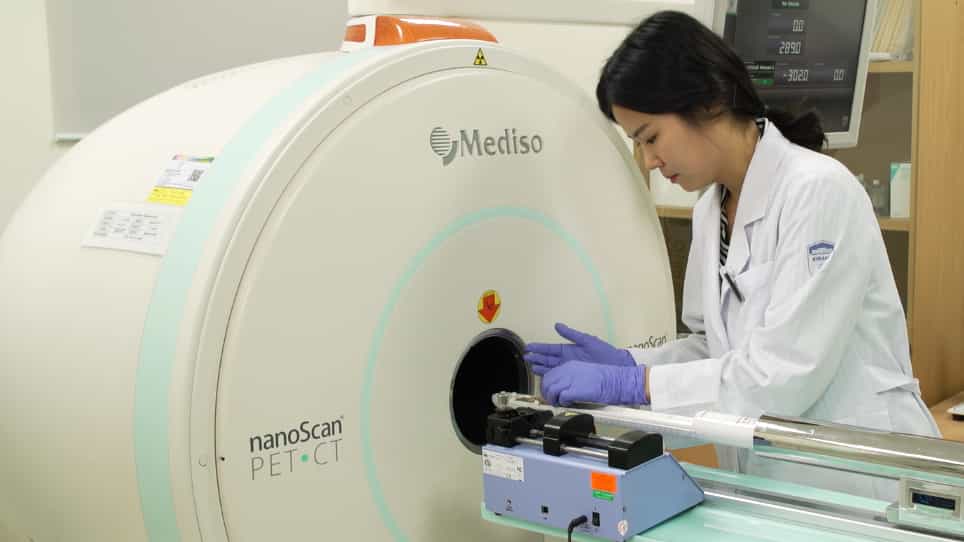
Preparing a 68Ga-labeled Arginine Glycine Aspartate RGD-peptide for Angiogenesis
Published on: January 7, 2019
Lenvatinib for Radioactive Iodine-Refractory Differentiated Thyroid Carcinoma and Candidate Biomarkers Associated
Eyun Song1, Mijin Kim2, Eui Young Kim3
1Division of Endocrinology and Metabolism, Department of Internal Medicine, Asan Medical Center, University of Ulsan College of Medicine, Seoul, Republic of Korea.

Abstract:
Lenvatinib, an oral multikinase inhibitor, is the latest addition to the treatment options for radioactive iodine (RAI)-refractory progressive differentiated thyroid carcinoma (DTC). This study investigated the efficacy of lenvatinib in real-world practice and prognostic biomarkers of survival. This multicenter study included 43 patients receiving lenvatinib as first-line or second-line treatment after sorafenib for RAI-refractory DTC. Progression-free survival (PFS) was evaluated according to various clinical factors including thyroglobulin doubling time (TgDT), tumor volume DT (TVDT), and tumor growth slope (TGS; slope of tumor change rate). Patients were treated with lenvatinib for a median of 14 months; 32 were previously treated with sorafenib. The median follow-up from lenvatinib initiation to the last censoring or death was 16 months. The median starting dose of 20 mg was reduced to a median sustainable dose of 10 mg in accordance with patient adverse events (AEs). The median PFS was 21.8 months; the median overall survival was not reached. The disease control rate was 97.7%, with the first objective response at 3.8 months. PFS was not significantly associated with previous sorafenib treatment, metastatic sites, or sustainable dose. TGS measured before (TGSpre, p = 0.003) and after (TGSpost, p = 0.036) the initiation of lenvatinib was associated with PFS. The sum of the largest diameters of target lesions (p = 0.043) and TgDT (p = 0.024) were associated with PFS, but TVDT calculated before (TVDTpre, p = 0.923) or after (TVDTpost, p = 0.966) lenvatinib treatment did not impact PFS. Lenvatinib was withdrawn in 24 patients (55.8%): in 6 patients because of treatment-induced AEs and in 18 patients because of disease progression or poor performance status. AEs of any grade were reported in all patients, and grade 3-4 AEs in 23.2% of the patients. The most frequent AE was fatigue or asthenia. Our results indicate that reduced doses of lenvatinib triggered by emergent AEs did not abrogate its apparent efficacy in patients with RAI-refractory DTCs. Rather, the sustained use of reduced doses of lenvatinib with a low rate of severe AEs may have contributed to the favorable outcomes. TgDT and TGS can assist in predicting the outcomes in these patients.

